
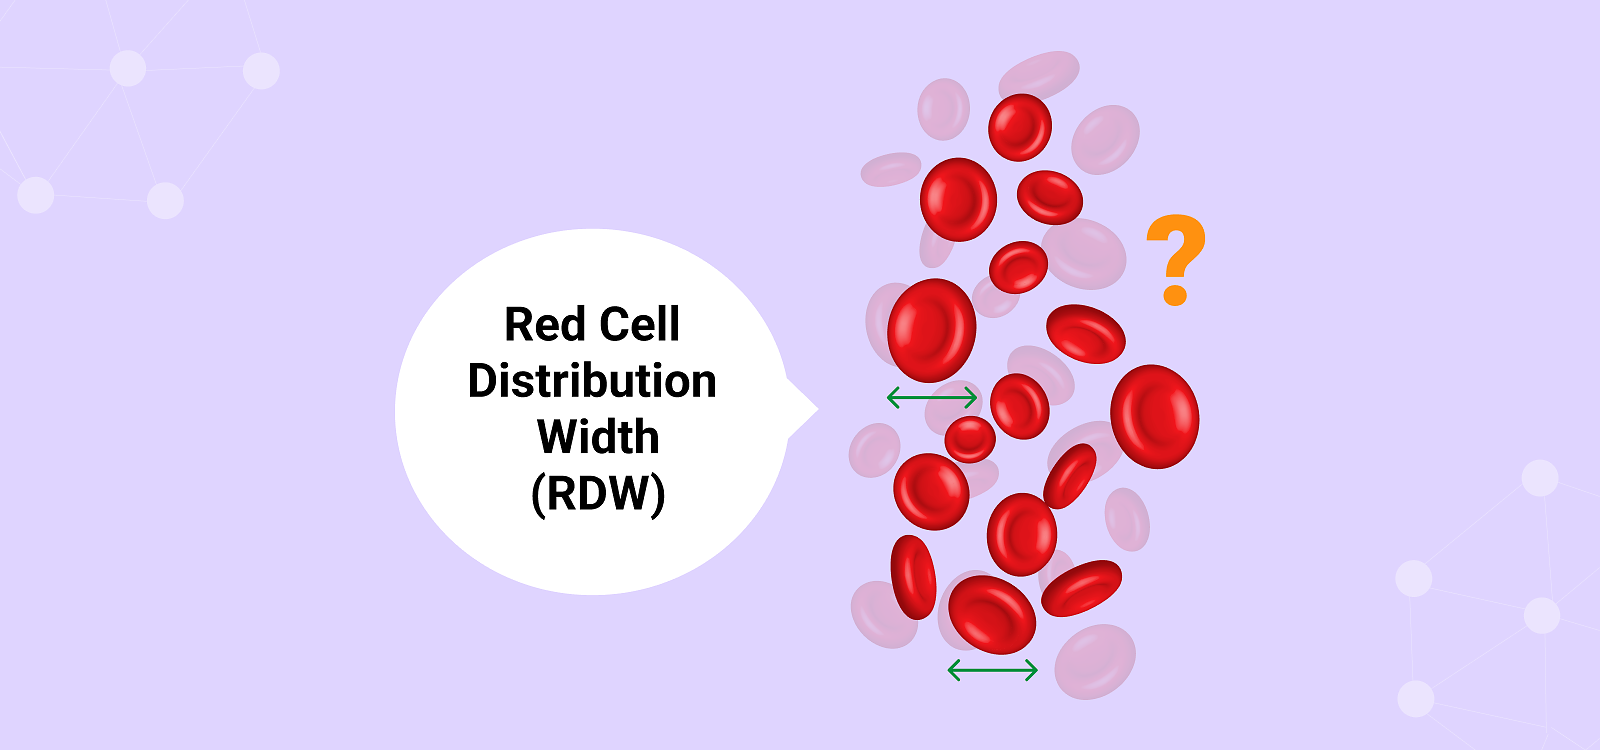
Understanding Red Cell Distribution Width (RDW) is crucial for a comprehensive assessment of hematological health, offering insights beyond standard red blood cell counts. RDW measures the variation in the size and volume of your red blood cells (erythrocytes). While red blood cells are typically uniform in size, certain conditions can lead to significant variations, a state known as anisocytosis. The RDW test quantifies this heterogeneity, providing a valuable diagnostic marker that aids in identifying and differentiating various medical conditions, particularly types of anemia.
The Basics of RDW Measurement
The RDW is usually part of a complete blood count (CBC), a common diagnostic test that provides a detailed picture of the cells in your blood, including red blood cells, white blood cells, and platelets. The measurement is expressed as a percentage or in femtoliters (fL), typically as RDW-CV (Coefficient of Variation) or RDW-SD (Standard Deviation). RDW-CV is more commonly reported and is calculated from the standard deviation of red blood cell volume divided by the mean corpuscular volume (MCV), then multiplied by 100 to express it as a percentage. RDW-SD, on the other hand, measures the width of the red cell volume distribution curve at the 20% level above the baseline, providing a direct measurement of cell size variation that is less influenced by MCV.
The automated hematology analyzers used in laboratories precisely measure the volume of thousands of individual red blood cells and then calculate the RDW based on the distribution of these volumes. A narrow distribution indicates uniform cell size, while a wide distribution indicates significant variation.
Normal RDW Ranges and Their Significance
Normal RDW ranges typically fall between 11.5% and 14.5% for RDW-CV, though specific laboratory reference ranges may vary slightly. An RDW within this normal range suggests that your red blood cells are relatively uniform in size. However, a normal RDW does not always rule out disease, especially if other CBC parameters are abnormal. For instance, some types of anemia, such as aplastic anemia or certain forms of thalassemia trait, might present with a normal RDW if the red cells are uniformly small or large. Therefore, RDW is rarely interpreted in isolation but rather in conjunction with other blood indices, particularly MCV, which measures the average volume of red blood cells.
Interpreting RDW values provides a dynamic view of erythropoiesis, the process of red blood cell production. A higher RDW suggests that newly formed red blood cells differ significantly in size from older red blood cells, indicating an underlying issue affecting red cell maturation or survival.
Interpreting Elevated RDW: Potential Clinical Implications
An elevated RDW, meaning the percentage is above the normal range, indicates a greater variation in the size of red blood cells, a condition known as anisocytosis. This finding is often the first clue to several underlying health conditions, prompting further investigation. Elevated RDW is frequently associated with various types of anemia but can also be an indicator of other systemic diseases.
Common Causes of High RDW
The most common reasons for an elevated RDW are conditions that affect red blood cell production, maturation, or survival. These include:
- Iron Deficiency Anemia: This is one of the most frequent causes of high RDW. As the body struggles to produce healthy red blood cells due to insufficient iron, it releases a mix of normally sized and smaller, iron-deficient cells, leading to increased size variation.
- Vitamin B12 Deficiency Anemia (Megaloblastic Anemia): A lack of vitamin B12 impairs DNA synthesis, leading to the production of abnormally large, immature red blood cells (macrocytes) alongside normal cells, resulting in a high RDW.
- Folate Deficiency Anemia: Similar to vitamin B12 deficiency, folate deficiency also causes megaloblastic anemia and an elevated RDW due to the production of diverse cell sizes.
- Mixed Deficiency Anemias: When a person has deficiencies in both iron and B12/folate, the body produces a highly varied population of red blood cells (both small and large), leading to a markedly high RDW.
- Hemolytic Anemias: These conditions involve the premature destruction of red blood cells. The bone marrow attempts to compensate by rapidly producing new, often immature, red blood cells of varying sizes, leading to increased RDW.
- Myelodysplastic Syndromes (MDS): These are a group of blood cancers where the bone marrow produces abnormal blood cells. The dysfunctional production often results in highly varied red blood cell sizes and shapes, thus an elevated RDW.
- Chronic Liver Disease: The liver plays a vital role in red blood cell production and maturation. Liver dysfunction can lead to changes in red blood cell morphology and an elevated RDW.
- Chronic Kidney Disease: Impaired kidney function can lead to reduced erythropoietin production, a hormone essential for red blood cell formation, contributing to anemia and potentially a high RDW.
RDW in Differentiating Anemia Types
One of the most valuable applications of RDW is its ability to help differentiate between various types of anemia, especially when considered alongside the MCV.
- Microcytic Anemias (low MCV):
- Iron Deficiency Anemia: Typically presents with low MCV and high RDW. This combination is a strong indicator of iron deficiency, as the body struggles to make hemoglobin, producing progressively smaller and more varied red cells.
- Thalassemia Trait (Minor): Often characterized by low MCV but usually a normal RDW. In thalassemia, the red blood cells are uniformly small due to a genetic defect affecting hemoglobin synthesis, but their size variation is minimal. This distinction is crucial to avoid unnecessary iron supplementation in thalassemia patients.
- Macrocytic Anemias (high MCV):
- Vitamin B12 or Folate Deficiency Anemia: Presents with high MCV and high RDW. The wide range of cell sizes, including large immature cells, increases the RDW.
- Normocytic Anemias (normal MCV):
- Anemia of Chronic Disease: Often presents with normal MCV and normal RDW. Inflammation typically suppresses red blood cell production uniformly.
- Early Iron Deficiency or Hemolytic Anemia: In the initial stages, these conditions might show a normal MCV but an elevated RDW, indicating that cell size variation is occurring before the average cell size changes significantly. This makes RDW an early and sensitive marker.
Beyond Anemia: Other Conditions Associated with High RDW
While RDW is primarily known for its role in anemia diagnosis, research has increasingly linked elevated RDW to a broader spectrum of health issues, including:
- Inflammatory Conditions: Chronic inflammation can affect red blood cell production and lead to a higher RDW.
- Cardiovascular Disease: Elevated RDW has been identified as an independent predictor of adverse outcomes in patients with heart failure, coronary artery disease, and stroke.
- Cancer: A high RDW can sometimes be observed in cancer patients, possibly due to chronic inflammation, nutritional deficiencies, or the direct effects of the cancer on the bone marrow. It has also been studied as a prognostic marker in various malignancies.
- Sepsis and Critical Illness: In critically ill patients, elevated RDW is associated with increased mortality, reflecting the systemic stress and dysregulation of erythropoiesis.
- Diabetes: Studies suggest a correlation between elevated RDW and poor glycemic control and increased risk of diabetes complications.
These associations highlight RDW as a general marker of overall health and chronic disease burden, not just a specific indicator of red blood cell disorders.
The Role of RDW in Comprehensive Blood Analysis
The RDW value, when considered in isolation, provides limited diagnostic information. Its true power emerges when it is interpreted in the context of a complete blood count (CBC) and other relevant clinical findings. It acts as a complementary tool, enriching the diagnostic algorithm for various conditions.
RDW in Conjunction with Other Indices
- MCV (Mean Corpuscular Volume): This is the most critical companion to RDW. MCV measures the average size of red blood cells.
- Low MCV, High RDW: Strongly suggestive of iron deficiency anemia.
- Low MCV, Normal RDW: Points towards thalassemia trait.
- Normal MCV, High RDW: Can indicate early iron deficiency, early vitamin B12/folate deficiency, mixed anemia, chronic liver disease, or myelodysplastic syndrome.
- Normal MCV, Normal RDW: Often seen in anemia of chronic disease, acute blood loss (if recent), or aplastic anemia.
- High MCV, High RDW: Characteristic of vitamin B12 or folate deficiency.
- High MCV, Normal RDW: May suggest aplastic anemia or pre-leukemia.
- Hemoglobin (Hb) and Hematocrit (Hct): These measurements confirm the presence and severity of anemia. RDW helps determine the likely cause once anemia is established.
- MCH (Mean Corpuscular Hemoglobin) and MCHC (Mean Corpuscular Hemoglobin Concentration): These reflect the average amount and concentration of hemoglobin in red blood cells. Abnormalities in these, combined with RDW and MCV, provide a more complete picture of red cell quality.
- Reticulocyte Count: This measures the number of immature red blood cells. An elevated reticulocyte count with a high RDW can indicate an active bone marrow response to hemolytic anemia or recent blood loss.
Clinical Utility and Diagnostic Pathways
The strategic use of RDW can streamline diagnostic pathways, guiding clinicians toward more specific and targeted investigations. For instance, in a patient presenting with microcytic anemia (low MCV), a high RDW immediately suggests iron deficiency, prompting iron studies (serum iron, ferritin, total iron-binding capacity). Conversely, a normal RDW in the same scenario would lead to further evaluation for thalassemia. This distinction is vital for appropriate treatment, as iron supplementation is harmful for thalassemia patients who are not iron deficient.
Furthermore, RDW can be a useful prognostic marker. In conditions like heart failure or kidney disease, an increasing RDW over time may indicate disease progression or increased risk of adverse events, prompting closer monitoring and management adjustments.

Low RDW: A Less Common Phenomenon
While an elevated RDW is a significant diagnostic finding, a low RDW is relatively uncommon and typically holds less clinical significance when considered alone. A low RDW implies that the red blood cells are exceptionally uniform in size, even more so than the average healthy individual. This can sometimes occur, but it is rarely indicative of a specific disease or pathology.
Generally, if other blood parameters (like hemoglobin, MCV, white blood cell count) are within normal ranges, a low RDW is usually not a cause for concern and often does not warrant further investigation. It might occasionally be observed in conditions like aplastic anemia or certain forms of thalassemia where red cell production is uniformly impaired, but in these cases, other more prominent abnormalities in the CBC would be the primary indicators. In most clinical settings, the focus remains overwhelmingly on high RDW values due to their strong correlation with various underlying diseases.