
Kernicterus is a devastating neurological complication of severe, untreated neonatal jaundice, a condition characterized by elevated levels of bilirubin in the bloodstream. While the term “kernicterus” itself refers to the yellowish staining of specific brain nuclei, the clinical syndrome it describes is a form of permanent brain damage. This damage is a direct consequence of bilirubin crossing the immature blood-brain barrier and accumulating in key areas of the brain, leading to irreversible neurological dysfunction. Understanding kernicterus requires delving into the physiology of bilirubin metabolism, the mechanisms of its neurotoxicity, the clinical presentation, diagnostic challenges, and the crucial preventative and therapeutic strategies.

The Physiology and Pathophysiology of Bilirubin
Bilirubin is a yellow pigment produced during the normal breakdown of heme, a component of red blood cells. This process primarily occurs in the reticuloendothelial system. Initially, bilirubin is unconjugated (indirect bilirubin), a lipid-soluble form that circulates in the blood bound to albumin. For excretion, unconjugated bilirubin must be transported to the liver, where it is conjugated with glucuronic acid by the enzyme uridine diphosphate-glucuronosyltransferase (UGT1A1) to become conjugated (direct bilirubin). Conjugated bilirubin is water-soluble and is then excreted into the bile, eventually eliminated from the body via the gastrointestinal tract.
In newborns, several factors contribute to an increased risk of hyperbilirubinemia (high bilirubin levels). These include a higher red blood cell turnover rate, a higher proportion of immature red blood cells (reticulocytes) that are more fragile, and a less mature hepatic conjugation system. UGT1A1 activity is significantly lower in neonates, particularly in the first few days of life. Furthermore, the neonatal blood-brain barrier is also more permeable than in adults, making the brain more vulnerable to circulating toxins like bilirubin.
When bilirubin levels rise to extremely high concentrations, the binding capacity of albumin can be overwhelmed. Unbound, unconjugated bilirubin, being lipid-soluble, can then readily cross the blood-brain barrier. Once in the brain, it preferentially deposits in specific areas rich in lipid tissues, including the basal ganglia, cerebellum, hippocampus, and brainstem nuclei. These nuclei are critical for motor control, auditory processing, and cognitive functions. The deposition of bilirubin in these neural structures causes neuronal damage, inflammation, and ultimately, cell death. This damage is often described as “bilirubin encephalopathy” in its acute phase and can lead to the permanent neurological sequelae of kernicterus.
Factors Contributing to Neonatal Hyperbilirubinemia
Several common conditions can exacerbate neonatal hyperbilirubinemia, increasing the risk of kernicterus:
- Physiological Jaundice: This is the most common type, occurring in approximately 60% of term infants and 80% of preterm infants during the first week of life. It is attributed to the immature hepatic conjugation system and increased red blood cell breakdown.
- Breastfeeding Jaundice: This type is associated with inadequate milk intake, leading to dehydration and delayed meconium passage, which can increase enterohepatic circulation of bilirubin.
- Breast Milk Jaundice: This is a less common, later-onset jaundice, typically appearing after the first week of life. The exact mechanism is not fully understood but may involve substances in breast milk that inhibit hepatic UGT1A1 activity or increase bilirubin absorption from the gut.
- Hemolytic Disease of the Newborn (HDN): This occurs when there is an incompatibility between the blood group of the mother and the baby, most commonly Rh incompatibility or ABO incompatibility. Maternal antibodies cross the placenta and attack the fetal red blood cells, leading to accelerated hemolysis and a rapid increase in bilirubin production.
- G6PD Deficiency: Glucose-6-phosphate dehydrogenase deficiency is an inherited enzyme disorder that makes red blood cells susceptible to oxidative stress. Certain triggers, such as infections or medications, can cause hemolysis and hyperbilirubinemia.
- Cephalohematoma and Bruising: Significant bruising or a cephalohematoma (a collection of blood under the scalp) represents a breakdown of red blood cells, releasing bilirubin that needs to be cleared by the infant’s system.
- Infection (Sepsis): Sepsis can impair hepatic function and increase red blood cell breakdown, contributing to hyperbilirubinemia.
- Prematurity: Premature infants have even more immature hepatic function and a more permeable blood-brain barrier, making them highly susceptible.
Clinical Manifestations of Kernicterus
Kernicterus is typically diagnosed retrospectively, meaning that the permanent neurological damage is recognized after the acute phase of severe jaundice has passed. The damage can manifest in a variety of ways, depending on the specific brain regions affected. The classic presentation of kernicterus, often referred to as chronic bilirubin encephalopathy, includes a characteristic set of neurological deficits.
Acute Bilirubin Encephalopathy
In the newborn period, severe hyperbilirubinemia can lead to acute bilirubin encephalopathy, which is a reversible condition if treated promptly. The signs and symptoms are often subtle at first and can progress rapidly:
- Mild Stage: Lethargy, poor feeding, hypotonia (decreased muscle tone), and irritability. The infant may appear “floppy” or excessively sleepy.
- Moderate Stage: Increased lethargy, fever, opisthotonos (arching of the back), retrocollis (arching of the neck), and a high-pitched cry. The infant may seem distressed and difficult to console.
- Advanced Stage: Profound lethargy or coma, absent reflexes, seizures (often characterized by opisthotonos and limb rigidity), and respiratory distress. In this advanced stage, the damage is often irreversible.
Chronic Bilirubin Encephalopathy (Kernicterus)
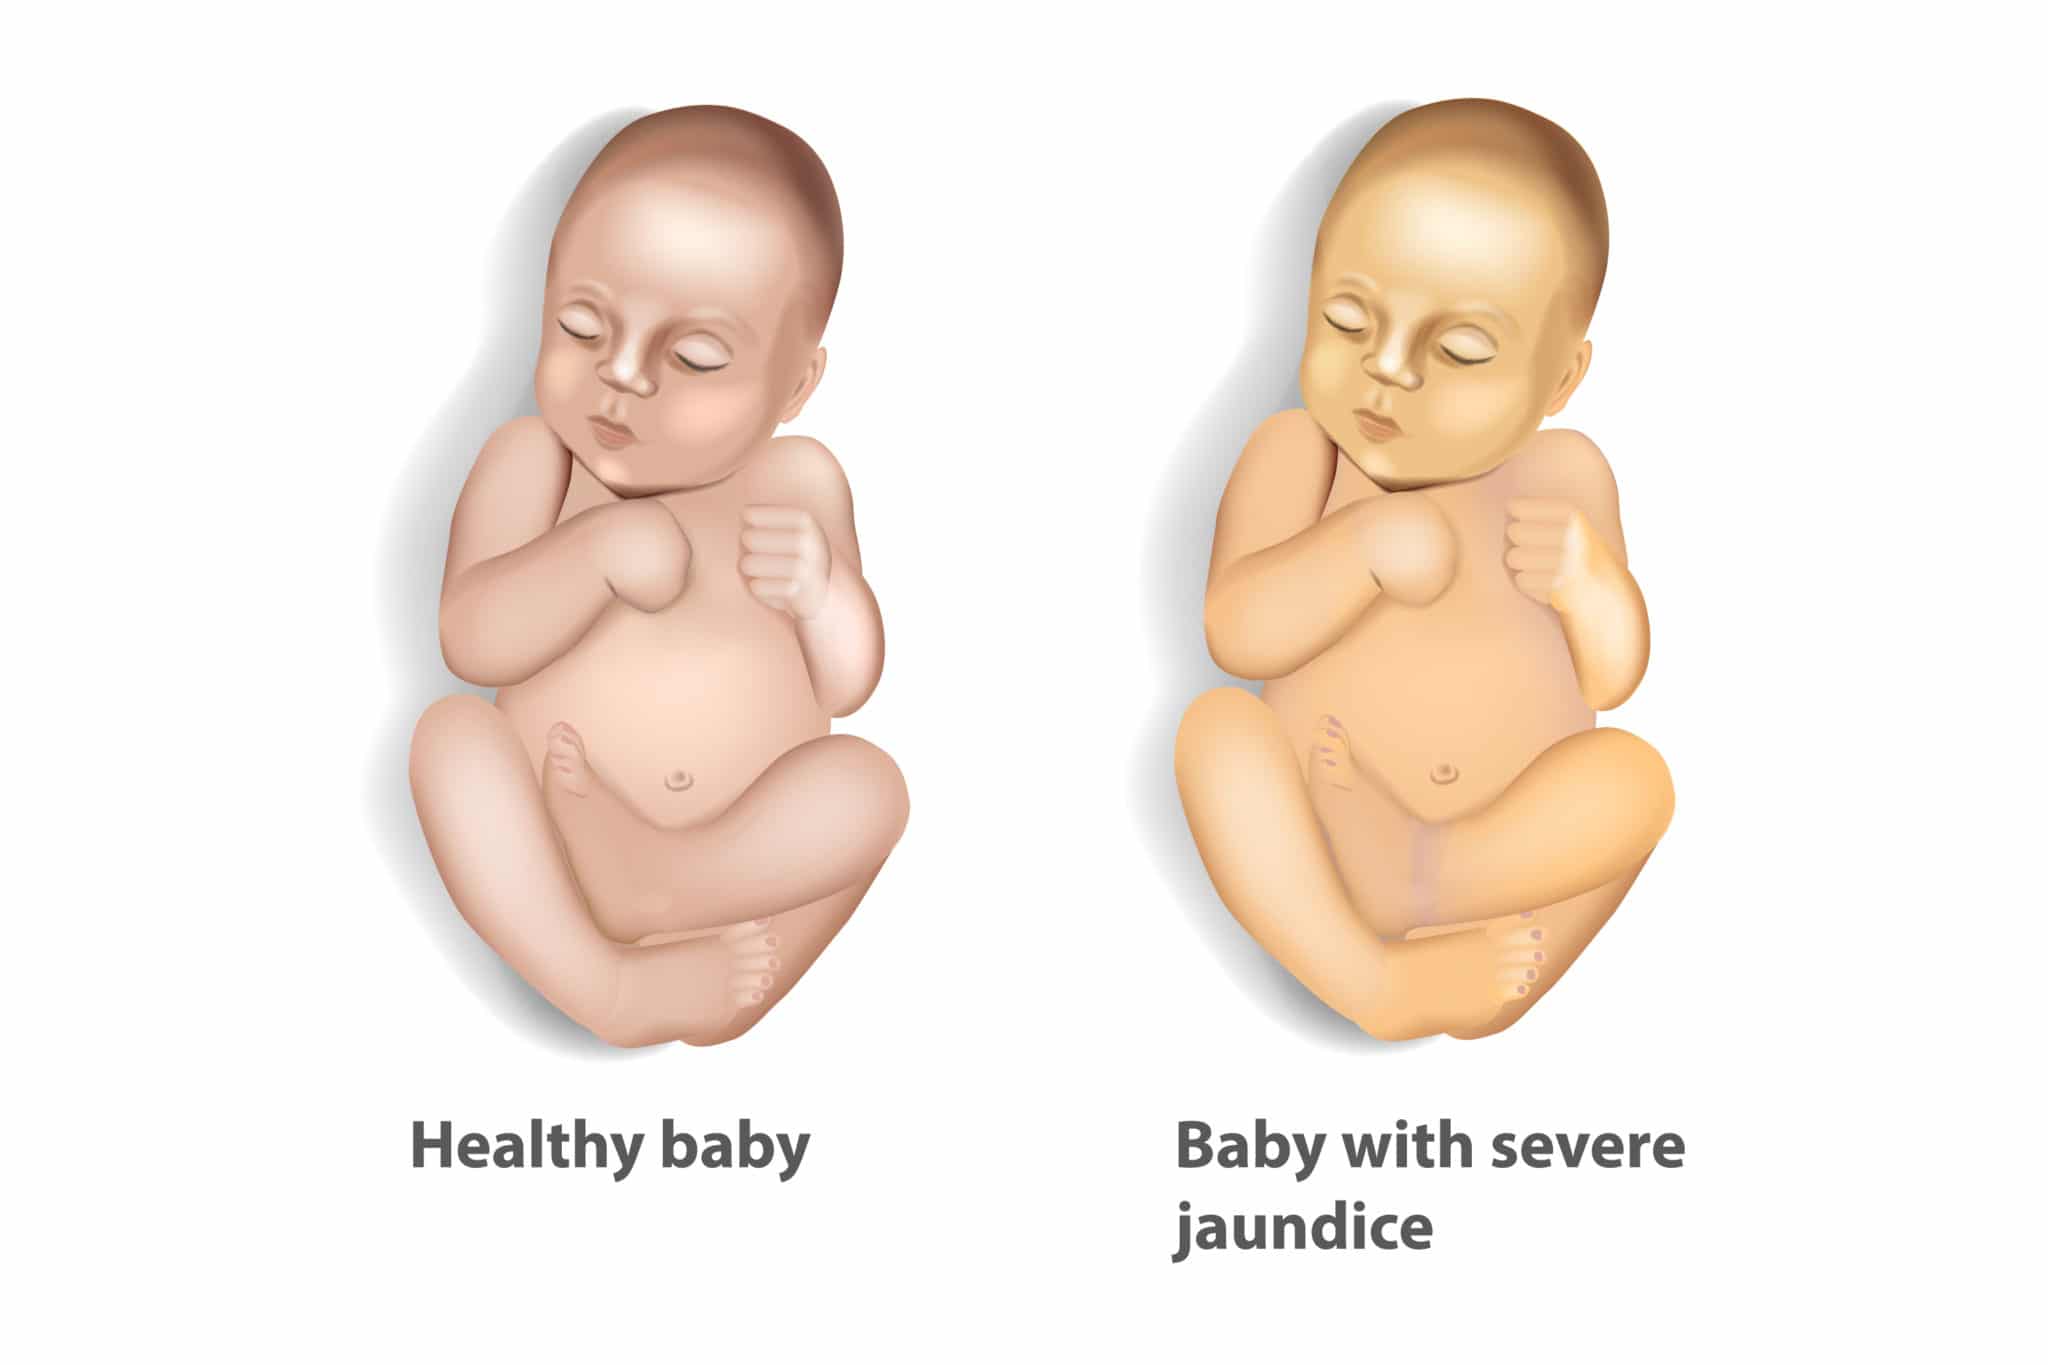
The chronic form of bilirubin encephalopathy, which is the hallmark of kernicterus, becomes apparent in infancy or later childhood. The neurological deficits are permanent and can significantly impact development and quality of life. The most commonly observed sequelae include:
- Auditory Neuropathy Spectrum Disorder (ANSD): This is a highly prevalent and often the first recognized symptom of kernicterus. It affects the auditory nerve and brainstem pathways, leading to hearing loss that can range from mild to profound. Infants may have normal outer ear function but struggle to process sounds, leading to difficulties with speech development.
- Motor Impairments:
- Extrapyramidal Cerebral Palsy (CP): This is the most characteristic motor deficit. It often involves choreoathetosis (involuntary, irregular, purposeless movements), dystonia (involuntary muscle contractions that cause repetitive or twisting movements), and spasticity. These movements can affect the limbs, trunk, and face, making voluntary movements difficult and impacting coordination.
- Ataxic CP: Less common but can occur, leading to problems with balance and coordination.
- Ocular Motor Impairments:
- Impaired Vertical Gaze: Difficulty moving the eyes upward is a hallmark. This can impact the ability to look up and follow moving objects.
- Strabismus (Crossed Eyes): Misalignment of the eyes is common.
- Dental Abnormalities: Enamel hypoplasia, particularly affecting the deciduous (baby) teeth, is frequently seen.
- Intellectual Disabilities: While not universally present, some individuals with kernicterus may experience mild to moderate intellectual disabilities. However, many have normal intelligence and can excel in areas not affected by their neurological deficits.
- Seizures: Recurrent seizures can occur in some individuals.
The constellation of these deficits, particularly the combination of auditory neuropathy and extrapyramidal cerebral palsy, is highly suggestive of kernicterus.
Diagnosis and Management
Diagnosing kernicterus is primarily a clinical diagnosis based on the characteristic neurological sequelae in an individual with a history of severe neonatal jaundice. There are no specific laboratory tests that can diagnose the chronic condition itself, as the damage has already occurred. The diagnosis is often made retrospectively by neurologists, developmental pediatricians, audiologists, and ophthalmologists.
Diagnostic Approaches
- Clinical Examination: A thorough neurological examination looking for the specific motor and ocular motor deficits described above is paramount.
- Auditory Evaluation: Auditory Brainstem Response (ABR) testing is crucial. In ANSD, the ABR typically shows absent or abnormal wave I (representing the auditory nerve) but present later waves, indicating that the problem lies in the auditory nerve or brainstem, not the inner ear. Otoacoustic emissions (OAEs), which assess the function of the outer hair cells in the cochlea, are often present in ANSD, further supporting the diagnosis.
- Neuroimaging: Magnetic Resonance Imaging (MRI) of the brain can reveal characteristic abnormalities in the globus pallidus and subthalamic nuclei, which are areas often affected by bilirubin deposition. These findings can support the diagnosis but are not always definitive.
- History Taking: A detailed history of the infant’s neonatal period, including the severity of jaundice, duration, and any treatment received, is vital.
Management and Prevention
The cornerstone of managing kernicterus is its prevention. Since the neurological damage is irreversible, all efforts must be focused on preventing severe hyperbilirubinemia in newborns.
Prevention Strategies:
- Early and Frequent Monitoring of Bilirubin Levels: All newborns should have their total serum bilirubin levels assessed, either transcutaneously or by blood test, within the first 24 hours of life and at regular intervals thereafter, based on risk factors and feeding status.
- Risk Assessment: Identifying infants at higher risk for severe hyperbilirubinemia before discharge is critical. This includes assessing gestational age, presence of bruising, blood group incompatibilities, history of sibling with jaundice, and feeding method.
- Timely Intervention for Hyperbilirubinemia:
- Phototherapy: This is the primary treatment for neonatal jaundice. It involves exposing the infant to specific wavelengths of light that convert unconjugated bilirubin into less toxic water-soluble photoproducts that can be excreted more easily. Phototherapy is initiated based on bilirubin nomograms that correlate bilirubin levels with age and risk factors.
- Exchange Transfusion: In cases of extremely high bilirubin levels that do not respond to phototherapy, or in the presence of significant hemolysis or signs of acute bilirubin encephalopathy, an exchange transfusion may be necessary. This procedure involves removing the infant’s blood and replacing it with donor blood, effectively reducing bilirubin levels and removing antibodies that might be causing hemolysis.
- Support for Breastfeeding: Promoting and supporting successful breastfeeding, including adequate latch and frequent feeding, is crucial to prevent breastfeeding jaundice. Lactation consultants and healthcare providers play a vital role in this.
- Phototherapy Protocols: Hospitals and healthcare facilities should have clear, evidence-based protocols for the management of neonatal jaundice, including guidelines for monitoring, treatment thresholds, and follow-up.

Management of Established Kernicterus:
Once kernicterus has occurred and the neurological damage is permanent, the management focuses on supportive care and rehabilitation to maximize the child’s functional abilities and quality of life.
- Multidisciplinary Rehabilitation: This involves a team of specialists including physical therapists, occupational therapists, speech-language pathologists, audiologists, ophthalmologists, and developmental pediatricians.
- Therapies:
- Physical Therapy: To manage spasticity, improve motor control, and enhance mobility.
- Occupational Therapy: To assist with fine motor skills, daily living activities, and adaptive equipment.
- Speech-Language Pathology: To address communication difficulties, feeding issues, and swallowing problems.
- Auditory Rehabilitation: Hearing aids, cochlear implants (in selected cases), and speech therapy are essential for individuals with ANSD.
- Visual Rehabilitation: Management of strabismus and other visual impairments.
- Seizure Management: Antiepileptic medications are used to control seizures if present.
- Educational Support: Tailored educational programs are necessary to support learning and cognitive development.
- Family Support: Families require extensive support, education, and resources to cope with the challenges of caring for a child with kernicterus.
In conclusion, kernicterus represents a tragic and entirely preventable form of brain damage resulting from severe neonatal hyperbilirubinemia. Its prevention hinges on vigilant monitoring, early recognition of jaundice, and timely, appropriate intervention. While the neurological sequelae are permanent, comprehensive rehabilitation and ongoing support can significantly improve the lives of affected individuals and their families. The ultimate goal remains the eradication of kernicterus through consistent application of established guidelines and a commitment to newborn health.