
Internuclear ophthalmoplegia (INO) is a neurological condition that affects eye movement coordination. It specifically impacts the connection between cranial nerves involved in directing the eyes. While not directly related to flight technology, understanding its neurological underpinnings offers a unique lens through which to appreciate the complex sensory processing and motor control systems that are also fundamental to advanced flight operations, particularly those involving sophisticated navigation and stabilization. This exploration delves into the nature of INO, its causes, symptoms, and diagnostic approaches, drawing parallels to the intricate control mechanisms seen in high-performance unmanned aerial vehicles (UAVs).

Understanding the Neurological Basis of Eye Movement
The ability to move our eyes precisely and smoothly is a marvel of biological engineering. It involves a delicate interplay of multiple cranial nerves and brainstem pathways. When we look from one object to another, or track a moving target, a coordinated effort between both eyes is essential for binocular vision and depth perception. Internuclear ophthalmoplegia disrupts this coordination, primarily affecting the conjugate movement of the eyes, which is the synchronized movement of both eyes in the same direction.
The Medial Longitudinal Fasciculus (MLF)
At the heart of INO lies damage to a crucial neural pathway called the medial longitudinal fasciculus (MLF). The MLF is a paired bundle of nerve fibers that runs through the brainstem, playing a vital role in connecting various nuclei responsible for eye movements. Specifically, it links the nucleus of the abducens nerve (cranial nerve VI), which controls outward eye movement (abduction), with the oculomotor nucleus (cranial nerve III), which controls inward eye movement (adduction) and other functions like pupillary constriction and eyelid elevation.
When an individual attempts to move their eyes horizontally, say from a central point to the right, the brain sends signals. The left abducens nucleus stimulates the left lateral rectus muscle to move the left eye outward, while simultaneously, signals are relayed via the MLF to the right oculomotor nucleus, exciting the right medial rectus muscle to move the right eye inward. This coordinated action ensures both eyes remain converged on the target. In INO, damage to the MLF disrupts this communication, leading to impaired adduction in one eye when the other eye abducts. This disruption, while neurological, highlights the critical importance of robust and reliable neural pathways for precise, coordinated, and responsive motor control – principles that are mirrored in the design of advanced flight control systems in UAVs.
Cranial Nerves Involved
The primary cranial nerves involved in INO are the abducens nerve (CN VI) and the oculomotor nerve (CN III).
- Abducens Nerve (CN VI): This nerve originates in the pons, a part of the brainstem. It innervates the lateral rectus muscle of the eye, which is responsible for pulling the eyeball outwards, away from the nose (abduction).
- Oculomotor Nerve (CN III): This nerve originates in the midbrain. It has a more extensive role, innervating most of the muscles of the eye, including the medial rectus muscle (responsible for inward movement, or adduction), the superior rectus muscle (upward movement), the inferior rectus muscle (downward movement), and the inferior oblique muscle (extorsion and elevation). It also controls the levator palpebrae superioris muscle (raising the eyelid) and the intrinsic muscles of the eye, the pupillary sphincter (pupil constriction) and the ciliary muscle (lens accommodation).
In INO, the damage to the MLF affects the signals that should normally coordinate the action of these nerves. For instance, when attempting to look to the right, the left eye’s ability to abduct (controlled by CN VI) is generally preserved. However, the signal to the right eye’s medial rectus muscle (controlled by CN III) to adduct inward, ensuring both eyes follow the target, is impaired due to the damaged MLF connection.
Clinical Manifestations of Internuclear Ophthalmoplegia
The symptoms of INO can vary in severity and presentation, but they primarily manifest as deficits in eye movement. The hallmark signs are typically observed during horizontal gaze.
Impaired Adduction and Abducting Nystagmus
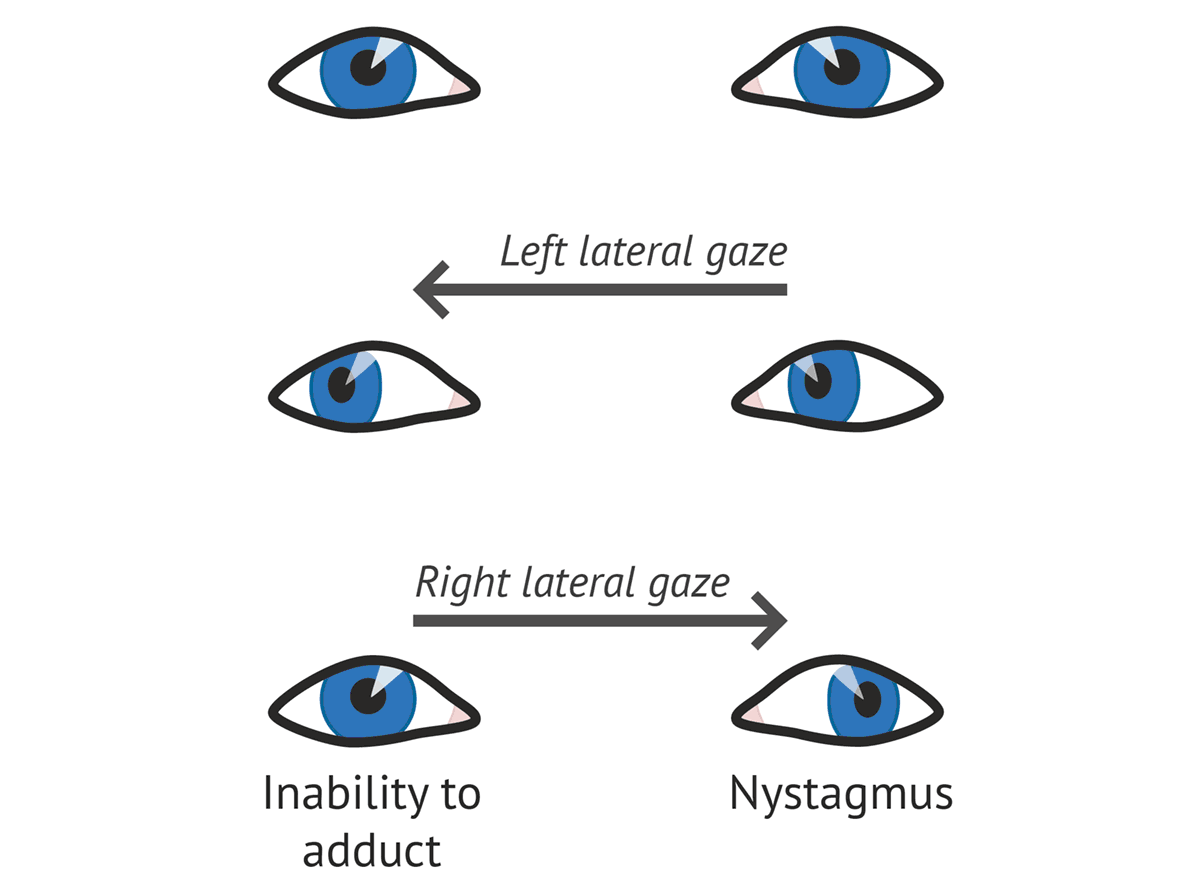
The most characteristic finding in INO is the inability of one eye to fully adduct (move inward) when the other eye abducts (moves outward). For example, if a person with INO tries to look to the right, their right eye may be unable to move fully towards the nose, while the left eye can abduct normally. Conversely, if they try to look to the left, the left eye’s adduction might be impaired, while the right eye abducts.
Furthermore, a peculiar phenomenon known as “abducting nystagmus” is often observed. This refers to a jerky, involuntary movement of the eye that is attempting to abduct. While the abducted eye might achieve some outward movement, it often oscillates or trembles. This nystagmus is typically transient and less pronounced than the adduction deficit. This visual disruption, where one eye struggles to follow a target while the other may exhibit instability, underscores the sophisticated interdependencies in sensory-motor systems, similar to how a drone’s flight stabilization system relies on precise sensor fusion and actuator response.
Diplopia (Double Vision)
The most bothersome symptom for individuals with INO is often diplopia, or double vision. This occurs because the brain receives two different images from each eye, which it cannot effectively fuse into a single, coherent image. The diplopia is typically worse when attempting to gaze in the direction that elicits the adduction deficit. For instance, if looking to the right causes the right eye’s adduction to fail, the individual may experience double vision in that direction. The severity of the diplopia can fluctuate depending on the gaze direction and the extent of the MLF lesion.
Other Potential Symptoms
While impaired adduction and diplopia are the most common symptoms, INO can sometimes be accompanied by other eye movement abnormalities, depending on the specific location and extent of the lesion within the brainstem. These might include:
- Impaired Vertical Gaze: In some cases, lesions affecting broader areas of the brainstem can impact vertical eye movements as well.
- Convergence Insufficiency: Convergence is the inward movement of both eyes when focusing on a near object. Damage to the MLF or related structures can sometimes impair this ability, leading to difficulty focusing on close-up tasks.
- Internuclear Ophthalmoplegia with Ipsilateral Paretic Nystagmus: In certain types of INO, a small nystagmus may be present in the abducting eye, which is termed ipsilateral paretic nystagmus.
Etiology: Causes of Internuclear Ophthalmoplegia
Internuclear ophthalmoplegia is not a disease in itself but rather a symptom of an underlying neurological disorder. The damage to the MLF can be caused by a variety of conditions that affect the brainstem.
Multiple Sclerosis (MS)
Multiple sclerosis is one of the most common causes of INO, particularly in younger adults. MS is an autoimmune disease that attacks the myelin sheath, the protective covering of nerve fibers, in the central nervous system. Lesions in the brainstem, specifically affecting the MLF, are frequent manifestations of MS and can lead to INO. The unpredictable nature of MS lesions mirrors how unpredictable environmental factors or system failures can affect the precise functioning of a drone’s navigation systems.
Stroke
Vascular events, such as strokes, are another significant cause of INO, especially in older individuals. A stroke occurs when blood flow to a part of the brain is interrupted, leading to cell death. Ischemic strokes (caused by a blockage) or hemorrhagic strokes (caused by bleeding) in the brainstem, particularly affecting the area where the MLF is located, can result in INO. The sudden onset of symptoms is a hallmark of stroke-related INO.
Tumors
Brain tumors, whether primary (originating in the brain) or metastatic (spreading from elsewhere), can compress or invade the brainstem, damaging the MLF and causing INO. The location and size of the tumor will determine the specific neurological deficits.
Other Causes
A range of other conditions can also lead to INO, including:
- Inflammatory Conditions: Certain inflammatory diseases affecting the central nervous system, besides MS, can also cause MLF lesions.
- Traumatic Brain Injury: Severe head trauma can sometimes result in brainstem damage and INO.
- Syphilis: Neurosyphilis, a late-stage complication of syphilis, can affect the nervous system and lead to various neurological deficits, including INO.
- Certain Medications and Toxins: In rare instances, certain drugs or toxins may have neurotoxic effects that can impact brainstem function.
Diagnosis and Management of Internuclear Ophthalmoplegia
Diagnosing INO involves a thorough neurological examination and appropriate imaging studies to identify the underlying cause. Management strategies are then tailored to the specific etiology.
Neurological Examination
A comprehensive neurological examination is the cornerstone of INO diagnosis. The clinician will meticulously assess:
- Eye Movements: This involves observing the patient’s ability to move their eyes in all directions, looking for the characteristic impaired adduction and abducting nystagmus. The examiner will also assess for the presence and direction of diplopia.
- Cranial Nerve Function: Other cranial nerves are tested to rule out broader neurological involvement.
- Motor and Sensory Function: Assessment of strength, coordination, and sensation helps to localize the lesion within the nervous system.
Imaging Studies
To pinpoint the location of the MLF lesion and identify the underlying cause, imaging techniques are crucial:
- Magnetic Resonance Imaging (MRI): MRI of the brain, particularly with specific sequences designed to visualize the brainstem, is the most sensitive imaging modality for detecting lesions affecting the MLF. It can effectively identify demyelinating lesions (as in MS), strokes, tumors, or other structural abnormalities.
- Computed Tomography (CT) Scan: While less sensitive than MRI for subtle brainstem lesions, a CT scan may be used in emergency situations or when MRI is contraindicated to detect larger lesions like hemorrhagic strokes or tumors.

Treatment and Management
The treatment of INO is directed at the underlying cause.
- For Multiple Sclerosis: Treatment focuses on managing MS itself with disease-modifying therapies and addressing acute relapses with corticosteroids.
- For Stroke: Management involves acute stroke treatment to restore blood flow (e.g., thrombolysis) and secondary prevention strategies to reduce the risk of future strokes.
- For Tumors: Treatment may involve surgery, radiation therapy, or chemotherapy, depending on the type and location of the tumor.
- Symptomatic Relief: While the underlying cause is treated, symptomatic management for diplopia may include:
- Prism Lenses: Specially designed glasses with prisms can help realign the images from the two eyes, reducing or eliminating double vision.
- Patching: In some cases, covering one eye can alleviate diplopia, although this sacrifices binocular vision.
- Vision Therapy: In certain instances, eye exercises and visual training may be beneficial.
The prognosis for INO varies widely depending on the cause. In some cases, particularly with MS or small ischemic strokes, recovery can be partial or complete. However, more extensive lesions or certain underlying conditions may lead to persistent deficits. The intricate neurological pathways governing eye movements, as exemplified by INO, serve as a testament to the complexity and robustness required for precise sensory processing and motor control, echoing the design principles found in advanced flight technology.