
The experience of passing blood clots during menstruation is a common one for many individuals, yet it often sparks concern and questions about their normalcy and potential implications. While the presence of small clots is typically a benign physiological event, understanding their formation, composition, and when they might signal a medical concern is crucial for informed health management. This exploration delves into the intricacies of menstrual blood clots, demystifying their nature and providing insights into their significance.
The Physiology of Menstruation and Clot Formation
Menstruation, the monthly shedding of the uterine lining (endometrium), is a complex hormonal process. When pregnancy does not occur, hormonal signals trigger the breakdown and shedding of this nutrient-rich tissue, accompanied by blood and cervical mucus. The blood that exits the body during a period is not merely liquid; it contains the shed endometrial tissue, other cellular debris, and various proteins.
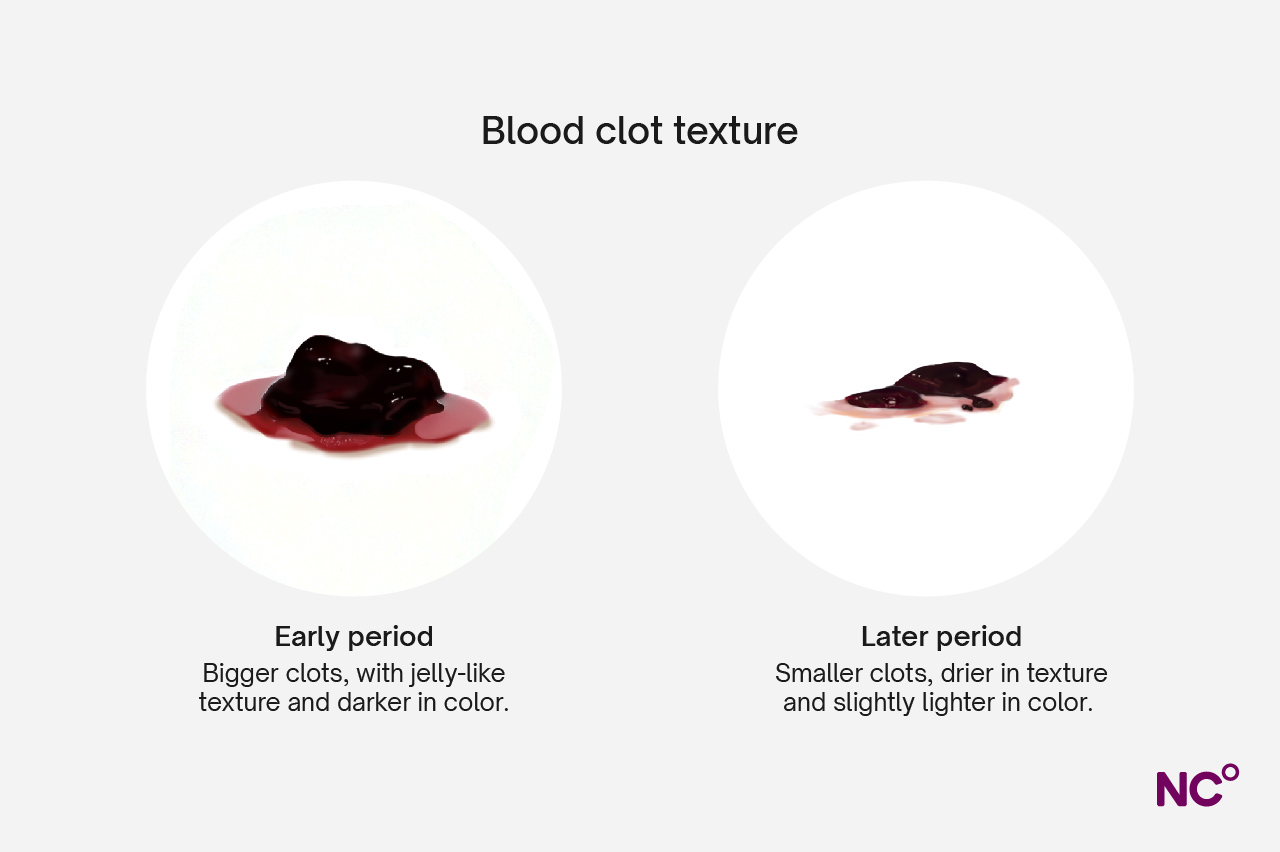
The body has natural anticoagulants present in menstrual fluid that typically prevent excessive clotting. However, under certain circumstances, these anticoagulants may be overwhelmed, or the rate of blood flow may exceed their capacity to act effectively. This leads to the formation of blood clots.
Endometrial Shedding and Tissue Breakdown
The endometrium is a dynamic tissue that thickens throughout the menstrual cycle in preparation for a potential pregnancy. It is richly supplied with blood vessels to nourish an early embryo. If fertilization and implantation do not occur, the hormonal support for the endometrium, primarily from estrogen and progesterone, declines. This hormonal shift initiates a cascade of events, including the release of prostaglandins.
Prostaglandins play a critical role in menstruation by causing the uterine muscles to contract, which helps to expel the uterine lining. They also influence blood flow to the uterus and can contribute to pain. The breakdown of the endometrial tissue releases various components, including cells, proteins, and blood.
The Role of Anticoagulants and When They Are Overwhelmed
The body naturally produces anticoagulants to prevent blood from clotting excessively within blood vessels. These substances, such as heparin and antithrombin, are also present in menstrual blood. Their function is to break down fibrin, a protein that forms the meshwork of a blood clot.
However, during heavy menstrual bleeding, the sheer volume of blood and shed tissue can overwhelm the body’s natural anticoagulant mechanisms. If blood remains in the uterus for a period of time before being expelled, it has more opportunity to coagulate. The uterine environment itself, with its muscular contractions and shedding of tissue, can also contribute to the formation and retention of clots.
The size and frequency of clots can vary significantly among individuals and even from cycle to cycle for the same person. Small, jelly-like clots are generally considered a normal part of menstruation for many. However, larger or more frequent clots, especially those accompanied by other symptoms, warrant further medical evaluation.
Factors Influencing Blood Clot Size and Frequency
Several physiological and hormonal factors can influence the size and frequency of blood clots experienced during menstruation. Understanding these influences can help individuals better interpret their menstrual patterns.
Hormonal Fluctuations and Imbalances
Hormonal imbalances, particularly those involving estrogen and progesterone, can significantly impact the menstrual cycle and the expulsion of the uterine lining. Conditions such as polycystic ovary syndrome (PCOS) or perimenopause can lead to irregular ovulation and consequently, irregular or heavier bleeding, which may increase the likelihood of clot formation.
An excess of estrogen relative to progesterone, often termed estrogen dominance, can lead to a thicker, more proliferative endometrium. A thicker lining means more tissue to shed, potentially resulting in heavier bleeding and a greater chance of clots. Conversely, insufficient progesterone can lead to breakthrough bleeding and a less stable uterine lining.
Uterine Contractions and Blood Retention
The muscular contractions of the uterus, stimulated by prostaglandins, are essential for expelling menstrual blood and tissue. However, if these contractions are not strong enough, or if there is an obstruction within the uterine cavity, blood can pool and clot. Conditions that affect uterine motility or structure, such as uterine fibroids or polyps, can impede the efficient emptying of the uterus, leading to prolonged blood retention and clot formation.
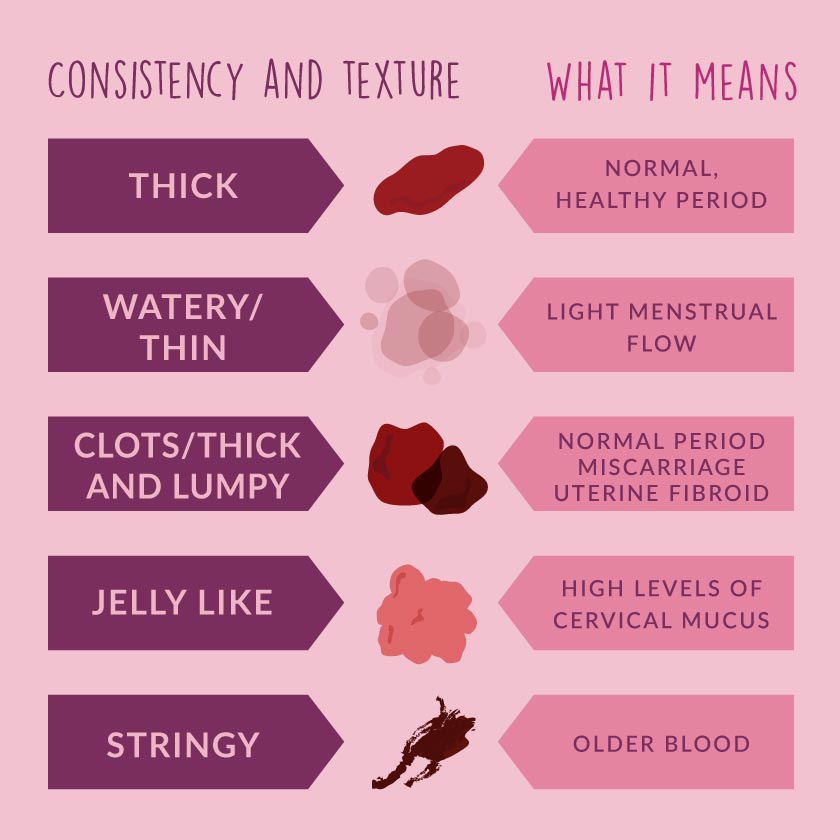
Uterine fibroids, non-cancerous growths in the uterine wall, are a common cause of heavy and painful periods, often associated with an increased incidence of blood clots. These fibroids can distort the uterine cavity, disrupt blood flow, and increase the surface area from which bleeding occurs. Endometrial polyps, small growths in the uterine lining, can also contribute to abnormal bleeding patterns and increased clotting.
Endometrial Thickness and Menstrual Flow
The thickness of the endometrium directly correlates with the amount of tissue to be shed during menstruation. A thicker lining, as mentioned, can lead to heavier bleeding and a greater propensity for clot formation. The rate of menstrual flow also plays a role; rapid bleeding that overwhelms the body’s anticoagulants is more likely to result in clots.
Some individuals naturally have a thicker endometrium or experience heavier menstrual flows. This can be influenced by genetics, body mass index, and other underlying health conditions. It is important to distinguish between a consistently heavy flow with clots that is within an individual’s normal range and a sudden increase in heaviness or clot size.
When to Seek Medical Advice for Menstrual Clots
While passing small blood clots during menstruation is usually normal, there are specific circumstances and accompanying symptoms that warrant a consultation with a healthcare professional. Recognizing these red flags is essential for timely diagnosis and management of potential underlying conditions.
Excessive Bleeding and Large Clots
A significant indicator that menstrual clots may be problematic is the volume of bleeding and the size of the clots. If individuals are passing clots larger than a quarter or experiencing bleeding that is so heavy they need to change pads or tampons every hour for several consecutive hours, this is considered excessive and should be evaluated. The presence of numerous large clots throughout the period is also a cause for concern.
Doctors often use the term “menorrhagia” to describe excessively heavy menstrual bleeding. This can be disruptive to daily life and can lead to anemia, a condition characterized by a low red blood cell count due to iron deficiency. Anemia can cause fatigue, weakness, shortness of breath, and pale skin.
Associated Symptoms and Potential Underlying Conditions
Beyond the clots themselves, the presence of other symptoms can signal an underlying issue. Severe pelvic pain that is not relieved by over-the-counter pain medication, pain that is significantly worse than usual menstrual cramps, or pain that occurs outside of menstruation should be investigated. Prolonged periods, lasting more than seven days, can also be indicative of a problem.
Several gynecological conditions can manifest with heavy bleeding and large blood clots. These include:
- Uterine Fibroids: Benign tumors in the uterus that can cause heavy, prolonged, and painful periods.
- Endometrial Polyps: Small growths on the uterine lining that can cause irregular bleeding and heavier periods.
- Adenomyosis: A condition where the tissue that normally lines the uterus grows into the muscular wall of the uterus, leading to heavy, painful periods.
- Endometriosis: A condition where tissue similar to the lining of the uterus grows outside the uterus, which can cause painful periods, heavy bleeding, and sometimes infertility.
- Bleeding Disorders: Though less common, inherited bleeding disorders like von Willebrand disease can affect blood clotting and lead to heavy menstrual bleeding.
- Hormonal Imbalances: Conditions like PCOS or thyroid disorders can disrupt the menstrual cycle and lead to abnormal bleeding patterns.
- Miscarriage: In early pregnancy, heavy bleeding and large clots can be a sign of a miscarriage.

Diagnostic Approaches and Treatment Options
When evaluating menstrual clots and heavy bleeding, healthcare providers will typically start with a detailed medical history and a physical examination, including a pelvic exam. Depending on the initial assessment, further diagnostic tests may be recommended.
- Transvaginal Ultrasound: This imaging technique provides detailed images of the uterus, ovaries, and fallopian tubes, allowing for the detection of fibroids, polyps, or other structural abnormalities.
- Blood Tests: These can be used to check for anemia, iron levels, thyroid function, hormone levels, and to screen for bleeding disorders.
- Saline Infusion Sonohysterography (SIS): A procedure where saline is infused into the uterus during an ultrasound to better visualize the uterine cavity and identify any abnormalities like polyps or submucosal fibroids.
- Hysteroscopy: A procedure where a thin, lighted instrument is inserted into the uterus to directly view the uterine lining and remove any polyps or small fibroids.
- Biopsy: In some cases, a sample of the uterine lining may be taken for examination to rule out precancerous or cancerous changes.
Treatment options for problematic menstrual clots and heavy bleeding depend entirely on the underlying cause. They can range from conservative management to surgical interventions:
- Medications:
- Hormonal Contraceptives: Birth control pills, patches, rings, or hormonal IUDs can help regulate the menstrual cycle, reduce the thickness of the uterine lining, and decrease bleeding and clotting.
- Nonsteroidal Anti-inflammatory Drugs (NSAIDs): Medications like ibuprofen or naproxen can help reduce prostaglandin levels, which can decrease uterine cramping and bleeding.
- Tranexamic Acid: This medication helps to stabilize fibrin and reduce bleeding.
- Minimally Invasive Procedures:
- Endometrial Ablation: A procedure to destroy the uterine lining, significantly reducing or stopping menstrual bleeding. This is usually considered for women who do not wish to have future pregnancies.
- Uterine Artery Embolization (UAE): For fibroids, this procedure blocks the blood supply to the fibroids, causing them to shrink.
- Surgery:
- Myomectomy: Surgical removal of uterine fibroids.
- Hysterectomy: Surgical removal of the uterus, which is a definitive treatment for heavy bleeding but also means the end of fertility.
By understanding the normal physiological processes of menstruation and the factors that can lead to the formation of blood clots, individuals can better advocate for their health and seek appropriate medical attention when necessary. Open communication with healthcare providers is paramount to addressing concerns and ensuring optimal well-being.