
The Endometrium: A Dynamic Micro-Environment Crucial for Reproduction
The human body is a marvel of intricate biological systems, each playing a vital role in maintaining life and ensuring continuity. Among these, the female reproductive system stands out for its profound complexity and its central role in procreation. At the heart of this system lies the uterus, a muscular organ designed to nurture a developing fetus. Crucially, the inner lining of this organ, known as the endometrium, is a dynamic and exquisitely regulated tissue that undergoes remarkable transformations throughout a woman’s reproductive life. Far from being a static structure, the uterine lining is a highly responsive micro-environment, meticulously prepared each month to receive a potential embryo. Understanding the endometrium is key to comprehending the intricacies of the menstrual cycle, implantation, pregnancy, and various reproductive health conditions.
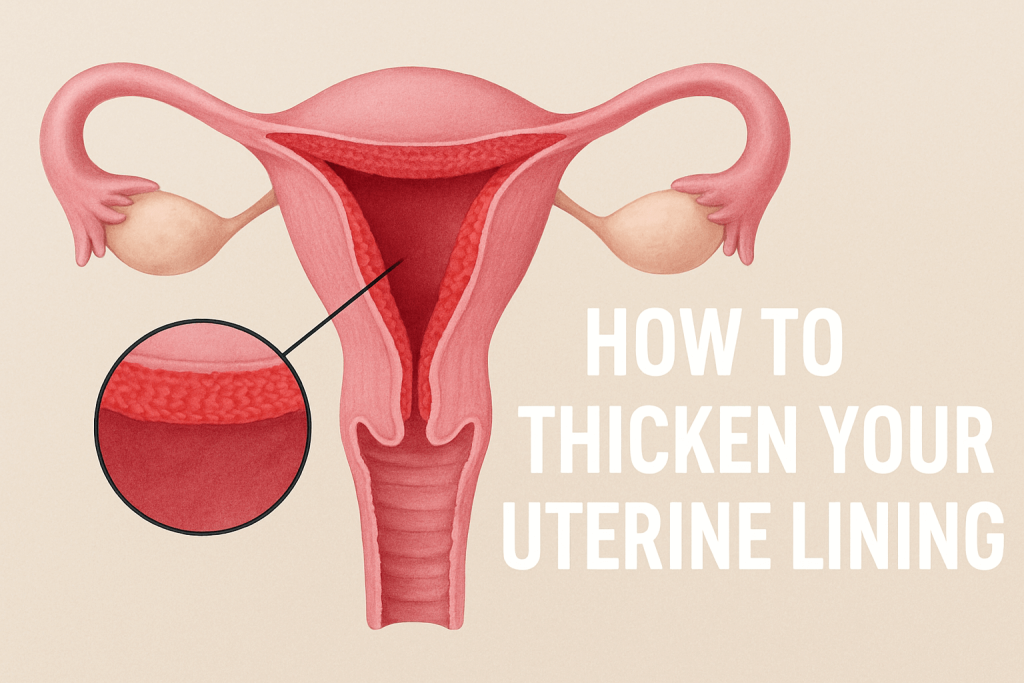
Structure and Composition of the Endometrium
The endometrium is a mucosal layer lining the inner surface of the uterus. It is not a uniform tissue but rather comprises two distinct layers, each with a specific function and histological characteristic.
The Basal Layer (Stratum Basalis)
This deeper layer of the endometrium is permanent and lies adjacent to the myometrium, the muscular wall of the uterus. The basal layer is rich in stem cells and possesses a dense connective tissue stroma, containing numerous blood vessels, nerves, and lymphatic channels. Its primary role is to regenerate the functional layer after menstruation. It contains the openings of the uterine glands and the bases of the spiral arteries. Unlike the functional layer, the basal layer is not shed during menstruation.
The Functional Layer (Stratum Functionalis)
Superficially located, the functional layer is the part of the endometrium that undergoes cyclical changes in response to ovarian hormones, primarily estrogen and progesterone. This layer is shed during menstruation if pregnancy does not occur. The functional layer itself has two sub-layers:
-
Stratum Compactum: This is the uppermost part of the functional layer, characterized by the presence of the openings of the uterine glands, which appear as small, round structures embedded in a cellular stroma. The stroma in this region is relatively cellular, with elongated fibroblast-like cells.
-
Stratum Spongiosum: Located beneath the stratum compactum, this layer is more loosely arranged and contains the coiled portions of the uterine glands, which are tortuous and tubular. The extracellular matrix here is more abundant and less cellular compared to the stratum compactum.
The endometrial glands, which are simple tubular glands, are a crucial component of both layers. Their morphology and secretory activity vary significantly throughout the menstrual cycle, reflecting the hormonal influences. The stroma is populated by fibroblasts, immune cells, and extracellular matrix components, all of which contribute to the tissue’s structural integrity and its dynamic remodeling capabilities. The endometrium is also highly vascularized, with a rich network of blood vessels, including straight arteries in the basal layer and coiled spiral arteries that extend into the functional layer. These spiral arteries are particularly important for supplying nutrients and oxygen to the endometrium and are essential for successful implantation and placental development.
Hormonal Regulation: The Orchestration of Cyclical Changes
The most striking characteristic of the endometrium is its cyclical transformation, orchestrated by a complex interplay of hormones, primarily estrogen and progesterone, regulated by the hypothalamic-pituitary-ovarian axis. These hormonal fluctuations dictate the endometrium’s readiness for implantation.
The Follicular Phase (Proliferative Phase)
During the follicular phase of the menstrual cycle, which begins on the first day of menstruation and lasts until ovulation, the ovaries are stimulated by follicle-stimulating hormone (FSH) to develop ovarian follicles. As these follicles grow, they produce increasing amounts of estrogen. Estrogen acts directly on the endometrium, stimulating cell proliferation in the basal layer and causing the uterine glands to elongate and the stroma to thicken. This phase is characterized by rapid growth and repair of the endometrium, hence the name “proliferative phase.” The endometrium rebuilds itself after shedding, becoming progressively thicker and more vascularized. The glands are straight and narrow during this period, and the spiral arteries begin to develop.
The Luteal Phase (Secretory Phase)
Following ovulation, which is triggered by a surge in luteinizing hormone (LH), the ruptured follicle transforms into the corpus luteum. The corpus luteum produces progesterone, in addition to estrogen. Progesterone is the dominant hormone of the luteal phase. Its effects on the endometrium are profound and distinct from those of estrogen.
-
Glandular Secretion: Progesterone stimulates the uterine glands to become coiled and secretory. They begin to release glycogen-rich mucus, transforming the endometrium into a nutrient-rich environment receptive to implantation. This is why it’s called the “secretory phase.”
-
Stromal Edema: The stromal cells swell, and the extracellular matrix becomes more edematous, creating a soft, spongy tissue.
-
Vascularization: The spiral arteries continue to develop and become more prominent, ensuring adequate blood supply to the receptive endometrium.
-
Decidualization: Under the influence of progesterone, stromal cells differentiate into decidual cells, a process known as decidualization. These decidual cells are larger and laden with glycogen and lipids, providing a supportive environment for early embryonic development.
The endometrium reaches its maximal thickness and secretory capacity in the mid-luteal phase, approximately 7-10 days after ovulation, representing the “window of implantation,” the optimal period for an embryo to successfully implant.

Menstruation: Shedding the Unused Lining
If fertilization and implantation do not occur, the corpus luteum begins to degenerate towards the end of the luteal phase. This decline in progesterone and estrogen levels triggers a cascade of events leading to menstruation.
-
Vasoconstriction: The sudden drop in hormones causes the spiral arteries to constrict, reducing blood flow to the functional layer.
-
Ischemia and Necrosis: The lack of oxygen and nutrients leads to the breakdown (necrosis) of the functional layer.
-
Hormonal Withdrawal: The withdrawal of progesterone and estrogen also triggers the release of inflammatory mediators and enzymes that break down the extracellular matrix, further contributing to tissue shedding.
-
Shedding: The functional layer, along with blood and debris, is expelled from the uterus through the vagina as menstrual flow. The basal layer, containing the stem cells and the bases of the glands and arteries, remains intact to initiate the regrowth of the functional layer in the next cycle.
Implantation and Pregnancy: The Endometrium as a Nurturing Ground
The endometrium plays an indispensable role in the establishment and maintenance of pregnancy.
Implantation
For successful implantation, the embryo, now a blastocyst, must arrive in the uterus at the appropriate time and encounter an endometrium that is receptive. This receptivity is a transient window, primarily dictated by hormonal cues. The blastocyst interacts with the endometrial epithelium, initiating a series of molecular events that allow it to attach, invade, and establish a connection with the maternal blood supply. The decidualized endometrium provides essential nutrients and signals for the developing embryo.
Placental Development
As pregnancy progresses, the endometrium undergoes further significant transformations to support the growing fetus. The decidua, formed from the transformed endometrium, becomes an integral part of the placenta. The maternal side of the placenta, the decidua basalis, is where the fetal chorionic villi embed. This intimate interface allows for the exchange of gases, nutrients, and waste products between the mother and the fetus. The blood vessels within the decidua, including the spiral arteries, are remodeled and adapted to supply the demands of the growing placenta and fetus.
Endometrial Disorders: When the Lining Goes Awry
Disruptions in the normal structure, function, or hormonal regulation of the endometrium can lead to various reproductive health issues.
-
Endometriosis: This condition is characterized by the presence of endometrial-like tissue outside the uterus, often on the ovaries, fallopian tubes, or pelvic peritoneum. This ectopic tissue responds to hormonal cycles, causing inflammation, pain, and potential infertility.
-
Endometrial Polyps: These are benign, overgrowths of endometrial tissue that can cause abnormal uterine bleeding, such as heavy or irregular periods.
-
Uterine Fibroids (Leiomyomas): While primarily originating in the myometrium, large fibroids can distort the uterine cavity and affect the endometrium, leading to bleeding irregularities and impacting fertility.
-
Endometrial Hyperplasia: This is a precancerous condition characterized by excessive thickening of the endometrium, often due to prolonged unopposed estrogen exposure. It can progress to endometrial cancer if left untreated.
-
Endometrial Cancer: This is the most common gynecological cancer in developed countries. It arises from the abnormal proliferation of endometrial cells, often driven by hormonal imbalances and genetic factors.
-
Asherman’s Syndrome: This condition involves the formation of intrauterine adhesions or scar tissue, typically after surgical procedures like dilation and curettage. It can lead to menstrual irregularities, infertility, and recurrent miscarriages by impairing the endometrium’s ability to respond to hormones.
-
Implantation Failure and Recurrent Miscarriage: Defects in endometrial receptivity, due to hormonal imbalances, immune system dysregulation, or structural abnormalities, can contribute to difficulties in achieving pregnancy or maintaining early pregnancies.

The Endometrium: A Window into Female Health
The endometrium is a testament to the body’s intricate design, a dynamic tissue that orchestrates critical events in reproduction. Its cyclical transformations, driven by precise hormonal control, prepare the uterus for the potential of new life. From its structural components to its hormonal regulation and its role in pregnancy and disease, understanding the uterine lining provides invaluable insight into female reproductive health and the complexities of conception. As scientific understanding advances, so too does our ability to diagnose and treat conditions affecting this vital tissue, ultimately improving women’s reproductive well-being.