
White blood cells, also known as leukocytes, are indispensable components of the body’s defense system. These specialized cells circulate throughout the bloodstream and lymphatic system, acting as vigilant guardians against infection, inflammation, and disease. Understanding what constitutes a “good” white blood cell (WBC) count is crucial for monitoring overall health and detecting potential underlying medical conditions. A complete blood count (CBC) test, which includes a WBC count, is one of the most common and informative diagnostic tools available, offering vital insights into the body’s immune status and capacity to fight off threats.
Understanding White Blood Cells and Their Role
White blood cells are not a monolithic group but rather a diverse collection of cells, each with distinct functions. Produced in the bone marrow, they are continuously generated and released into the bloodstream, ready to respond to specific challenges. Their collective mission is to identify and neutralize foreign invaders such as bacteria, viruses, fungi, and parasites, as well as to eliminate damaged cells and abnormal growths within the body.
Types of White Blood Cells
The five main types of white blood cells, often referred to as a “WBC differential,” each play a unique role in the immune response:
- Neutrophils: These are the most abundant type of WBC and act as the body’s primary responders to bacterial and fungal infections. They are phagocytes, meaning they engulf and digest harmful microorganisms. A high neutrophil count often indicates an active bacterial infection.
- Lymphocytes: Comprising T cells and B cells, lymphocytes are critical for targeted immune responses. T cells directly attack infected cells and cancer cells, while B cells produce antibodies that neutralize pathogens. Elevated lymphocytes can suggest viral infections, chronic inflammation, or certain lymphatic disorders.
- Monocytes: As the largest type of WBC, monocytes also act as phagocytes. They migrate from the bloodstream into tissues, where they transform into macrophages, powerful scavengers that clear cellular debris and present antigens to lymphocytes, initiating more specific immune responses. Increased monocytes can be seen in chronic inflammatory diseases, viral infections, or some cancers.
- Eosinophils: These cells are primarily involved in allergic reactions and the defense against parasitic infections. They release toxins that can damage parasites and modulate inflammatory responses. High eosinophil counts are characteristic of allergies, asthma, and parasitic infestations.
- Basophils: The least common type of WBC, basophils release histamine and other chemicals during allergic reactions and parasitic infections, contributing to inflammation and blood vessel dilation. While less frequently a primary indicator, elevated basophils can be present in severe allergic reactions or certain blood disorders.
The Immune System’s Frontline
Together, these white blood cells form a sophisticated and interconnected network, constantly patrolling the body. When an infection or injury occurs, chemical signals trigger a rapid mobilization of WBCs to the affected site. Their ability to distinguish between “self” and “non-self” and to coordinate complex responses is fundamental to maintaining health and preventing widespread disease. A well-functioning immune system, reflected in a balanced WBC count, is essential for healing, recovery, and overall well-being.
Normal Ranges: What Do the Numbers Mean?
Determining a “good” white blood cell count involves understanding the established reference ranges, which can vary slightly depending on the laboratory, but generally fall within a specific spectrum. These ranges represent the counts found in the vast majority of healthy individuals. Deviations from these norms, either too high or too low, often signal an underlying issue that warrants further investigation.
Adult Reference Ranges
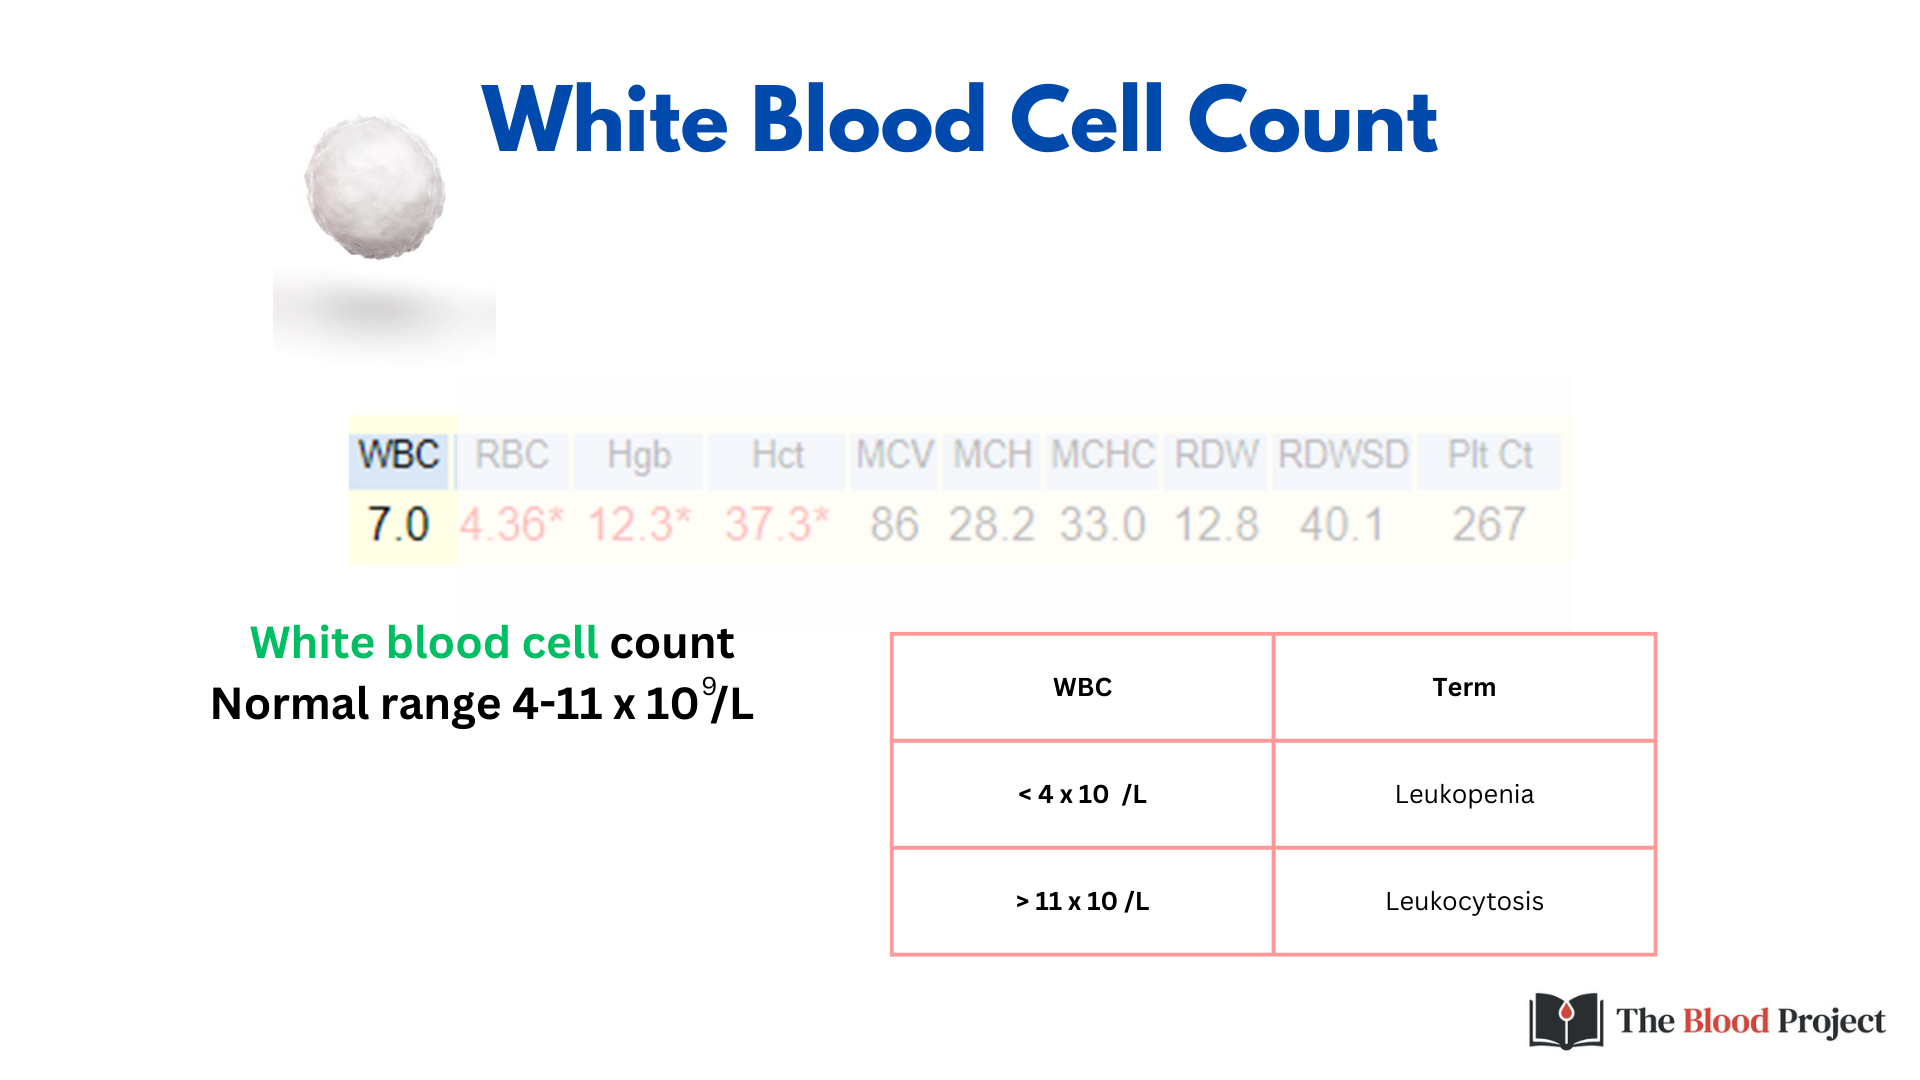
For adults, a typical healthy total white blood cell count usually falls between 4,000 and 11,000 cells per microliter of blood (or 4.0-11.0 x 10^9 cells/L). However, it’s important to remember that this is a general guideline. Doctors often look at the individual breakdown of each WBC type (the differential) for a more nuanced understanding.
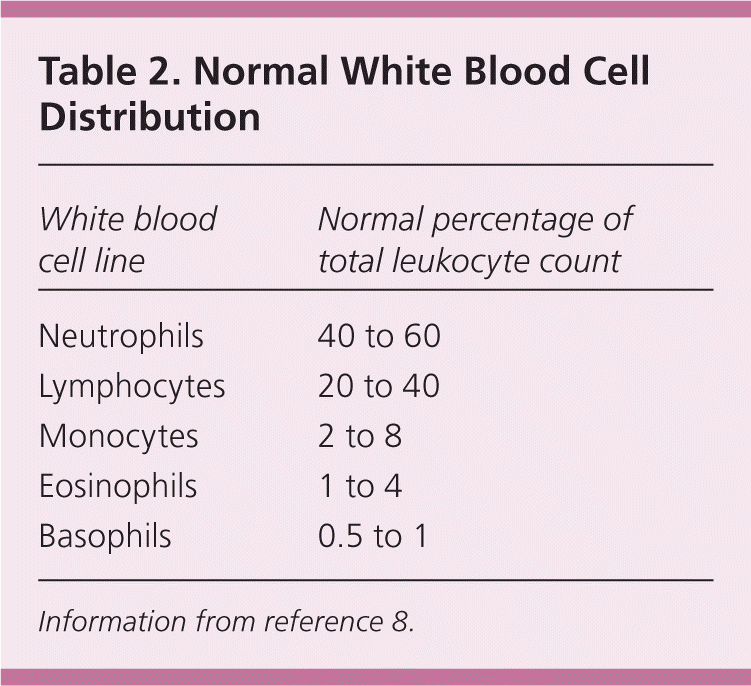
The approximate normal ranges for the differential count are:
- Neutrophils: 40-75%
- Lymphocytes: 20-45%
- Monocytes: 2-10%
- Eosinophils: 1-6%
- Basophils: 0-2%
These percentages, when combined with the total WBC count, provide a detailed snapshot of the immune system’s composition. For instance, a total count within the normal range might still be concerning if one specific type of WBC is disproportionately high or low.
Variations by Age and Other Factors
It’s crucial to note that “normal” WBC counts are not static. They can fluctuate based on several physiological and external factors:
- Age: Children, particularly infants and toddlers, typically have higher WBC counts than adults due to their developing immune systems and more frequent encounters with new pathogens. Newborns can have counts as high as 30,000 cells/µL, gradually decreasing as they grow.
- Pregnancy: Pregnant women often experience a slight increase in their WBC count, particularly during the third trimester and postpartum period, which is considered a normal physiological response.
- Stress: Both physical and emotional stress can temporarily elevate WBC counts, as the body prepares for a “fight or flight” response, releasing stress hormones that stimulate WBC production.
- Exercise: Strenuous physical activity can lead to a transient increase in WBCs as they are mobilized from peripheral tissues into the bloodstream.
- Ethnicity: Some minor variations in WBC counts have been observed across different ethnic groups, though these are generally within established normal ranges.
- Medications: Certain drugs, such as corticosteroids, can influence WBC counts, either increasing or decreasing them.
- Smoking: Smokers often have slightly higher baseline WBC counts than non-smokers due to chronic inflammation in their airways.
When interpreting a WBC count, healthcare providers consider these variables alongside the patient’s overall health, symptoms, and medical history to make an accurate assessment.
When Counts Are Too High: Leukocytosis
A white blood cell count above the normal range (typically >11,000 cells/µL for adults) is known as leukocytosis. While often indicative of the body’s active response to a threat, sustained or extremely high counts can also point to more serious underlying conditions requiring prompt medical attention.
Common Causes of High WBC Count
Leukocytosis is a common finding and can be triggered by a wide array of factors:
- Infection: This is the most frequent cause. Bacterial infections typically lead to an increase in neutrophils (neutrophilia), while viral infections might cause an increase in lymphocytes (lymphocytosis). Severe or systemic infections can drastically elevate total WBC counts.
- Inflammation: Non-infectious inflammatory conditions, such as arthritis, inflammatory bowel disease, or trauma (e.g., burns, surgery), can stimulate the immune system and result in elevated WBC counts.
- Stress: Significant emotional or physical stress, including severe anxiety, major surgery, or intense physical exertion, can temporarily raise WBC levels by releasing adrenaline and cortisol.
- Medications: Corticosteroids (e.g., prednisone) are well-known for their ability to increase WBC counts, particularly neutrophils, by affecting their release from bone marrow and circulation.
- Allergic Reactions: Acute allergic reactions, especially severe ones like anaphylaxis, can lead to transient leukocytosis, often with an increase in eosinophils.
- Tissue Damage: Conditions causing tissue damage, such as heart attacks (myocardial infarction) or burns, can trigger an inflammatory response and subsequent increase in WBCs.
- Bone Marrow Disorders: Certain conditions affecting the bone marrow, where WBCs are produced, can lead to uncontrolled production. These include myeloproliferative disorders like chronic myeloid leukemia, which can cause extremely high WBC counts.
- Autoimmune Diseases: Diseases where the immune system mistakenly attacks healthy tissues, such as rheumatoid arthritis or lupus, can also be associated with chronic leukocytosis.
Interpreting High Counts
The interpretation of leukocytosis always considers the differential count, the patient’s symptoms, and their medical history. For example, a high neutrophil count in a patient with fever and localized pain strongly suggests a bacterial infection. Conversely, a high lymphocyte count in a patient with swollen glands and fatigue might suggest a viral infection like mononucleosis. Extremely high or persistent leukocytosis, especially without a clear infectious or inflammatory cause, often warrants further investigation, including a bone marrow biopsy, to rule out hematological malignancies.
When Counts Are Too Low: Leukopenia
Conversely, a white blood cell count below the normal range (typically <4,000 cells/µL for adults) is termed leukopenia. A low WBC count can significantly impair the body’s ability to fight off infections, leaving an individual vulnerable to illness. While less common than leukocytosis, it is often a more concerning finding, indicating a compromised immune system.
Common Causes of Low WBC Count
Leukopenia can arise from various factors, many of which suppress bone marrow function or destroy circulating WBCs:
- Bone Marrow Suppression: This is a primary cause. Conditions or treatments that damage or suppress the bone marrow’s ability to produce WBCs can lead to leukopenia. This includes:
- Chemotherapy and Radiation Therapy: These cancer treatments are notorious for suppressing bone marrow activity, leading to a significant drop in WBCs (neutropenia).
- Certain Medications: Some drugs, such as specific antibiotics (e.g., chloramphenicol), antipsychotics (e.g., clozapine), and anticonvulsants, can cause drug-induced leukopenia.
- Aplastic Anemia: A rare but serious condition where the bone marrow stops producing enough new blood cells.
- Autoimmune Diseases: Conditions like lupus or rheumatoid arthritis can sometimes lead to the immune system attacking its own WBCs or bone marrow.
- Severe Infections: While mild infections typically cause leukocytosis, overwhelming or very severe infections (e.g., sepsis, typhoid fever, severe influenza, HIV) can sometimes deplete WBCs faster than the bone marrow can produce them, leading to leukopenia.
- Viral Infections: Many viral infections, including influenza, measles, and infectious mononucleosis, can temporarily reduce WBC counts. HIV specifically targets and destroys T-lymphocytes, leading to severe immunodeficiency.
- Nutritional Deficiencies: Deficiencies in essential vitamins and minerals, such as Vitamin B12 or folate, can impair bone marrow function and lead to reduced blood cell production.
- Liver and Spleen Disorders: An enlarged spleen (splenomegaly) can trap and destroy WBCs, leading to lower counts. Severe liver disease can also affect the production and circulation of WBCs.
- Myelodysplastic Syndromes: These are a group of disorders where the bone marrow produces abnormal or immature blood cells that don’t function correctly or die prematurely, leading to low counts.
Clinical Implications of Low Counts
Individuals with leukopenia, particularly those with a very low neutrophil count (neutropenia), are at a significantly increased risk of developing severe infections. Even common bacteria that are normally harmless can cause life-threatening infections in these individuals. Symptoms of leukopenia itself are often absent, but patients may experience recurrent or unusually severe infections, fever, chills, and general malaise. Identifying the cause of leukopenia is critical for guiding appropriate treatment, which might involve stopping offending medications, treating underlying infections, administering growth factors to stimulate WBC production, or managing bone marrow disorders.
Beyond the Numbers: When to Seek Medical Advice
While a blood test provides objective numbers, it’s the integration of these numbers with a patient’s symptoms, medical history, and clinical context that leads to an accurate diagnosis and appropriate management plan. A “good” white blood cell count isn’t just about falling within the normal range; it’s about the count being consistent with the body’s current state of health.
Symptoms to Watch For
It’s important to be aware of symptoms that might suggest an abnormal WBC count, even if you haven’t recently had a blood test.
If your WBC count is too high (leukocytosis), symptoms often relate to the underlying cause:
- Fever, chills, body aches (suggesting infection or inflammation).
- Localized pain or swelling (e.g., appendicitis, abscess).
- Fatigue and unexplained weight loss (potentially indicative of chronic inflammation or malignancy).
- Symptoms related to allergic reactions, such as rash, itching, or shortness of breath.
If your WBC count is too low (leukopenia), the primary concern is an increased susceptibility to infection:
- Recurrent infections that are slow to heal or unusually severe.
- Frequent fevers, even without obvious signs of infection.
- Fatigue, weakness, and general malaise.
- Symptoms like mouth sores, sore throat, or skin infections due to a weakened immune system.
Any persistent, unexplained symptoms, particularly those related to infection or chronic illness, warrant a visit to a healthcare professional.
Diagnostic Procedures and Follow-Up
If an abnormal WBC count is detected, your doctor will likely conduct further investigations to pinpoint the cause. This may include:
- Repeat Blood Tests: To confirm the initial finding and monitor trends.
- WBC Differential: To see which specific types of white blood cells are affected.
- Bone Marrow Biopsy: If a bone marrow disorder or cancer is suspected, a small sample of bone marrow will be taken for examination.
- Infection Screening: Cultures (blood, urine, sputum) to identify bacterial, viral, or fungal infections.
- Imaging Studies: X-rays, CT scans, or ultrasounds to look for sources of infection, inflammation, or organomegaly.
- Autoimmune Markers: Blood tests to look for antibodies associated with autoimmune diseases.
Regular follow-up with your healthcare provider is essential, especially if you are undergoing treatment for a condition affecting your WBC count. Early detection and management of abnormal WBC counts are critical for preventing complications and maintaining long-term health. Understanding your WBC count is a vital piece of your overall health puzzle, offering actionable insights into your body’s immune resilience.