
The phrenic nerve, a pair of nerves originating in the neck, plays a profoundly vital role in our ability to sustain life. While often overlooked in casual conversation about the nervous system, its primary function is intrinsically linked to one of the most fundamental and continuous actions we perform: breathing. Without the phrenic nerve, the diaphragm, the primary muscle of respiration, would be unable to contract, rendering spontaneous breathing impossible. This article delves into the intricate anatomy and crucial physiological contributions of the phrenic nerve, exploring its origins, pathway, innervation, and the critical implications of its function and dysfunction.
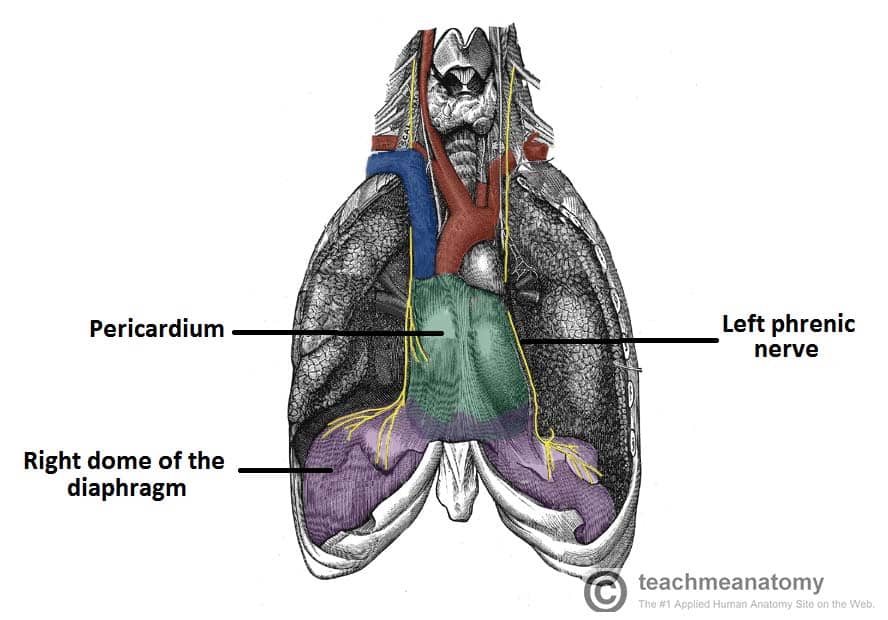
Anatomy and Pathway of the Phrenic Nerve
The phrenic nerve is unique in that it is the sole motor supply to the diaphragm. This muscular dome separates the thoracic cavity from the abdominal cavity, and its rhythmic contraction and relaxation are the driving force behind inhalation and exhalation. Understanding the phrenic nerve’s journey from its origin to its target organ is key to appreciating its importance.
Origin and Roots
The phrenic nerve’s roots arise from the cervical spinal cord, specifically from the ventral rami of spinal nerves C3, C4, and C5. This is often remembered by the mnemonic “C3, 4, 5 keeps the diaphragm alive.” These nerve roots begin their descent through the neck, contributing to the formation of the nerve. While C4 is typically the most significant contributor, contributions from C3 and C5 are essential for complete diaphragmatic innervation. The precise arrangement and contribution of these roots can vary slightly between individuals, but the functional outcome remains consistent: the creation of a robust nerve ready to descend to the diaphragm.
Descent Through the Thorax
After forming in the neck, the phrenic nerves, one on each side of the body, descend through the thoracic cavity. Their pathways are distinct and intricate, weaving through various anatomical structures.
Right Phrenic Nerve
The right phrenic nerve travels vertically down the right side of the neck, passing posterior to the subclavian artery and vein. It then enters the thorax, descending between the mediastinal pleura and the pericardium, in close proximity to the heart. It passes anterior to the right lung and then pierces the diaphragm slightly to the right of the inferior vena cava opening, just before it reaches its destination.
Left Phrenic Nerve
The left phrenic nerve follows a similar trajectory but is slightly longer due to the position of the heart. It descends on the left side of the neck, passing anterior to the subclavian artery. It then enters the thorax, lying lateral to the pericardium and heart. It courses anterior to the left lung and finally pierces the diaphragm, typically to the left of the esophageal opening.
Relationship with Other Structures
Throughout its descent, the phrenic nerve maintains intimate relationships with vital structures. It crosses the anterior scalene muscle in the neck and is often accompanied by the pericardiacophrenic artery and vein, which supply blood to the nerve and surrounding tissues. Its proximity to the heart and lungs highlights the delicate nature of its path and the potential for injury during thoracic procedures.
Innervation and Function of the Diaphragm
The primary and most critical role of the phrenic nerve is to provide motor and sensory innervation to the diaphragm. This innervation is essential for the mechanics of breathing.
Motor Innervation
The phrenic nerve is a mixed nerve, meaning it carries both motor and sensory fibers. The motor fibers are responsible for causing the diaphragm to contract. When these motor impulses travel down the phrenic nerve, they stimulate the muscle fibers of the diaphragm to contract. This contraction causes the diaphragm to flatten and move downward, increasing the vertical volume of the thoracic cavity. This increase in volume leads to a decrease in intra-thoracic pressure, drawing air into the lungs through the process of inhalation. Conversely, when the phrenic nerve signals relaxation, the diaphragm returns to its dome shape, decreasing thoracic volume and facilitating exhalation. This coordinated, rhythmic contraction and relaxation, largely driven by the phrenic nerve, is the cornerstone of our respiratory system.
Sensory Innervation
In addition to motor control, the phrenic nerve also carries sensory information from the diaphragm itself and from the diaphragmatic pleura (the lining of the diaphragm). This sensory input is crucial for proprioception, allowing us to sense the position of the diaphragm, and for detecting pain or irritation in the region. Referred pain is a notable phenomenon associated with phrenic nerve sensory innervation. Irritation or inflammation of the diaphragmatic pleura or peritoneum can cause pain that is felt in other areas, most commonly the shoulder. This is because the sensory fibers from these areas share common pathways in the spinal cord with sensory fibers from the shoulder, a phenomenon known as referred pain.
The Diaphragm: A Unique Muscle of Respiration
The diaphragm is not just another muscle; it is a unique structure with a dual role in both respiration and abdominal pressure regulation. The phrenic nerve’s control over this muscle enables these diverse functions.
Primary Muscle of Inhalation
During quiet, relaxed breathing, the diaphragm is the principal muscle responsible for inspiration. Its contraction accounts for approximately 75% of the tidal volume, the amount of air inhaled or exhaled during a normal breath. The force generated by the diaphragm’s downward movement is substantial, effectively expanding the lungs. The phrenic nerve’s constant, low-level signaling ensures that this crucial process continues uninterrupted, even during sleep.
Role in Forced Breathing and Other Actions

While the diaphragm is the primary muscle of quiet inhalation, accessory muscles of respiration become more active during forceful breathing, such as during exercise or when experiencing shortness of breath. However, the diaphragm still plays a role, and its ability to contract forcefully is augmented. Beyond respiration, the diaphragm also plays a critical role in other bodily functions that involve increasing intra-abdominal pressure. This includes actions like coughing, sneezing, vomiting, defecation, and childbirth. In these instances, the diaphragm contracts forcefully, while the glottis (the opening between the vocal cords) closes, creating a powerful increase in pressure within the abdominal cavity. This controlled pressure generation aids in expelling contents from the chest and abdomen. The phrenic nerve orchestrates these coordinated actions, demonstrating its multifaceted importance.
Clinical Significance and Phrenic Nerve Dysfunction
Given its vital role, any impairment to the phrenic nerve can have severe consequences for an individual’s respiratory function. Understanding the causes and manifestations of phrenic nerve dysfunction is crucial for diagnosis and management.
Causes of Phrenic Nerve Injury
Phrenic nerve injuries can occur due to a variety of reasons, ranging from direct trauma to medical conditions.
Trauma
Direct trauma to the neck or chest, such as from penetrating injuries (e.g., stab wounds, gunshot wounds) or blunt force trauma, can sever or damage the phrenic nerve. Surgical procedures in the neck or thoracic region also carry a risk of iatrogenic (medically caused) injury to the phrenic nerve. For example, cardiothoracic surgery, neck dissections, or even certain types of anesthesia can inadvertently affect the nerve.
Medical Conditions
Several medical conditions can lead to phrenic nerve dysfunction.
- Inflammation and Infection: Viral infections, such as those affecting the respiratory system, can sometimes lead to inflammation of the phrenic nerve (neuritis). Lyme disease, a tick-borne illness, has also been implicated in causing phrenic nerve palsy.
- Tumors: Tumors in the neck, mediastinum (the space between the lungs), or lungs can compress or invade the phrenic nerve, leading to impaired function.
- Autoimmune Disorders: Conditions like Guillain-Barré syndrome, an autoimmune disorder that affects the peripheral nervous system, can sometimes involve the phrenic nerve, leading to respiratory compromise.
- Neurological Diseases: Certain degenerative neurological diseases can affect nerve function, including the phrenic nerve.
Idiopathic Phrenic Nerve Palsy
In some cases, the cause of phrenic nerve palsy remains unknown, a condition referred to as idiopathic phrenic nerve palsy. While frustrating from a diagnostic standpoint, it still requires careful management and monitoring.
Manifestations of Phrenic Nerve Dysfunction
The most significant consequence of phrenic nerve dysfunction is compromised breathing. The severity of symptoms depends on whether one or both phrenic nerves are affected.
Unilateral Phrenic Nerve Palsy
When one phrenic nerve is paralyzed, the diaphragm on that side weakens or ceases to move properly. During inhalation, the intact diaphragm contracts normally, but the paralyzed side may paradoxically move upward (paradoxical movement) as the abdominal contents push it up due to the negative pressure generated by the functioning side. Patients with unilateral phrenic nerve palsy may experience mild shortness of breath, particularly with exertion. They might also notice increased fatigue or a reduced capacity for physical activity. Often, the respiratory system can compensate, and individuals may remain asymptomatic at rest.
Bilateral Phrenic Nerve Palsy
Bilateral phrenic nerve palsy is far more serious. If both phrenic nerves are compromised, the diaphragm becomes largely immobile. This leads to significant and often life-threatening respiratory insufficiency. Patients will experience severe shortness of breath, even at rest. They will rely heavily on accessory muscles of respiration, leading to labored breathing, retractions of the chest wall, and accessory muscle fatigue. In severe cases, mechanical ventilation (using a breathing machine) is required to sustain life.
Diagnosis and Management
Diagnosing phrenic nerve dysfunction typically involves a combination of clinical examination, imaging, and electrophysiological tests.
Diagnostic Tools
- Chest X-ray: Can reveal elevated hemidiaphragm or paradoxical movement of the diaphragm during breathing.
- Fluoroscopy: Real-time X-ray imaging allows for direct observation of diaphragmatic motion.
- Pulmonary Function Tests (PFTs): Measure lung volumes and capacities, which can be reduced in cases of diaphragmatic weakness.
- Electromyography (EMG) and Nerve Conduction Studies (NCS): These tests assess the electrical activity of the nerve and muscles, helping to confirm nerve damage and its extent.
- High-Resolution Computed Tomography (HRCT) or Magnetic Resonance Imaging (MRI): Can help identify underlying causes such as tumors or inflammation.

Management Strategies
Management depends on the underlying cause and the severity of the dysfunction.
- Conservative Management: For mild cases or those with potential for recovery, a period of observation and supportive care may be recommended.
- Treatment of Underlying Cause: If the dysfunction is due to an infection, tumor, or autoimmune disease, treating the primary condition is paramount. This might involve antibiotics, surgery, chemotherapy, or immunosuppressive therapy.
- Mechanical Ventilation: In severe cases of bilateral phrenic nerve palsy, mechanical ventilation is essential to support breathing. This can be temporary or long-term, depending on the prognosis.
- Diaphragmatic Pacing: In select cases of chronic, irreversible phrenic nerve paralysis, diaphragmatic pacing systems can be implanted. These devices electrically stimulate the phrenic nerve or diaphragm directly, allowing for spontaneous breathing without mechanical ventilation. This is a complex procedure reserved for specific patient populations.
- Physical Therapy: Respiratory physiotherapy can help patients optimize their breathing mechanics, strengthen accessory respiratory muscles, and improve overall lung function.
In conclusion, the phrenic nerve, though small and often unheralded, is a cornerstone of human survival. Its direct control over the diaphragm makes it indispensable for the continuous act of breathing. Understanding its anatomy, function, and the implications of its dysfunction is vital for appreciating the intricate marvel of the human respiratory system and for addressing the critical health challenges that can arise when this essential nerve is compromised.