
The term “half-life” is a cornerstone of understanding how medications work within the body, influencing everything from dosing schedules to treatment efficacy. While it might sound like a concept exclusive to the realm of physics, its application in pharmacology is critical. In essence, the half-life of a medication refers to the time it takes for the concentration of that drug in the bloodstream to be reduced by half. This seemingly simple metric holds profound implications for how healthcare professionals manage patient treatment, ensuring optimal therapeutic effects while minimizing the risk of adverse reactions. Understanding half-life allows for informed decisions about how often a drug needs to be administered, how long it will take to reach therapeutic levels, and how long it will remain in the system after discontinuation.
The Pharmacokinetic Journey: Absorption, Distribution, Metabolism, and Excretion (ADME)
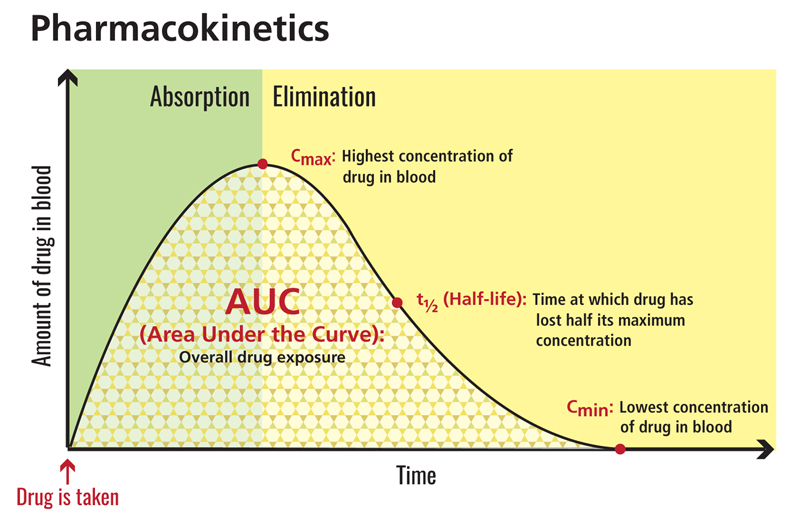
The half-life of a medication is not a static value; it is intrinsically linked to the complex processes that govern a drug’s behavior within the body. These processes are collectively known as ADME: Absorption, Distribution, Metabolism, and Excretion. Each of these phases plays a crucial role in determining the concentration of a drug over time, and therefore, its half-life.
Absorption: Entering the System
Absorption is the process by which a drug enters the bloodstream from its site of administration. This can occur through various routes, such as oral ingestion, injection, inhalation, or topical application. The rate and extent of absorption are influenced by factors like the drug’s chemical properties, the route of administration, and the physiological state of the patient. For instance, a drug taken orally must pass through the gastrointestinal tract and liver (first-pass metabolism) before reaching systemic circulation, a process that can significantly impact its bioavailability and the initial concentration achieved, indirectly affecting how quickly subsequent concentrations decline.
Distribution: Reaching the Target
Once absorbed, a drug is distributed throughout the body via the bloodstream. Distribution is not uniform; it depends on factors such as blood flow to different tissues, the drug’s ability to bind to plasma proteins, and its lipid solubility. Drugs that are highly lipid-soluble can readily cross cell membranes and distribute into tissues, including the brain. Conversely, drugs that are highly protein-bound will have a larger proportion circulating in the blood and may have a longer apparent half-life because only the unbound fraction is pharmacologically active and available for elimination.
Metabolism: Chemical Transformation
Metabolism, primarily occurring in the liver, involves the chemical alteration of a drug into inactive or less active metabolites. This process is crucial for detoxification and facilitates the excretion of the drug from the body. Enzymes, particularly those in the cytochrome P450 (CYP) family, are responsible for metabolizing a vast array of drugs. Factors like genetic variations in these enzymes, liver function, and the presence of other medications can significantly influence the rate of metabolism. A drug that is metabolized rapidly will generally have a shorter half-life compared to one that is metabolized slowly.
Excretion: Leaving the Body
Excretion is the final stage of ADME, where the drug and its metabolites are removed from the body. The primary route of excretion is through the kidneys in urine, but other routes include the feces, bile, sweat, and exhaled air. Renal function is a critical determinant of drug excretion. Patients with impaired kidney function will eliminate drugs more slowly, leading to a prolonged half-life and an increased risk of drug accumulation and toxicity.
Types of Half-Life: Primary, Effective, and Biological
While the fundamental definition of half-life is consistent, different nuances are considered in clinical practice. Understanding these variations provides a more comprehensive picture of a drug’s behavior.
Primary Half-Life (Elimination Half-Life)
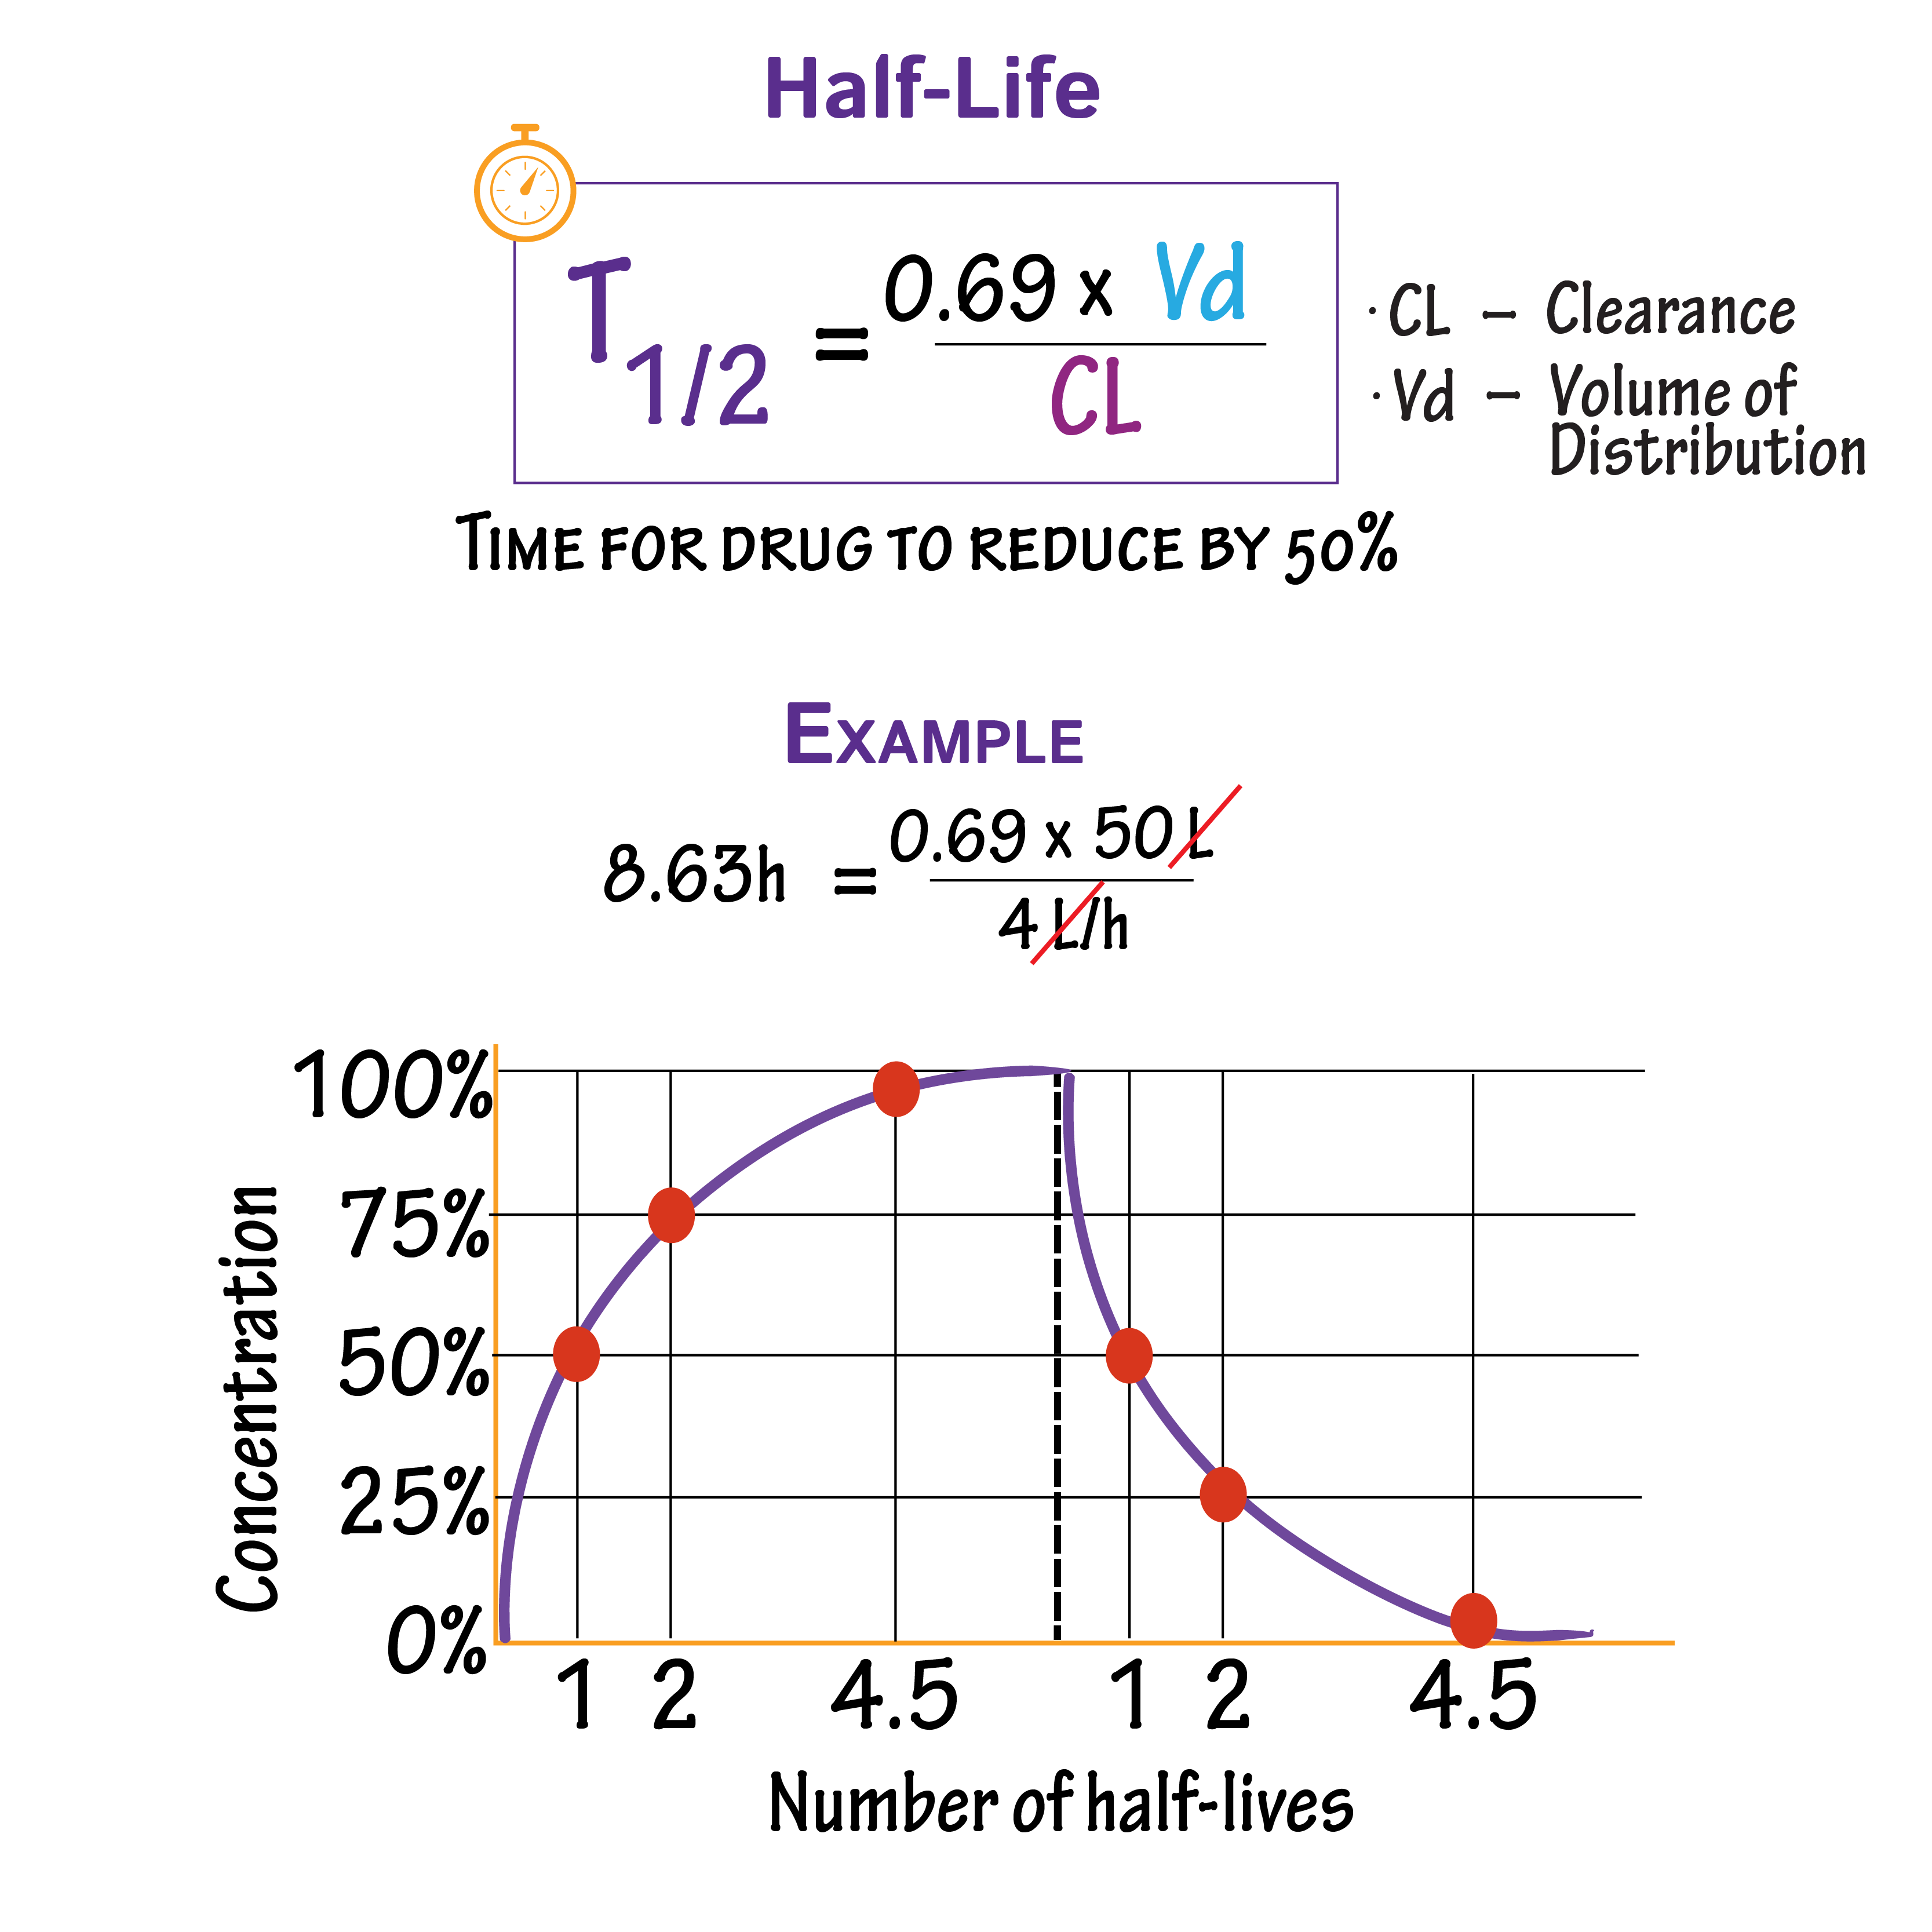
This is the most commonly referred to half-life and represents the time it takes for the concentration of the parent drug in the plasma to decrease by 50% due to elimination processes alone. It is a measure of how quickly the drug is removed from the body. This value is determined by both metabolism and excretion. For example, if a drug has a half-life of 8 hours, it means that after 8 hours, only half of the original dose will remain in the bloodstream. After another 8 hours (16 hours total), half of the remaining amount will be eliminated, leaving only one-quarter of the original dose.
Effective Half-Life
The effective half-life, sometimes referred to as the apparent half-life, accounts for the entire process of drug elimination from the body, including any reversible binding to tissues or proteins. In some cases, a drug might be temporarily sequestered in certain tissues. The effective half-life considers the rate at which the drug is released from these tissues back into the bloodstream for elimination. This can sometimes differ from the primary elimination half-life, especially for drugs with significant tissue distribution. It is a more practical measure for predicting how long a drug will exert its pharmacological effects.
Biological Half-Life
This term is less commonly used in standard pharmacology and is more associated with radioactive isotopes used in medical imaging or therapy. It refers to the time it takes for the amount of a radioactive substance in the body to decrease by half due to biological processes (excretion, metabolism) and radioactive decay. In drug therapy, the focus is typically on the elimination or effective half-life.
Factors Influencing Half-Life
The half-life of a medication is not a fixed constant for every individual. Numerous physiological and external factors can alter this crucial parameter, necessitating individualized treatment adjustments.
Patient-Specific Factors
- Age: Both very young children and the elderly may have altered drug metabolism and excretion. Immature liver enzymes in neonates and infants, and decreased organ function in the elderly, can lead to longer half-lives.
- Renal Function: As mentioned, kidney disease significantly impairs drug excretion. A patient with chronic kidney disease will likely have a much longer half-life for drugs cleared by the kidneys.
- Hepatic Function: Liver disease, such as cirrhosis, can impair the liver’s ability to metabolize drugs, leading to an increased half-life.
- Body Composition: The distribution of a drug can be influenced by the amount of fat or muscle tissue in the body. Lipid-soluble drugs might have longer half-lives in individuals with a higher percentage of body fat.
- Genetics: Variations in the genes encoding metabolic enzymes (like CYP enzymes) can lead to individuals being “fast metabolizers” or “slow metabolizers” of certain drugs, drastically impacting their half-lives.
- Disease States: Conditions affecting blood flow, protein binding, or organ function can influence drug half-life. For example, conditions causing edema might alter drug distribution.
External Factors
- Drug Interactions: When multiple medications are taken concurrently, they can interact with each other. Some drugs can inhibit or induce the activity of metabolic enzymes, thereby affecting the half-life of other drugs. For instance, one drug might slow down the metabolism of another, prolonging its half-life and increasing the risk of toxicity.
- Diet: Certain foods can affect drug absorption or metabolism. For example, grapefruit juice is known to inhibit CYP3A4 enzymes, which can increase the bioavailability and half-life of many medications.
- Lifestyle Factors: Smoking and alcohol consumption can also influence drug metabolism, often leading to faster metabolism and shorter half-lives for some drugs.
Clinical Significance: Why Half-Life Matters in Patient Care
The understanding of a medication’s half-life is indispensable in clinical practice, guiding critical decisions that directly impact patient outcomes. It is the bedrock upon which rational drug therapy is built.
Dosing Frequency and Maintenance Doses
The half-life of a drug is the primary determinant of how often it needs to be administered to maintain therapeutic levels in the body. For drugs with short half-lives, frequent dosing is required to prevent drug concentrations from falling below the minimum effective concentration (MEC). Conversely, drugs with long half-lives can be administered less frequently, improving patient adherence.
For example, a drug with a half-life of 4 hours taken once daily might not maintain therapeutic levels for the entire 24-hour period. To achieve steady-state concentrations (where the rate of drug administration equals the rate of elimination), the drug needs to be given at intervals related to its half-life. Dosing regimens are often designed to achieve steady-state concentrations within approximately 4-5 half-lives.
Time to Reach Therapeutic Levels
Similarly, the half-life dictates how long it takes for a drug to reach its effective therapeutic concentration in the bloodstream after the first dose. For drugs with long half-lives, it may take several days of regular dosing before the drug concentration is high enough to produce the desired clinical effect. In such cases, a “loading dose” – a larger initial dose – may be administered to rapidly achieve therapeutic levels, followed by smaller maintenance doses.
Duration of Action and Drug Accumulation
The half-life helps predict how long a drug will remain in the body after it is stopped. For drugs with short half-lives, the effects diminish relatively quickly once dosing ceases. However, for drugs with long half-lives, it can take a considerable amount of time for the drug to be fully eliminated from the system. This is particularly important in cases of potential toxicity or when switching to a different medication. If a drug with a long half-life is given to a patient with impaired renal or hepatic function, it can accumulate to toxic levels due to delayed excretion.
Drug Withdrawal and Tapering Strategies
For medications that can cause withdrawal symptoms upon abrupt discontinuation (e.g., certain antidepressants, benzodiazepines), understanding the half-life informs strategies for gradual dose reduction, or “tapering.” A slower tapering schedule is often employed for drugs with longer half-lives to minimize the severity of withdrawal effects. Conversely, drugs with very short half-lives might require more rapid tapering or even a bridge medication to manage withdrawal.

Conclusion: The Power of Predictability in Drug Therapy
In conclusion, the half-life of a medication is a fundamental pharmacokinetic parameter that quantifies the time required for the drug’s concentration in the body to decrease by half. This concept is not merely academic; it is a practical tool that underpins rational drug prescribing and management. By understanding how absorption, distribution, metabolism, and excretion influence a drug’s half-life, and by considering patient-specific and external factors, healthcare professionals can optimize dosing regimens. This leads to more effective treatment, minimizes the risk of adverse drug reactions, and ensures the safe and predictable use of medications, ultimately enhancing patient care and well-being. The half-life, therefore, represents a critical element in the art and science of pharmacotherapy.