
HIV, the Human Immunodeficiency Virus, is a retrovirus that targets specific cells within the human immune system, primarily those responsible for orchestrating and executing the body’s defense against pathogens. Understanding which cells HIV affects is crucial to comprehending its devastating impact on the immune system and the progression of the disease. The virus’s primary targets are cells that possess a specific receptor on their surface, allowing HIV to bind and subsequently infect them. This selective tropism is the hallmark of HIV’s pathogenesis.
The Primary Targets: CD4+ T Cells
The most profoundly affected cells by HIV are CD4+ T cells, also known as T-helper cells. These lymphocytes are central players in the adaptive immune response. They act as conductors of the immune orchestra, coordinating the actions of other immune cells, including B cells (which produce antibodies) and cytotoxic T cells (which kill infected cells). CD4+ T cells are characterized by the presence of a protein receptor called CD4 on their cell surface. This CD4 molecule serves as the primary docking site for the HIV virus.
The Mechanism of CD4+ T Cell Infection
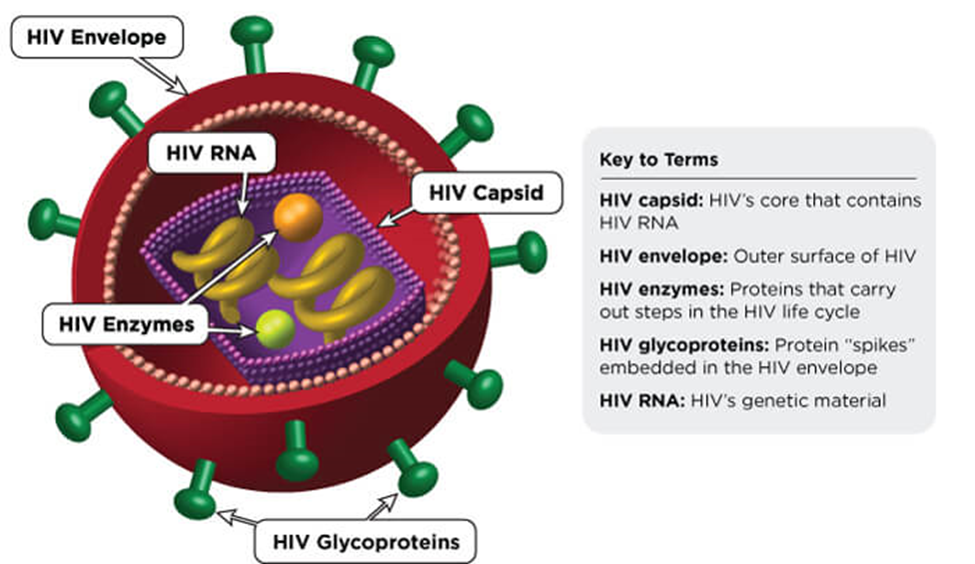
Upon entering the bloodstream, HIV encounters CD4+ T cells. The virus’s outer envelope contains glycoproteins, specifically gp120, which have a high affinity for the CD4 receptor. The binding of gp120 to CD4 is the initial step in the infection process. Following this binding, a conformational change occurs in another viral glycoprotein, gp41, which facilitates the fusion of the viral envelope with the cell membrane of the CD4+ T cell. Once inside the cell, HIV releases its genetic material (RNA) and essential enzymes into the cytoplasm.
The virus then employs a unique enzyme called reverse transcriptase to convert its RNA genome into DNA. This viral DNA, now in a double-stranded form, is transported into the cell’s nucleus and integrated into the host cell’s genome by another viral enzyme called integrase. Once integrated, the viral DNA becomes a permanent part of the host cell’s genetic material. This integrated viral DNA is known as a provirus.
Consequences of CD4+ T Cell Depletion
The consequence of this infection cycle within CD4+ T cells is twofold. Firstly, the virus hijacks the cell’s machinery to replicate itself, producing new viral particles that bud off from the infected cell. This process often damages and eventually destroys the CD4+ T cell. Secondly, even if the cell isn’t immediately destroyed, the chronic activation and exhaustion of these cells due to persistent viral replication lead to their dysfunction and eventual depletion.
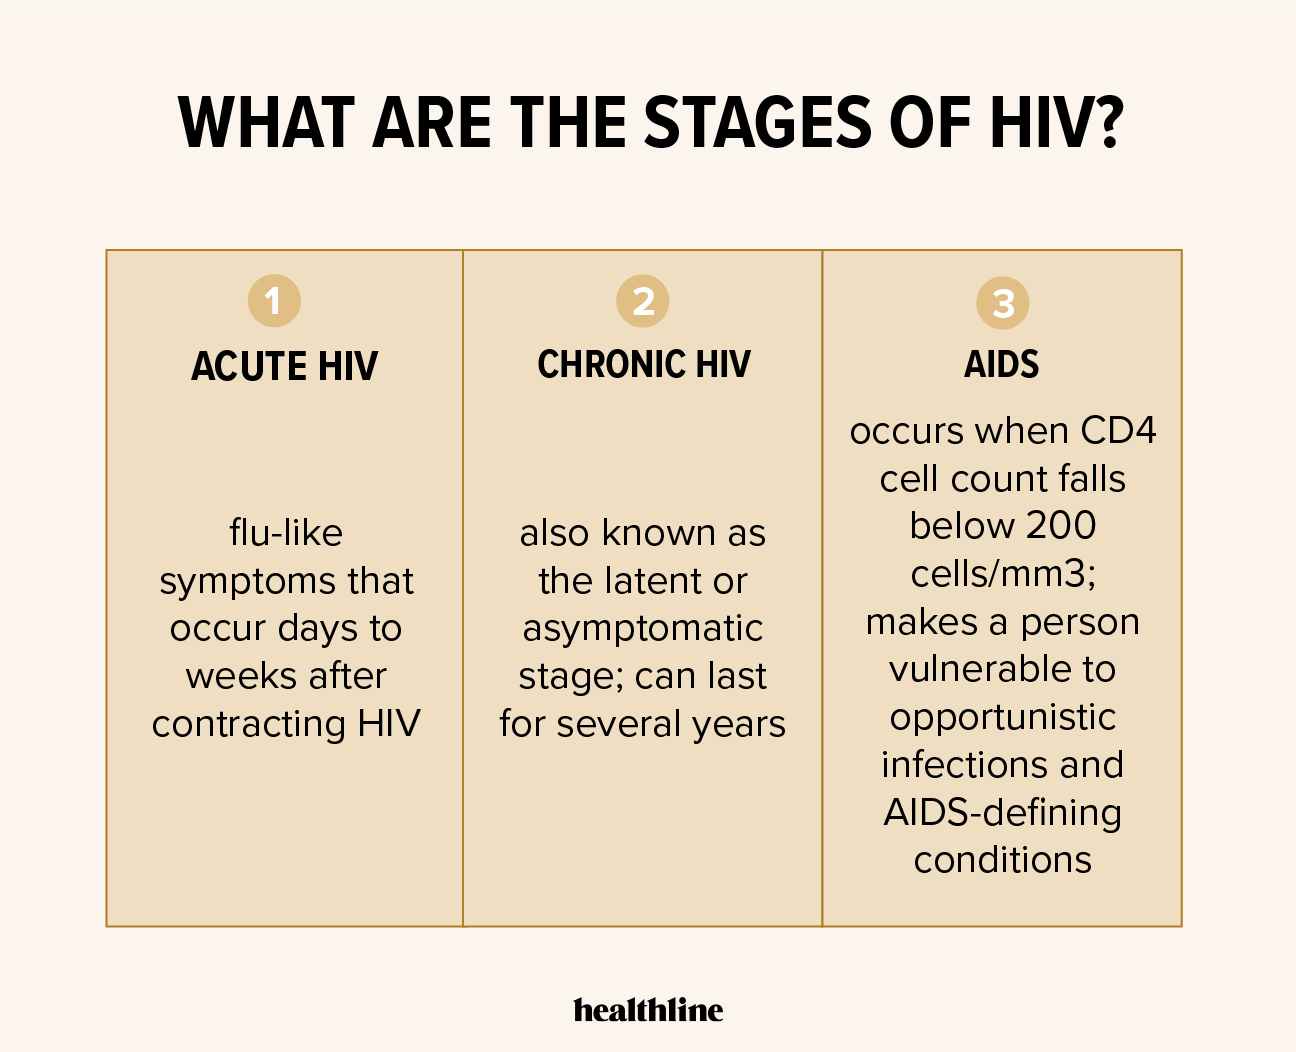
As the number of CD4+ T cells declines, the immune system’s ability to mount effective responses against opportunistic infections and certain cancers is severely compromised. The hallmark of Acquired Immunodeficiency Syndrome (AIDS), the advanced stage of HIV infection, is a critically low CD4+ T cell count (typically below 200 cells per cubic millimeter of blood) and the presence of one or more opportunistic infections or AIDS-defining cancers. This depletion renders the individual vulnerable to pathogens that a healthy immune system would readily control.
Other Key Immune Cells Affected
While CD4+ T cells are the primary targets, HIV can also infect and affect other cells of the immune system, albeit to a lesser extent or with different consequences. These include:
Macrophages
Macrophages are large phagocytic cells that play a critical role in innate immunity, engulfing and digesting cellular debris, foreign substances, microbes, and cancer cells. They also present antigens to T cells, initiating adaptive immune responses. Macrophages also express the CD4 receptor, making them susceptible to HIV infection.
Role of Macrophages in HIV Infection
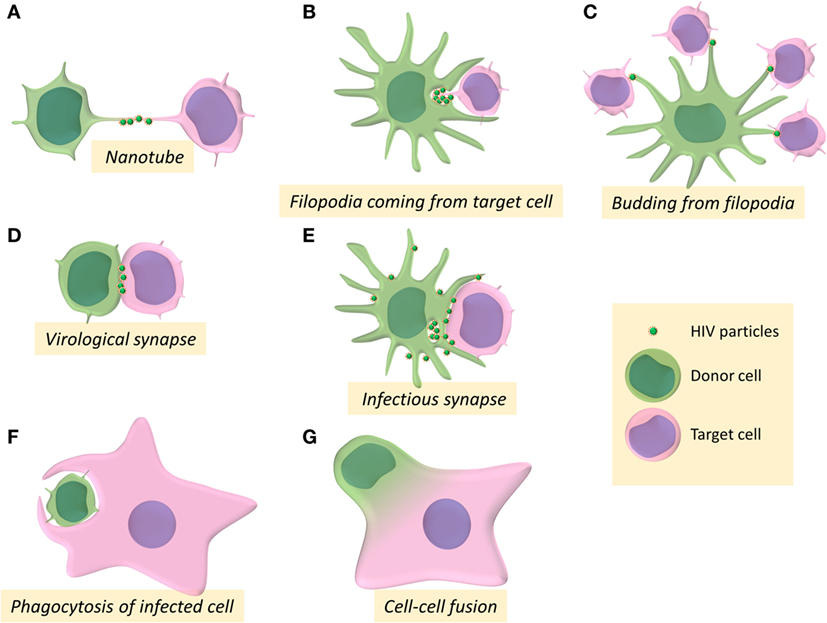
Macrophages can become infected by HIV, particularly in the early stages of infection and in certain tissues like the brain. Unlike T cells, macrophages tend to be more resistant to the cytopathic effects of HIV. This means that while they can be infected and produce virus, they don’t always die off as rapidly as CD4+ T cells. However, infected macrophages can still contribute to viral reservoirs and the spread of infection.
Furthermore, infected macrophages can act as reservoirs for HIV, particularly in tissues like the brain and lymph nodes, where they can harbor the virus for extended periods. They can also contribute to chronic inflammation, a hallmark of HIV infection that exacerbates disease progression. HIV infection of macrophages can also impair their ability to perform their essential functions, such as phagocytosis and antigen presentation, further weakening the immune system.
Dendritic Cells
Dendritic cells (DCs) are specialized antigen-presenting cells (APCs) that are crucial for initiating adaptive immune responses. They capture antigens from pathogens, process them, and present them to T cells in lymph nodes. Dendritic cells have also been shown to express CD4 and co-receptors that can bind HIV.
Dendritic Cells as Vehicles and Reservoirs
Dendritic cells play a complex role in HIV pathogenesis. While they can be infected by HIV, their primary significance lies in their potential to facilitate the transmission of the virus. Certain types of dendritic cells, particularly myeloid and plasmacytoid dendritic cells, can capture free virus particles and transport them to lymphoid tissues where they can infect susceptible CD4+ T cells. This makes them crucial for disseminating the virus throughout the body.
Additionally, some studies suggest that dendritic cells can also act as reservoirs for HIV, although this role is generally considered less significant than that of macrophages or T cells. The interaction between HIV and dendritic cells is a dynamic and multifaceted aspect of viral pathogenesis, highlighting the intricate ways in which the virus manipulates the immune system.
Cells of the Nervous System
While HIV’s primary focus is on immune cells, it can also affect the nervous system, leading to a range of neurological complications. This occurs through several mechanisms:
Microglia and Astrocytes
Microglia are the resident immune cells of the central nervous system (CNS), acting as macrophages within the brain and spinal cord. Astrocytes are glial cells that provide structural and metabolic support to neurons and play a role in maintaining the blood-brain barrier. HIV can infect microglia, and indirect effects on astrocytes also contribute to neurological damage.
HIV-Associated Neurocognitive Disorders (HAND)
Infected microglia can release inflammatory cytokines and chemokines, as well as viral proteins like Tat and gp120, into the brain microenvironment. These substances can be toxic to neurons and astrocytes, leading to neuronal dysfunction, damage, and death. This inflammatory cascade and direct viral damage contribute to the development of HIV-Associated Neurocognitive Disorders (HAND), which can range from mild cognitive impairment to severe dementia. The blood-brain barrier, which normally protects the CNS, can also be compromised by HIV infection and associated inflammation, allowing more virus and inflammatory mediators to enter the brain.
Conclusion: A Systemic Assault
In summary, HIV is a virus with a predilection for cells bearing the CD4 receptor, making CD4+ T cells its primary and most devastating target. The progressive depletion and dysfunction of these cells cripple the adaptive immune system, leading to immunodeficiency. However, HIV’s impact is not limited to CD4+ T cells. It also infects macrophages and dendritic cells, contributing to viral reservoirs, immune dysregulation, and the dissemination of the virus. Furthermore, its ability to affect the nervous system through microglia and indirect pathways leads to significant neurological complications. Understanding the diverse cellular targets of HIV is fundamental to developing effective antiviral therapies and strategies to combat this complex and persistent pathogen.