
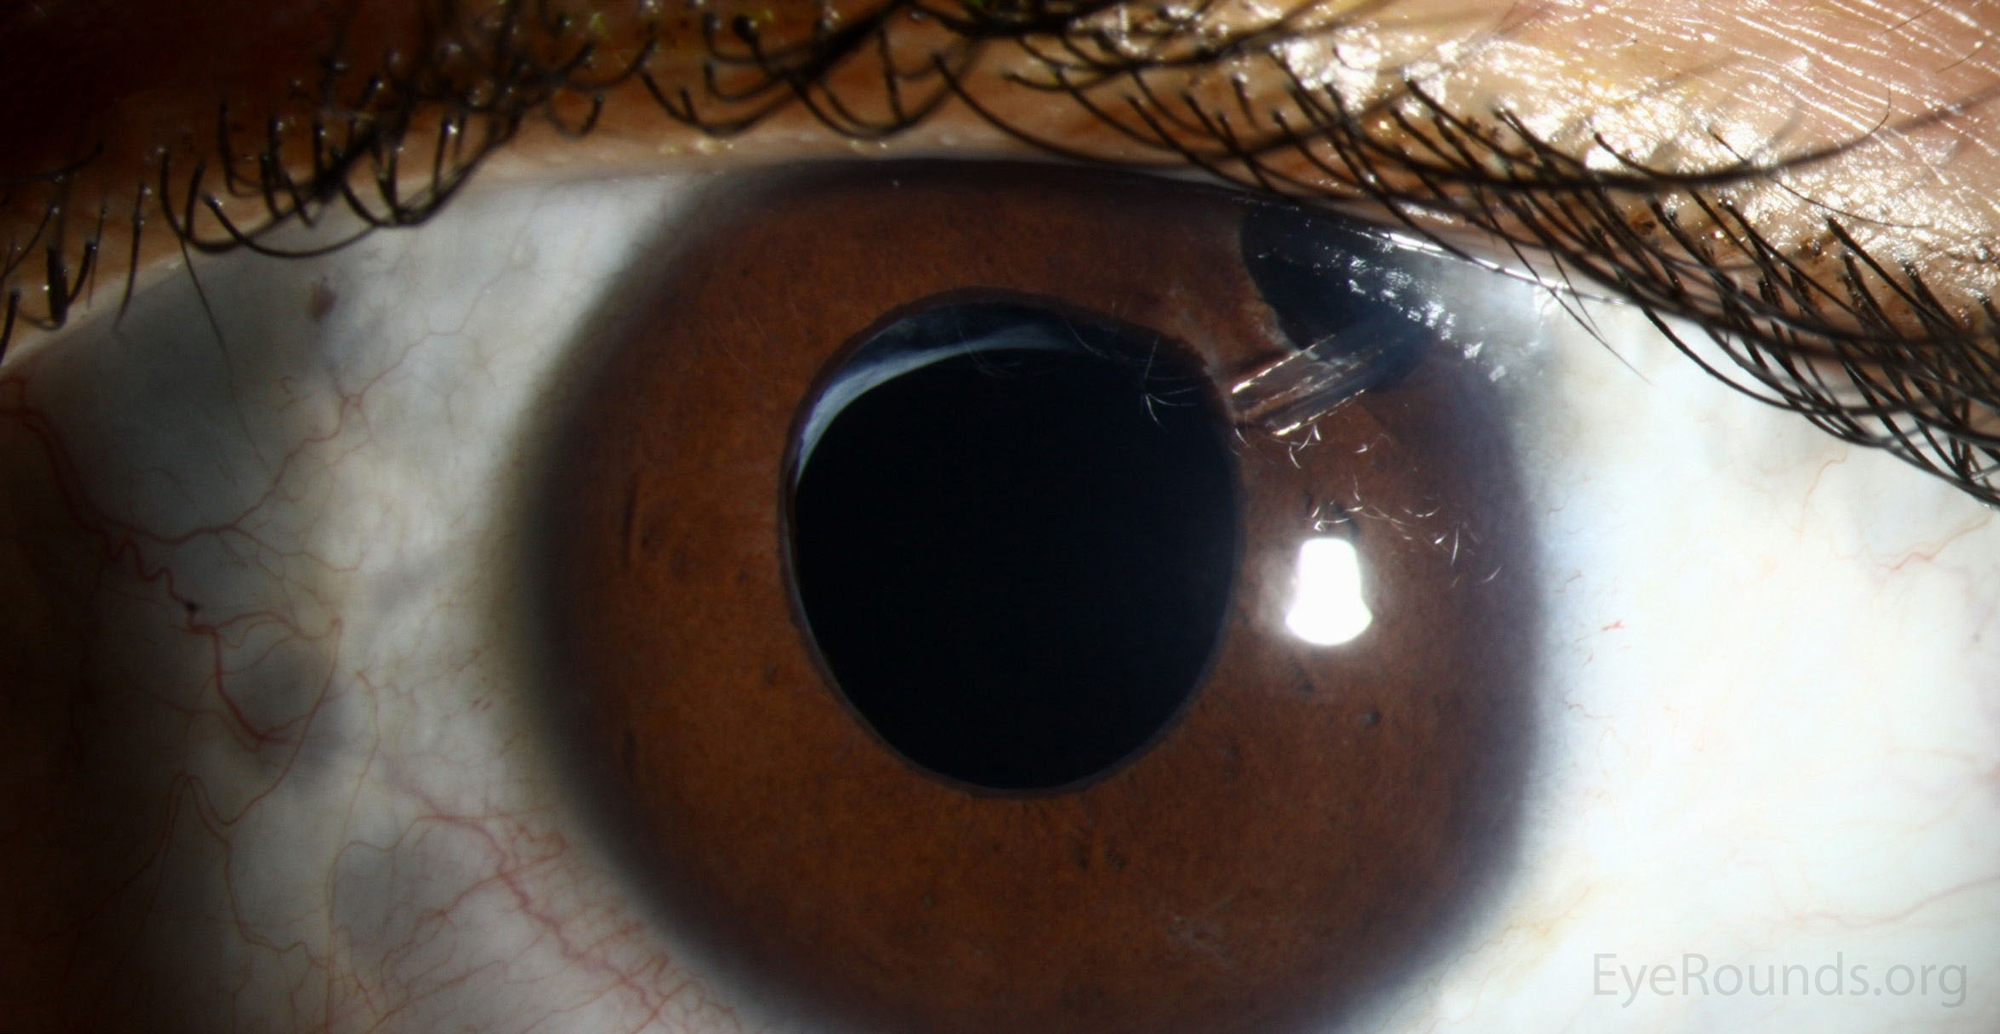
Aphakia, a term derived from the Greek words “a-” (without) and “phakos” (lens), refers to the absence of the natural crystalline lens of the eye. This condition can be congenital, meaning present at birth, or acquired later in life due to various factors. Understanding aphakia is crucial, not only for ophthalmologists and optometrists but also for individuals seeking to comprehend eye health and the potential impact on vision. While seemingly straightforward, the implications of aphakia are multifaceted, influencing visual acuity, refractive error, and the overall visual experience.
Understanding the Ocular Lens and Its Role
To fully grasp aphakia, it’s essential to appreciate the function of the natural crystalline lens. Situated behind the iris and pupil, the lens is a transparent, biconvex structure that plays a pivotal role in the eye’s ability to focus light onto the retina. This focusing power, known as refractive power, is vital for clear vision at varying distances.
Refraction: The Science of Focusing Light
The process by which the eye achieves focus is called refraction. Light rays enter the eye and are bent, or refracted, by the cornea and the crystalline lens. The cornea, the transparent outer layer of the eye, provides the majority of the eye’s focusing power. However, the lens offers a dynamic form of refraction through a process called accommodation.
Accommodation: Adjusting Focus for Different Distances
Accommodation is the ability of the eye to change its refractive power to focus on objects at different distances. This is achieved by the ciliary muscles, a ring of smooth muscle in the eye’s middle layer (vascular layer) that controls the shape of the lens. When focusing on distant objects, the ciliary muscles relax, causing the lens to flatten and become less powerful. Conversely, when focusing on near objects, the ciliary muscles contract, making the lens thicker and more curved, thus increasing its refractive power. This intricate interplay allows us to see both far-away landscapes and close-up details with clarity.
The Lens’s Contribution to Refractive Error
The precise curvature and thickness of the crystalline lens, combined with the refractive power of the cornea, determine the eye’s overall refractive state. Deviations from the ideal refractive state can lead to common refractive errors such as myopia (nearsightedness), hyperopia (farsightedness), and astigmatism. The lens’s ability to accommodate is a key factor in compensating for certain degrees of these errors, allowing for a broader range of clear vision.
Causes and Types of Aphakia
Aphakia can arise from several distinct causes, leading to different clinical presentations and management strategies. Broadly, these can be categorized as congenital or acquired.
Congenital Aphakia
Congenital aphakia is a rare condition present at birth. It can be an isolated finding or associated with various syndromes and genetic conditions.
Genetic Predisposition
In some cases, congenital aphakia may be inherited. Certain genetic mutations can disrupt the normal development of the eye during gestation, leading to the absence or incomplete formation of the crystalline lens. Understanding these genetic links is crucial for genetic counseling and family planning.
Associated Ocular Anomalies
Congenital aphakia is often accompanied by other ocular abnormalities. These can include microphthalmia (abnormally small eyes), corneal opacities, iris coloboma (a gap in the iris), and retinal abnormalities. The presence of these co-occurring conditions can significantly impact the overall visual prognosis.
Acquired Aphakia
Acquired aphakia is far more common and results from events or procedures that occur after birth.
Cataract Surgery
The most prevalent cause of acquired aphakia in adults is the surgical removal of a cataract. A cataract is a clouding of the natural crystalline lens, which impairs vision. During cataract surgery, the clouded lens is removed. While modern cataract surgery often involves the implantation of an intraocular lens (IOL) to restore focusing power, in cases where an IOL is not implanted or is subsequently removed, the patient becomes aphakic. Historically, before the widespread use of IOLs, cataract surgery routinely resulted in aphakia.
Trauma
Severe eye trauma, such as a blunt force impact or a penetrating injury, can dislodge or shatter the crystalline lens, leading to its expulsion or fragmentation within the eye. In such instances, surgical intervention may be necessary to remove the damaged lens fragments, resulting in aphakia. The extent of visual loss in traumatic aphakia is often dependent on associated injuries to other ocular structures.
Uveitis and Other Inflammatory Conditions
Chronic or severe inflammation within the eye, known as uveitis, can sometimes lead to the dislocation or destruction of the crystalline lens. The inflammatory process can weaken the zonules of Zinn, the fibers that hold the lens in place, causing it to fall backward into the vitreous cavity or become opaque and eventually require removal.
Intumescent Cataracts
An intumescent cataract is a mature or hypermature cataract where the lens cortex has swelled due to hydration. This swelling can lead to increased pressure within the lens capsule, potentially causing the lens to rupture or dislocate, resulting in aphakia if not managed surgically.
Visual Consequences of Aphakia
The absence of the crystalline lens has significant implications for vision, primarily due to the loss of its refractive and accommodative capabilities.
Loss of Refractive Power and Hyperopia

The crystalline lens contributes a substantial amount of refractive power to the eye. Its removal or absence results in a significant shift in the eye’s refractive state, typically leading to a profound degree of hyperopia (farsightedness). Without the lens, light rays that would have been focused by it now converge behind the retina, making it difficult to see distant objects clearly.
Impact on Accommodation
The loss of the crystalline lens also means the complete absence of accommodation. This means an aphakic eye cannot change its focus to see objects at different distances. While the cornea provides a fixed amount of refractive power, the dynamic adjustment provided by the lens is gone. This severely limits the ability to read or perform other near-vision tasks without corrective lenses.
High-Order Aberrations
In some cases, particularly with traumatic aphakia or when the removal of the lens is not perfectly smooth, individuals may experience high-order aberrations. These are more complex distortions of light than simple refractive errors and can lead to symptoms like glare, halos around lights, and reduced visual quality, even with corrective lenses.
Management and Correction of Aphakia
The goal of managing aphakia is to restore clear and functional vision. This is primarily achieved through optical correction.
Spectacle Lenses
Historically, aphakia was corrected using high-powered convex spectacle lenses. These thick, heavy lenses are designed to compensate for the missing refractive power of the crystalline lens. While effective in improving distance vision, they can cause significant peripheral distortion, a magnified image size (which can lead to binocular vision issues if only one eye is aphakic), and cosmetic concerns due to their thickness.
Contact Lenses
Contact lenses offer a more cosmetically appealing and often visually superior option for correcting aphakia compared to spectacles.
Hard and Rigid Gas Permeable (RGP) Lenses
Hard lenses, and their more advanced successors, RGP lenses, can provide excellent visual acuity for aphakic individuals. They offer good oxygen permeability and can correct for significant hyperopia. However, they can have a learning curve for insertion and removal and may not be as comfortable for extended wear as some other types of contact lenses.
Soft Aphakic Contact Lenses
Specialized soft contact lenses are designed for aphakic correction. These lenses are typically high-plus power and can provide good comfort and visual results. They are generally easier to wear and handle than RGP lenses.
Intraocular Lenses (IOLs)
The advent of intraocular lenses has revolutionized the management of aphakia, particularly in the context of cataract surgery.
Post-Cataract Surgery IOL Implantation
As mentioned earlier, the most common scenario where aphakia is avoided is during modern cataract surgery. After the natural lens is removed, an artificial IOL is implanted in its place. These IOLs are made of biocompatible materials and are designed to permanently restore the eye’s focusing power. They can be monofocal (providing clear vision at one distance) or multifocal (providing clear vision at multiple distances), significantly reducing or eliminating the need for corrective lenses post-surgery.
Sulcus-Placed IOLs
In cases where an IOL cannot be implanted in the capsular bag (the natural pocket where the lens resided) during cataract surgery, it can be placed in the sulcus, a ciliary body structure. These are known as sulcus-placed IOLs. This is a common approach when the capsular bag is compromised or absent, as can happen in some forms of congenital aphakia or after trauma.
Iris-Claw Lenses
Iris-claw lenses are a type of anterior chamber IOL that is surgically attached to the iris. They are often used when there is no capsular support for an IOL, or when the cornea is not suitable for a standard intraocular lens. These lenses are inserted and then secured by gently grasping the iris tissue.
Living with Aphakia
Aphakia, while a significant visual impairment, does not necessarily mean a life of severely compromised vision. With appropriate management, individuals can achieve good visual function.
Rehabilitation and Visual Training
For individuals who were born with aphakia or experienced traumatic aphakia without immediate IOL implantation, visual rehabilitation is crucial. This can involve a combination of optical correction (spectacles or contact lenses) and visual training exercises. These exercises aim to improve visual acuity, depth perception, and hand-eye coordination.
Importance of Regular Eye Care
Regardless of the cause of aphakia, regular comprehensive eye examinations are essential. An eye care professional can monitor the health of the eye, adjust corrective prescriptions as needed, and screen for any secondary complications. This proactive approach ensures optimal visual outcomes and early detection of potential issues.

Psychological and Social Impact
The visual changes associated with aphakia can have a psychological and social impact. For children, early and effective correction is vital for normal development of vision and learning. For adults, adapting to new visual experiences and ensuring effective correction can require patience and support. Understanding the condition and available solutions can empower individuals to lead fulfilling lives.
In conclusion, aphakia is the absence of the eye’s natural crystalline lens. While it significantly alters the eye’s refractive and accommodative capabilities, leading to profound hyperopia and the inability to accommodate, modern ophthalmic advancements offer effective solutions. From specialized spectacles and contact lenses to the widespread use of intraocular lenses, the management of aphakia aims to restore clear, functional vision, enabling individuals to see the world with clarity and confidence.