
Understanding the Auditory Hallmarks of Lung Inflammation
Pneumonia, a pervasive infection that inflames the air sacs in one or both lungs, fundamentally alters the acoustic landscape within the respiratory system. While the visual manifestations of pneumonia are often discussed in terms of radiographic findings and clinical symptoms, the auditory cues provided by the lungs can be equally diagnostic and are a cornerstone of physical examination in respiratory medicine. These sounds, often described as “rales,” “rhonchi,” or “wheezes,” are not merely random noises but specific sonic signatures that indicate the presence of fluid, inflammation, and compromised airflow. Understanding these sounds requires a basic grasp of how healthy lungs produce sound and how pneumonia disrupts this delicate acoustic balance.
The Symphony of Healthy Lungs
In a healthy individual, the lungs are remarkably quiet during normal respiration. The primary sound generated is the gentle whoosh of air moving through the trachea and into progressively smaller bronchi and bronchioles, eventually reaching the alveoli. This smooth airflow creates a relatively consistent and soft sound, best heard with a stethoscope over the chest wall. This baseline sound is often referred to as “vesicular breath sounds.” Deviations from this norm, particularly the advent of crackling, bubbling, or rattling noises, are immediate indicators of a problem. These abnormal sounds arise from changes in the physical state of the airways and the air within them.
The mechanics of breathing involve the expansion and contraction of the chest cavity, drawing air into the lungs and expelling it. This process is facilitated by the elasticity of lung tissue and the coordinated action of the diaphragm and intercostal muscles. As air travels through the airways, it encounters different structures, each contributing to the overall sound profile. The larger airways, like the trachea and bronchi, produce louder and lower-pitched sounds due to their wider diameter and thicker walls. As the airways branch into smaller bronchioles and eventually reach the alveoli, the air velocity decreases, and the sounds become softer and higher-pitched. The alveoli themselves, tiny air sacs responsible for gas exchange, are normally filled with air, and their movement during respiration is largely inaudible.
When a person is at rest, breathing is typically shallow and quiet. However, during exertion or with conditions that affect lung volume, the sounds become more pronounced. The pitch, intensity, and duration of breath sounds are all important diagnostic parameters. For instance, diminished breath sounds might suggest a problem with air entry into a particular lung segment, while exaggerated breath sounds could indicate increased airflow or consolidation. The texture of the sound – whether it’s smooth, turbulent, or interrupted – provides crucial clues about the underlying pathology.
The Cacophony of Pneumonia: Crackles (Rales)
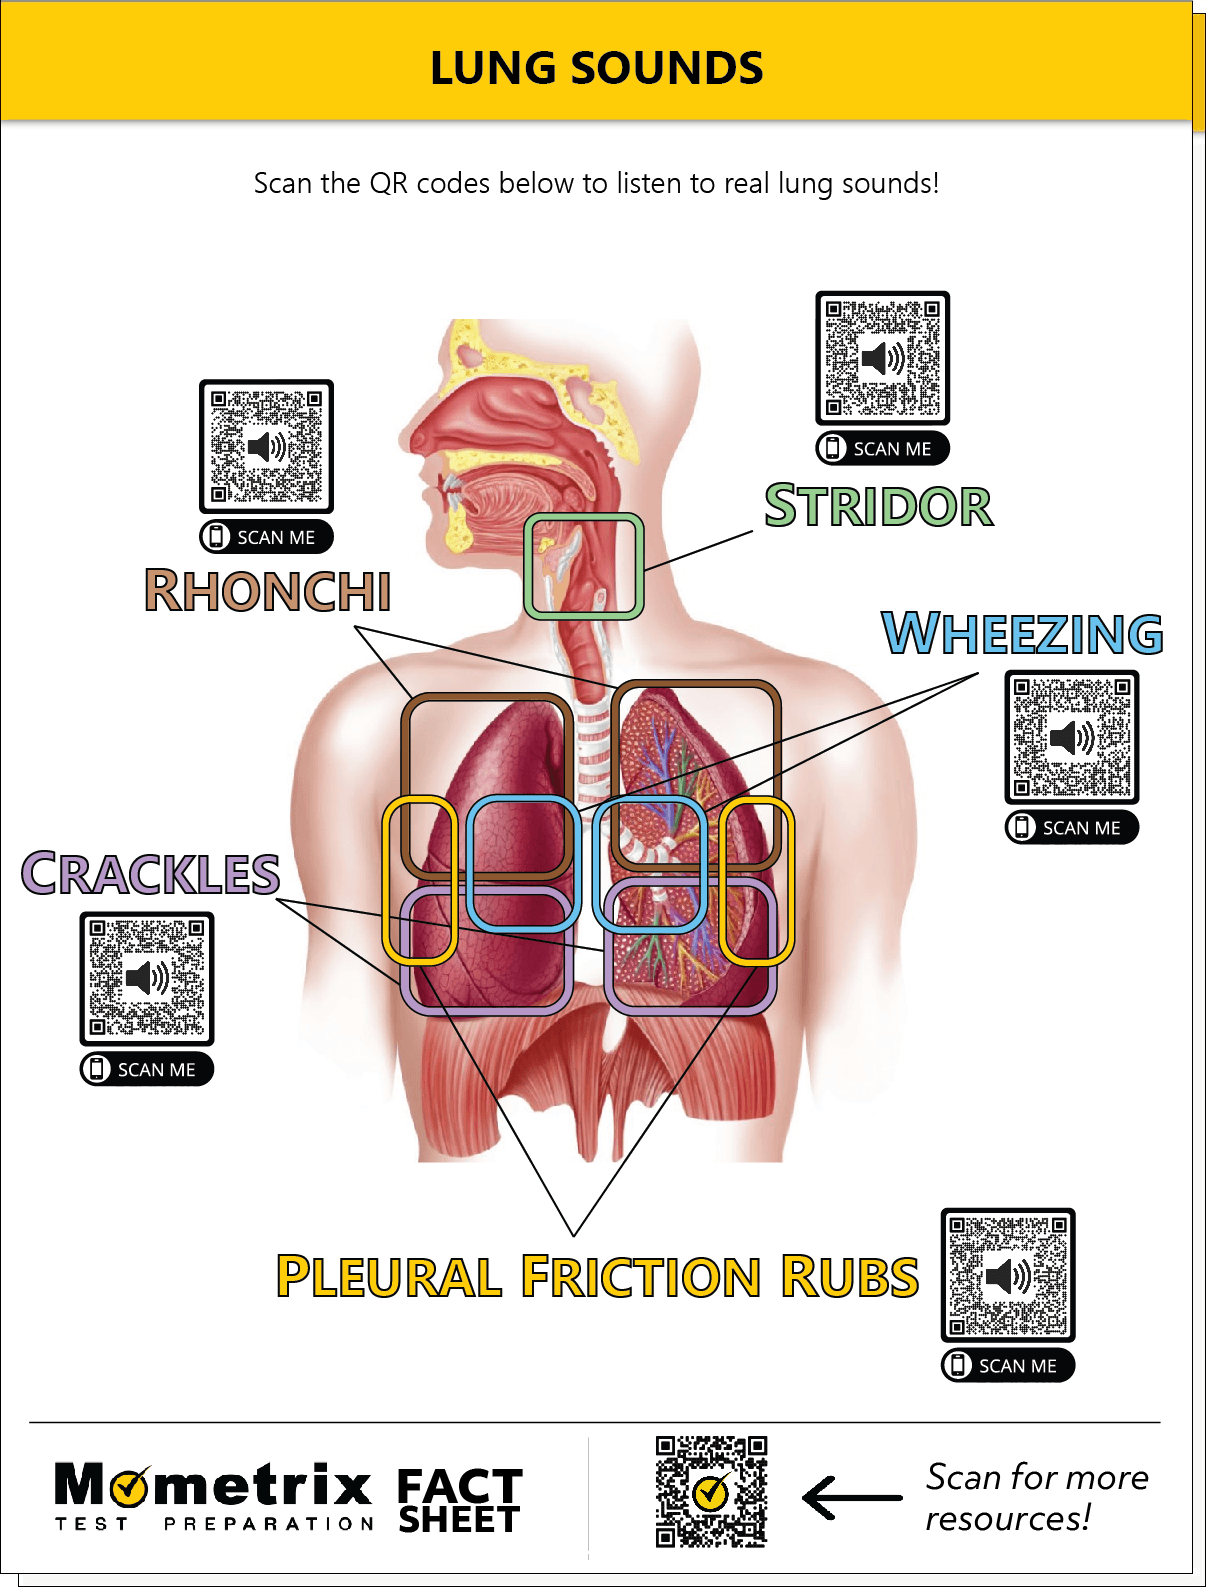
The most characteristic abnormal lung sound associated with pneumonia is the crackle, often historically referred to as a “rales.” Crackles are discontinuous, brief, popping or crackling sounds that occur during inspiration, and sometimes expiration. They are analogous to the sound of cellophane being crinkled or Velcro being pulled apart.
The Genesis of Crackles
Crackles are believed to be caused by the sudden opening of collapsed or fluid-filled airways. In pneumonia, the alveoli, which are normally filled with air, become engorged with inflammatory exudate, pus, or fluid. This accumulation impedes the normal passage of air. During inspiration, as negative pressure is generated in the chest cavity, these partially or completely collapsed alveoli are suddenly pulled open, causing the surrounding fluid to vibrate. This rapid inflation and vibration create the distinct popping sound.
The type of crackles heard can offer further diagnostic information:
- Fine crackles: These are high-pitched, soft, and very brief sounds, often described as resembling the sound of hair being rubbed between your fingers. They are typically heard late in inspiration and are indicative of fluid in the smaller airways and alveoli, common in early or mild pneumonia, or conditions like pulmonary fibrosis.
- Coarse crackles: These are lower-pitched, louder, and longer-lasting sounds, reminiscent of boiling water or Velcro being ripped. They are heard earlier in inspiration and are associated with fluid in the larger airways, suggesting a more significant inflammatory process or the presence of thicker secretions.
The distribution of crackles is also important. If they are localized to a specific lobe or segment of the lung, it strongly suggests a focal pneumonia. Bilateral crackles might indicate a more widespread infection or a different underlying condition. The persistence of crackles throughout the respiratory cycle, or their change in character with coughing, can provide further insights into the nature and severity of the pneumonia. For example, if crackles clear after a patient coughs, it might suggest that secretions are contributing significantly to the sound, and their removal provides temporary relief. However, in many cases of pneumonia, especially those involving significant alveolar filling, crackles will persist despite coughing.
Beyond Crackles: Rhonchi and Wheezes
While crackles are the hallmark of alveolar involvement in pneumonia, other adventitious sounds can also be present, reflecting different aspects of the inflammatory process.
Rhonchi: The Gurgling of Congestion
Rhonchi are low-pitched, continuous, snoring or rattling sounds that are typically heard during both inspiration and expiration. They are often described as sounding like a blocked pipe or a snore.

The Mechanism of Rhonchi
Rhonchi are caused by the passage of air through airways that are narrowed by thick secretions or inflammation. Unlike crackles, which are discontinuous and caused by the sudden opening of closed structures, rhonchi are continuous and produced by the vibration of mucus or inflammatory material within the larger airways, such as the bronchi. This vibration occurs as air flows over these thickened secretions.
The presence of rhonchi in pneumonia suggests significant bronchial involvement, where the inflammatory process has led to increased mucus production and thickening of the bronchial walls. This can obstruct airflow, leading to the characteristic gurgling sound. Coughing often temporarily alters or clears rhonchi, as it can dislodge some of the obstructing secretions. However, if the inflammation is severe or the secretions are particularly tenacious, rhonchi may persist.
Wheezes: The Whistle of Constriction
Wheezes are high-pitched, musical, whistling sounds that are usually heard during expiration, though they can also occur during inspiration. They are produced by the rapid passage of air through narrowed airways.
The Genesis of Wheezes
While often associated with asthma or bronchiolitis, wheezing can also be heard in certain types of pneumonia. This occurs when the inflammation and swelling of the bronchial walls lead to significant narrowing of the airways. This narrowing increases the velocity of airflow, causing the edges of the airways to vibrate and produce a musical note. Pneumonia can cause such narrowing due to edema of the bronchial mucosa, or sometimes due to bronchospasm triggered by the inflammatory process.
Wheezes are distinct from crackles and rhonchi in their pitch and continuous nature. They are a sign of airflow obstruction, and their presence in pneumonia may indicate a more severe inflammatory response or a superimposed condition like reactive airway disease. The intensity of the wheeze can vary, and it may be localized to a particular area of the lung or be more generalized.
The Clinical Significance of Lung Sounds in Pneumonia
The interpretation of lung sounds is a critical component of the physical examination of a patient suspected of having pneumonia. A skilled clinician uses a stethoscope to auscultate the chest, systematically listening to breath sounds in different areas. The presence, type, location, and timing of adventitious sounds provide invaluable clues for diagnosis, assessing severity, and monitoring treatment response.
- Diagnostic Clues: Crackles, rhonchi, and wheezes, when heard in conjunction with other symptoms like fever, cough, and shortness of breath, strongly point towards pneumonia. The specific combination and distribution of these sounds can help differentiate between different types of pneumonia and rule out other respiratory conditions. For instance, the predominance of fine crackles might suggest a typical bacterial pneumonia affecting the alveoli, while the presence of coarse crackles and rhonchi could indicate a more productive cough with significant bronchial involvement, possibly a viral or atypical pneumonia.
- Severity Assessment: The loudness and widespread nature of crackles or rhonchi can correlate with the extent of lung involvement and the severity of inflammation. For example, extensive bilateral crackles may suggest severe pneumonia requiring more aggressive management. The presence of diminished breath sounds alongside adventitious sounds can indicate areas of lung that are not adequately ventilated due to consolidation or pleural effusions, further contributing to the assessment of severity.
- Monitoring Treatment Response: As a patient recovers from pneumonia, the abnormal lung sounds typically diminish or disappear. The clearing of crackles and rhonchi, and the return of normal vesicular breath sounds, are reassuring signs that the inflammatory process is resolving and the lungs are returning to normal function. Conversely, if abnormal sounds persist or worsen despite treatment, it may indicate a treatment failure, complications, or the development of a secondary infection.
Technological Augmentations: Enhancing Auditory Diagnosis
While the stethoscope remains a primary tool, technological advancements are increasingly being integrated into the assessment of lung sounds, offering enhanced precision and analytical capabilities.

Digital Stethoscopes and AI Analysis
Digital stethoscopes are capable of recording and amplifying lung sounds, allowing for more detailed analysis than traditional acoustic stethoscopes. These recordings can be saved for later review, shared with specialists, or analyzed by sophisticated algorithms.
The application of artificial intelligence (AI) in this field is particularly promising. AI algorithms can be trained on vast datasets of lung sound recordings, enabling them to identify subtle patterns and differentiate between various types of adventitious sounds with remarkable accuracy. These AI-powered systems can assist clinicians by:
- Automated identification and classification of lung sounds: AI can objectively identify and categorize crackles, rhonchi, and wheezes, reducing inter-observer variability and potential for human error.
- Quantification of sound characteristics: AI can measure parameters like frequency, amplitude, and duration of abnormal sounds, providing objective data for severity assessment and monitoring treatment response.
- Early detection of subtle abnormalities: AI algorithms may be able to detect changes in lung sounds that are not readily apparent to the human ear, potentially leading to earlier diagnosis of pneumonia or other respiratory conditions.
- Remote monitoring and telemedicine: Digital recordings of lung sounds analyzed by AI can facilitate remote patient monitoring, allowing for timely intervention and reducing the need for frequent in-person visits.
While these technologies are not intended to replace the clinical judgment of a healthcare professional, they serve as powerful adjuncts, augmenting diagnostic capabilities and paving the way for more personalized and efficient respiratory care. The subtle whispers and crackles within the lungs, once solely interpreted by the trained ear, are now being amplified and illuminated by the power of digital technology and artificial intelligence.