
Torticollis, often referred to as “wryneck,” is a condition characterized by a twisted neck in which the head is tilted to one side while the chin is turned to the opposite shoulder. When it affects infants, it is typically known as congenital muscular torticollis (CMT) or simply “torticollis baby.” This condition is usually present at birth or develops within the first few months of life, often due to a tightening or shortening of the sternocleidomastoid (SCM) muscle on one side of the neck. While alarming for parents, CMT is generally treatable, especially with early detection and intervention, often involving innovative approaches in monitoring and therapy. Understanding the nuances of torticollis, from its causes and symptoms to modern diagnostic tools and therapeutic technologies, is crucial for optimal outcomes.
Understanding Congenital Muscular Torticollis
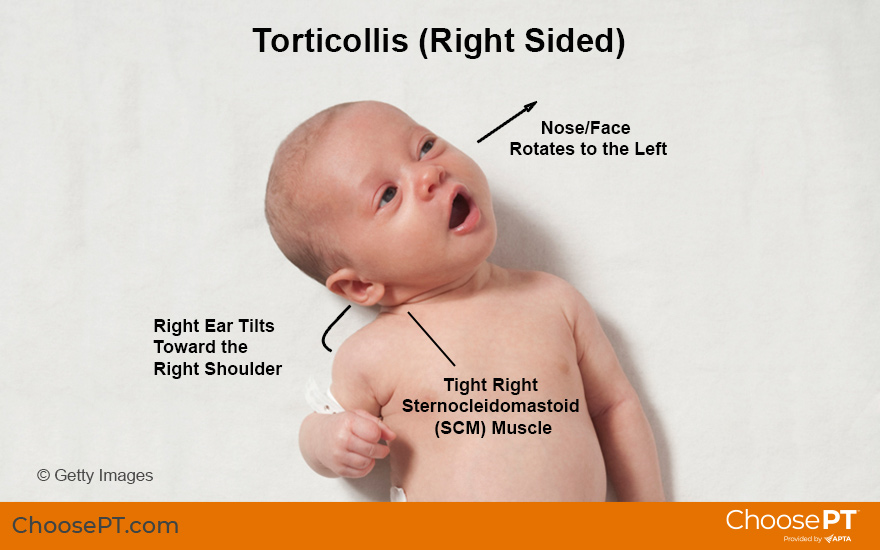
Congenital muscular torticollis is the most common type of torticollis in infants. It is a postural deformity of the head and neck that results from unilateral shortening and fibrosis of the SCM muscle. This muscle runs from behind the ear (mastoid process) down to the collarbone and breastbone. Its primary functions include rotating the head to the opposite side and tilting it to the same side. When one SCM muscle is affected, it restricts the infant’s ability to move their head freely, leading to the characteristic head tilt and chin rotation.
The Sternocleidomastoid Muscle’s Role
The SCM muscle is pivotal in head movement. In CMT, the muscle on one side becomes tight and shortened, often feeling like a palpable lump or “olive” in the muscle belly, though this lump typically resolves on its own within the first year. The exact cause of this muscle shortening is not always clear, but several factors are thought to contribute. These include positioning in the womb (intrauterine constraint), breech presentation, multiple births, and difficult deliveries involving vacuum extraction or forceps. These scenarios can lead to trauma or ischemia (reduced blood flow) to the SCM muscle, resulting in muscle fiber damage and subsequent scarring and shortening. The affected side usually corresponds to the direction the head is tilted. For instance, if the right SCM is shortened, the baby’s head will tilt to the right, and the chin will rotate towards the left shoulder.
Identifying the Signs
Parents are often the first to notice the signs of torticollis. The most obvious symptom is the consistent head tilt, where the baby’s ear seems to rest on one shoulder. Other common signs include:
- Head preference: The baby consistently turns their head to one side.
- Difficulty turning head: Limited range of motion when trying to turn the head past the midline to the affected side.
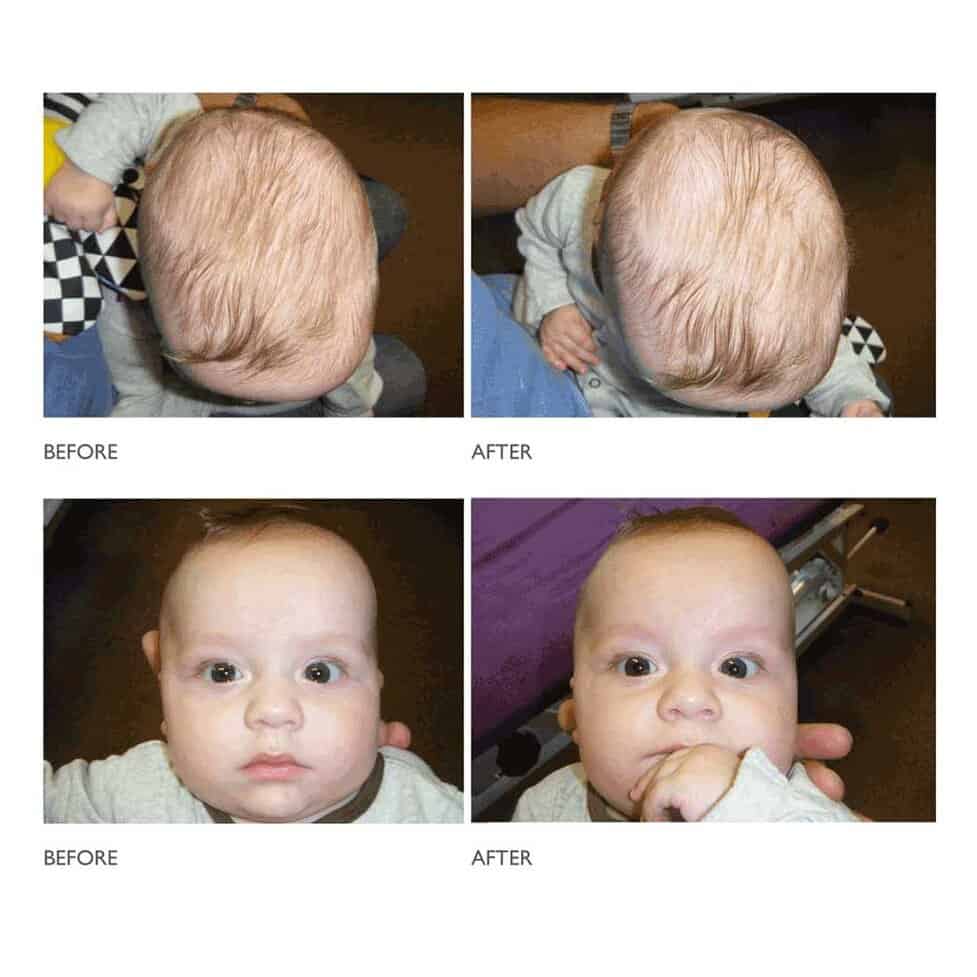
- Facial asymmetry: Over time, if untreated, the constant pressure can lead to flattening on one side of the head (plagiocephaly) and potentially facial asymmetry as the baby grows.
- Developmental delays: In severe or untreated cases, persistent head positioning can impact motor skills like rolling, sitting, and reaching.
- Irritability: Some babies may show discomfort or cry when attempts are made to move their head past the restricted range.
Early identification is paramount, as conservative treatments are highly effective when initiated promptly. Modern technological innovations are increasingly playing a role in both diagnosing and monitoring these subtle signs.
Early Detection and Diagnostic Innovation
The timely diagnosis of torticollis is critical for successful treatment and preventing secondary complications such as plagiocephaly and developmental delays. While a physical examination by a pediatrician is the primary diagnostic tool, technological advancements are enhancing our ability to detect and assess the severity of CMT.
The Importance of Timely Assessment
Pediatricians often screen for torticollis during routine well-baby check-ups. They look for the characteristic head tilt, palpate the SCM muscle for any lumps or tightness, and assess the baby’s range of motion. Early intervention, ideally before 3 months of age, significantly improves the chances of full recovery with conservative management. Delays can necessitate more prolonged therapy or, in rare cases, surgical intervention. The insight provided by parents regarding their observations of the baby’s head preference and movement is invaluable. Educating parents on the signs to watch for empowers them to seek medical advice sooner.
Emerging Technologies in Diagnosis
Innovation in diagnostics is continually evolving to provide more objective and precise assessments.
- AI-assisted image analysis: Artificial intelligence is beginning to revolutionize early detection. Computer vision algorithms can analyze photographs or video footage of infants to identify subtle head tilts, rotational preferences, and degrees of restricted motion that might be missed by the human eye, especially in the earliest stages. By training AI models on large datasets of infant postures, these systems can provide quantitative measurements of head alignment and track changes over time, offering a non-invasive screening tool. This technology holds promise for telehealth applications, allowing parents to submit images for preliminary assessment, potentially flagging at-risk infants for earlier in-person evaluation.
- 3D Scanning for Cranial Asymmetry: While not directly diagnosing torticollis, 3D cranial scanning technology is crucial for assessing and monitoring plagiocephaly, a common comorbidity. These non-invasive scanners create a precise 3D model of the baby’s head, accurately measuring deformities and tracking the effectiveness of repositioning strategies or helmet therapy. This provides objective data for clinicians and helps parents visualize progress.
- Quantitative Range of Motion Measurement Devices: Handheld goniometers have traditionally been used to measure joint angles. However, more advanced, often digital, devices and even smartphone applications using built-in accelerometers and gyroscopes are being explored to provide more precise and reproducible measurements of cervical range of motion, helping to quantify the severity of muscle tightness and track improvement during therapy.

These innovations aim to make diagnosis more accessible, objective, and earlier, leading to better outcomes for infants with torticollis.
Therapeutic Approaches and Technological Aids
Once torticollis is diagnosed, treatment typically involves conservative measures, primarily physical therapy. However, technology is increasingly integrated into the therapeutic process to enhance effectiveness, adherence, and monitoring.
Physical Therapy Fundamentals
The cornerstone of torticollis treatment is a comprehensive physical therapy program. A pediatric physical therapist designs specific stretching and strengthening exercises tailored to the individual infant.
- Stretching: Exercises focus on gently stretching the shortened SCM muscle to lengthen it and restore full range of motion. This involves positioning the baby’s head to tilt it away from the affected side and rotate the chin towards the affected side.
- Strengthening: Exercises aim to strengthen the opposing neck muscles and the SCM muscle on the non-affected side, promoting symmetrical head control.
- Positioning: Parents are educated on proper positioning techniques during feeding, sleeping, and play to encourage head movement in the non-preferred direction. “Tummy time” is particularly emphasized to strengthen neck and core muscles.
- Environmental adaptations: Adjusting the baby’s environment to encourage them to turn their head towards the restricted side (e.g., placing toys, light sources, or the parent’s voice).
Consistency in these exercises, performed multiple times a day, is key to success.
Wearable Tech for Monitoring and Guidance
Adherence to home exercise programs is crucial, but also challenging for parents. Here, innovative wearable technology and smart devices offer significant promise:
- Sensor-based monitoring devices: Small, lightweight sensors can be discreetly attached to an infant’s head or clothing to track head position, movement patterns, and the duration spent in different head orientations. These devices can provide real-time feedback to parents and therapists, ensuring exercises are performed correctly and that positioning strategies are maintained throughout the day. Data collected can be wirelessly transmitted to a smartphone app, allowing therapists to remotely monitor progress and adjust treatment plans without requiring constant in-person visits. This remote sensing capability can be invaluable, especially for families in rural areas or with limited access to specialists.
- Biofeedback systems: Some advanced systems incorporate biofeedback, providing auditory or visual cues to infants or parents when the head deviates from a desired symmetrical position. For older infants, this can help them actively participate in correcting their head posture.
- Smart mats and play areas: Integrating sensors into play mats or activity centers can track an infant’s head movements during play, encouraging symmetrical engagement and identifying preferences that need to be addressed. These systems can gamify therapy, making it more engaging for both infant and parent.
- Virtual reality and augmented reality: While still largely in the research phase for infants, VR/AR could potentially create engaging environments for older infants and toddlers undergoing physical therapy, making exercises more interactive and enjoyable.
These technological aids don’t replace hands-on therapy but augment it, providing objective data, enhancing consistency, and empowering parents to be more effective participants in their child’s recovery.
Preventing Progression and Enhancing Outcomes
The primary goal in managing torticollis is to achieve a full, symmetrical range of motion in the neck and prevent secondary complications. This requires a concerted effort from parents, caregivers, and medical professionals, supported by continuous innovation in care delivery.
Parental Engagement and Home Exercises
Parents are integral to the success of torticollis treatment. They are essentially the “at-home therapists” who carry out the prescribed exercises multiple times daily. Education on the condition, clear demonstration of exercises, and ongoing support from therapists are essential. Resources like instructional videos, mobile apps with exercise reminders, and progress tracking features can significantly boost parental confidence and adherence. Encouraging consistent tummy time, ensuring babies are positioned to turn their heads to the non-preferred side, and engaging them with toys and sounds from that direction are simple yet powerful interventions. The “tech” in parental engagement often lies in the digital tools that facilitate learning and compliance, turning complex medical advice into manageable daily routines.
Future Innovations in Treatment and Support
The field of pediatric rehabilitation is continuously evolving. Looking ahead, we can anticipate further integration of technology:
- Personalized AI-driven therapy plans: Leveraging AI to analyze individual infant data (e.g., muscle stiffness, range of motion, developmental milestones, response to therapy) to generate highly personalized exercise regimens and adapt them in real-time based on progress.
- Advanced robotics for gentle stretching: While manual therapy is paramount, robotic assistance could potentially provide highly controlled, gentle, and consistent stretching for infants with severe limitations, though ethical considerations and safety would be paramount.
- Tele-rehabilitation platforms: Enhanced tele-rehabilitation services, integrating high-resolution video consultations with sensor data from home, will make expert care more accessible globally. This remote sensing and monitoring capability, while different from drone-based remote sensing, shares the core principle of gathering data from a distance to inform decision-making.
- Early warning systems: Further development of AI-powered systems that can analyze routine infant movements or even cry patterns (a form of remote sensing data from audio) to flag potential developmental issues, including early signs of torticollis, even before physical asymmetry becomes obvious.
In conclusion, congenital muscular torticollis is a common yet highly treatable condition in infants. While traditional physical therapy remains the cornerstone of management, the integration of advanced technology and innovation, from AI-assisted diagnostics to wearable monitoring devices and enhanced tele-rehabilitation, promises to revolutionize early detection, treatment efficacy, and long-term outcomes for affected babies and their families.