
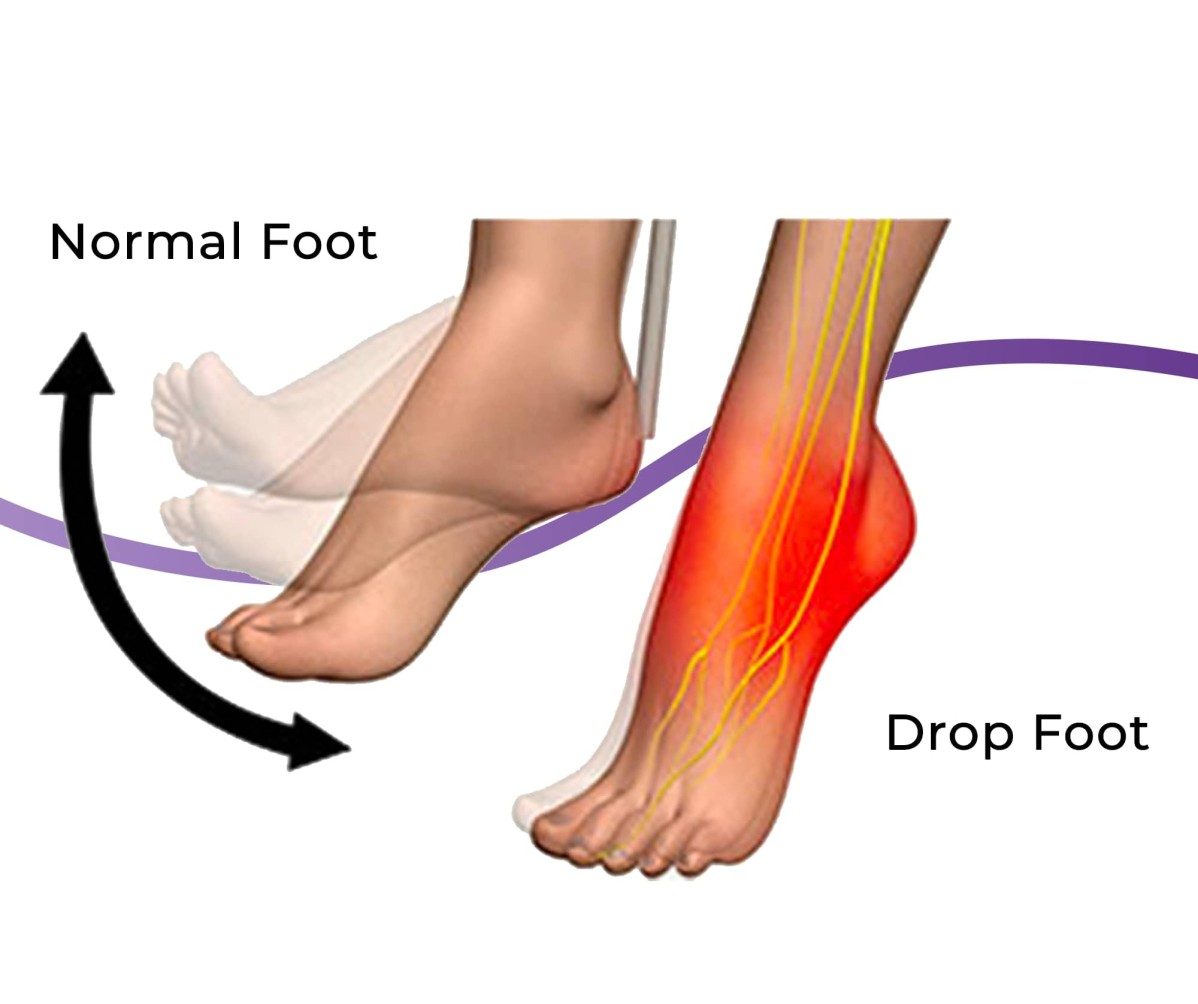
Drop foot, also known as foot drop, is a complex neurological and muscular condition that affects a person’s ability to lift the front part of their foot. This inability to dorsiflex the ankle results in the toes dragging along the ground when walking. It’s not a disease in itself, but rather a symptom of an underlying issue affecting the nerves, muscles, or brain that control the movement of the foot. The consequences of drop foot can range from a noticeable gait abnormality to a significant tripping hazard, impacting mobility, confidence, and overall quality of life.

Understanding drop foot requires a closer look at the intricate biomechanics of the foot and ankle and the neural pathways that orchestrate their movement. The primary muscle responsible for lifting the foot is the tibialis anterior, located on the front of the shin. This muscle is controlled by the common peroneal nerve, a branch of the sciatic nerve, which originates from the spinal cord. Any disruption along this pathway, from the brain and spinal cord down to the muscles themselves, can lead to drop foot.
The presentation of drop foot can vary in severity. In mild cases, the foot may only partially lift, leading to a subtle drag or shuffle. In more severe instances, the foot may hang limply, requiring compensatory movements like a high-stepping gait (also known as steppage gait) to avoid tripping. This compensatory action can strain other muscles and joints, leading to secondary problems such as hip pain or back issues. The sensation of the foot being “heavy” or “dead” is also commonly reported.
Neurological Origins of Drop Foot
The most common cause of drop foot is nerve damage, specifically affecting the common peroneal nerve. This nerve plays a critical role in innervating the muscles responsible for dorsiflexion and eversion of the foot. Damage to this nerve can occur due to a variety of factors, ranging from direct trauma to chronic conditions.
Nerve Compression and Injury
Direct compression of the common peroneal nerve is a frequent culprit. This can happen at the fibular head, a bony prominence on the outside of the knee where the nerve passes close to the surface. Prolonged pressure on this area, such as from sitting with legs crossed for extended periods, wearing tight casts or braces, or even sleeping in certain positions, can lead to temporary or permanent nerve damage.
- Sciatica and Radiculopathy: Conditions that affect the sciatic nerve, which branches into the peroneal nerve, can also cause drop foot. Herniated discs, spinal stenosis, or other spinal cord injuries in the lumbar region can compress the nerve roots that form the sciatic nerve, leading to symptoms that radiate down the leg, including drop foot.
- Trauma and Surgery: Direct injuries to the knee or lower leg, such as fractures of the fibula or tibia, can damage the peroneal nerve. Surgical procedures in the knee, hip, or leg can also inadvertently injure the nerve.
- Peripheral Neuropathy: This is a broad category of nerve disorders that can affect any peripheral nerve in the body. Diabetic neuropathy, caused by high blood sugar levels damaging nerves over time, is a very common cause of peripheral neuropathy and can manifest as drop foot. Other causes include autoimmune diseases like Guillain-Barré syndrome, infections, and exposure to toxins.
Central Nervous System Disorders
While peripheral nerve damage is more common, disorders affecting the central nervous system (brain and spinal cord) can also lead to drop foot by disrupting the neural signals to the leg muscles.
- Stroke: A stroke, which occurs when blood flow to a part of the brain is interrupted, can damage the motor pathways controlling leg movement. Depending on the location and severity of the stroke, individuals may experience weakness or paralysis in one or both legs, including drop foot.
- Multiple Sclerosis (MS): This chronic autoimmune disease affects the myelin sheath, the protective covering around nerve fibers in the brain and spinal cord. Damage to the myelin can disrupt nerve signal transmission, leading to a range of neurological symptoms, including muscle weakness and spasticity, which can result in drop foot.
- Amyotrophic Lateral Sclerosis (ALS): Also known as Lou Gehrig’s disease, ALS is a progressive neurodegenerative disease that affects nerve cells in the brain and spinal cord. It causes muscle weakness and atrophy, and drop foot is a common early symptom, often affecting one foot before the other.
- Parkinson’s Disease: While primarily known for its effects on motor control, including tremors and rigidity, Parkinson’s disease can also cause gait abnormalities and muscle weakness, which may manifest as drop foot in some individuals.
- Brain Tumors: Tumors in areas of the brain that control motor function can compress or damage nerve pathways, leading to various motor impairments, including drop foot.
Muscular and Other Contributing Factors
Although nerve damage is the most prevalent cause, in some instances, drop foot can arise from primary muscle weakness or other less common factors.
Muscular Dystrophies
These are genetic disorders characterized by progressive weakness and degeneration of skeletal muscles. While often affecting larger muscle groups, some forms of muscular dystrophy can impact the muscles responsible for foot dorsiflexion, leading to drop foot.
Myopathies
Myopathies are diseases that affect muscle fibers. They can be inherited or acquired and can cause muscle weakness, which, if it affects the anterior tibialis muscle, can result in drop foot.
Traumatic Injuries and Fractures
Severe trauma to the lower leg, including fractures of the tibia or fibula, can not only damage the nerves but also directly affect the muscles responsible for lifting the foot. If the muscles themselves are severely torn or damaged, their ability to function can be compromised, contributing to or causing drop foot.
Other Conditions
- Polio: While largely eradicated in many parts of the world due to vaccination, polio is a viral disease that can cause paralysis by attacking motor neurons, leading to significant muscle weakness and drop foot.
- Electrolyte Imbalances: Severe imbalances in electrolytes like potassium or calcium can sometimes lead to muscle weakness and, in rare cases, contribute to symptoms resembling drop foot.
Diagnosis and Assessment of Drop Foot
Diagnosing the cause of drop foot is a crucial step in developing an effective treatment plan. A thorough medical history, physical examination, and specific diagnostic tests are typically employed.
Medical History and Physical Examination
The doctor will begin by asking about the onset of symptoms, any preceding injuries or illnesses, and other medical conditions. The physical examination will focus on observing the patient’s gait, assessing muscle strength in the legs and feet, checking reflexes, and testing sensation. Specific tests might be performed to pinpoint the exact location and extent of any nerve damage or muscle weakness.

Diagnostic Tests
- Nerve Conduction Studies (NCS) and Electromyography (EMG): These tests are fundamental in diagnosing nerve damage. NCS measures the speed and strength of electrical signals traveling along nerves, while EMG assesses the electrical activity of muscles at rest and during contraction. Together, they can identify damaged nerves and muscles and help pinpoint the site of the problem.
- Imaging Studies: MRI or CT scans of the spine and brain can help identify structural abnormalities like herniated discs, spinal stenosis, tumors, or signs of stroke or MS that might be causing nerve compression or central nervous system damage. Imaging of the leg may also be performed to rule out fractures or other structural issues.
- Blood Tests: Blood tests can help identify underlying systemic conditions such as diabetes, autoimmune diseases, or infections that may be contributing to nerve damage.
The accurate diagnosis of the root cause of drop foot is paramount, as treatment strategies will vary significantly depending on whether the issue stems from nerve compression, a central nervous system disorder, or muscle disease.