
Tympanostomy is a common surgical procedure involving the insertion of a small tube, often called an ear tube or grommet, into the eardrum (tympanic membrane). This procedure is primarily performed to treat conditions related to middle ear fluid accumulation and chronic or recurrent ear infections, most notably otitis media with effusion (OME) and recurrent acute otitis media (AOM). The core purpose of a tympanostomy tube is to provide ventilation to the middle ear, allow fluid to drain, and equalize pressure across the eardrum, thereby preventing further fluid buildup and reducing the frequency of infections. This seemingly minor intervention represents a significant advancement in pediatric ear care, profoundly impacting the quality of life for countless children.
Understanding Otitis Media and the Need for Intervention
Otitis media refers to inflammation of the middle ear, often caused by bacterial or viral infections. It is incredibly common in young children due to the anatomy of their Eustachian tubes, which are narrower, more horizontal, and less efficient than those in adults. When these tubes become blocked, fluid can accumulate behind the eardrum, leading to pressure, pain, and potential hearing impairment.
Chronic or Recurrent Otitis Media
Recurrent acute otitis media (AOM) is defined by multiple episodes of middle ear infection within a short period, typically three or more episodes in six months or four or more in a year. Each episode can bring fever, ear pain (otalgia), and irritability. Repeated use of antibiotics, while necessary for treatment, raises concerns about antibiotic resistance and potential side effects. For children experiencing persistent AOM, tympanostomy tubes offer a prophylactic measure by ensuring continuous middle ear ventilation, which helps prevent fluid accumulation that serves as a breeding ground for bacteria and viruses.
Effusion and Hearing Loss
Otitis media with effusion (OME) occurs when fluid remains in the middle ear for an extended period after an infection, or even in the absence of an active infection. This “glue ear” can persist for weeks or months, leading to conductive hearing loss. In young children, chronic hearing loss, even mild to moderate, can significantly impede speech and language development, academic performance, and social interaction. Tympanostomy is often recommended for OME that persists for three months or longer, particularly if associated with hearing loss, developmental delays, or significant otalgia, as it immediately drains the fluid and restores hearing.
The Tympanostomy Procedure: A Detailed Overview
The tympanostomy procedure is a relatively quick and minimally invasive outpatient surgery, typically performed under general anesthesia, especially for children. The entire process, from induction of anesthesia to recovery, usually takes less than an hour, with the surgical component lasting only about 10 to 15 minutes.
Pre-Operative Assessment and Preparation
Before the surgery, a thorough evaluation by an otolaryngologist (ear, nose, and throat specialist) is conducted. This includes a review of the child’s medical history, frequency of ear infections, duration of fluid accumulation, and any associated symptoms like hearing loss or speech delays. An audiogram (hearing test) and tympanometry (eardrum movement test) are often performed to confirm the presence of hearing loss and fluid. Parents receive instructions regarding fasting prior to surgery and what to expect during and after the procedure.
Surgical Technique: Placement of Tympanostomy Tubes
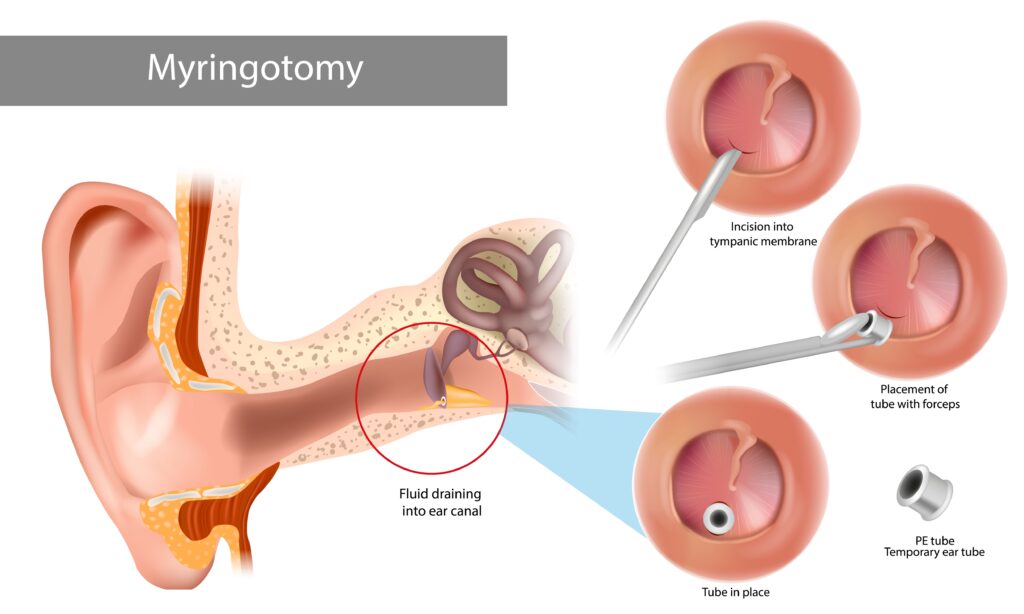
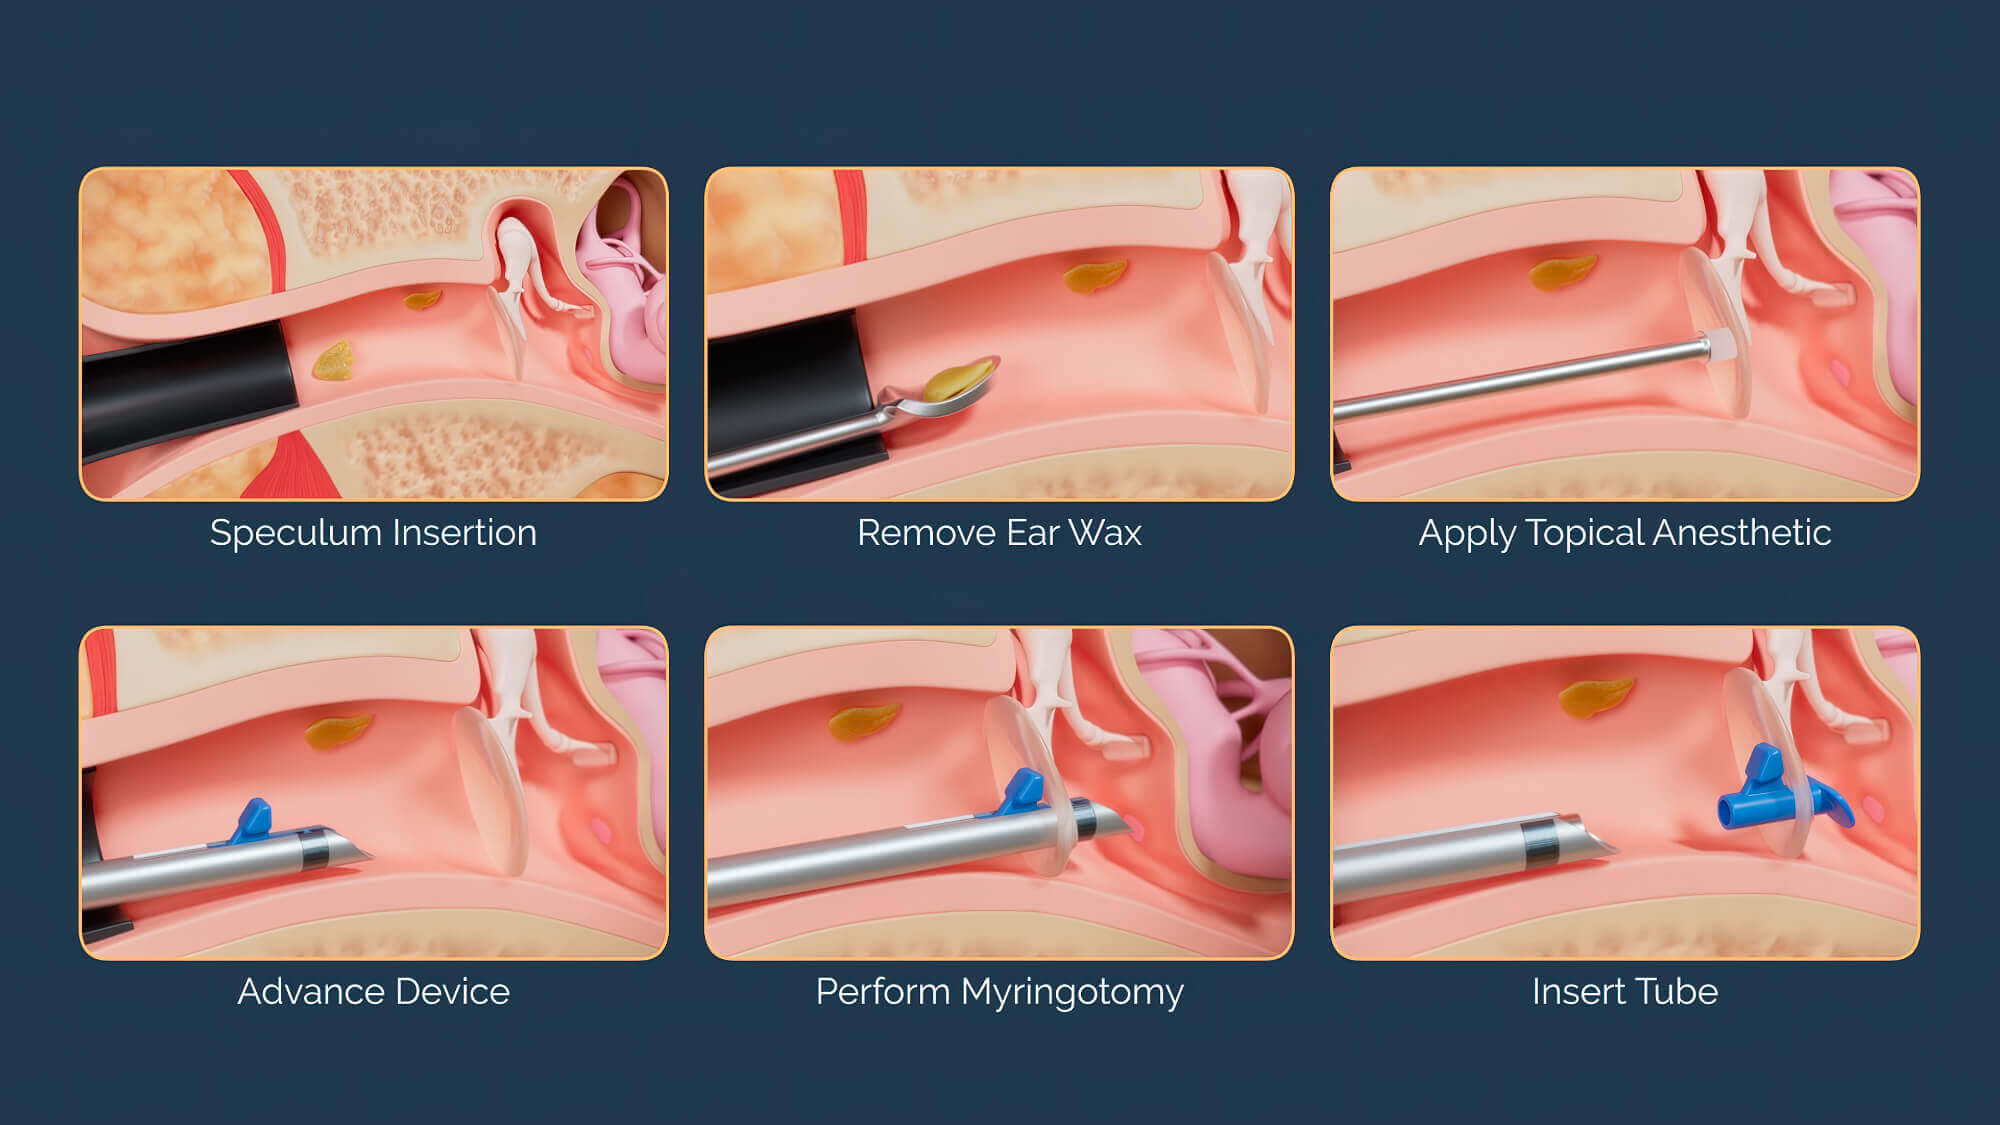
During the procedure, the surgeon makes a tiny incision (myringotomy) in the eardrum using a microscope for magnification. Any fluid present in the middle ear is suctioned out. A small tympanostomy tube is then inserted through the incision, allowing air to enter the middle ear space and any remaining fluid to drain. The tube essentially acts as a tiny ventilation shaft. This immediate equalization of pressure often provides instant relief from pain and restores hearing. The tubes are designed to remain in place for several months, typically 6 to 18 months, before naturally extruding (falling out) as the eardrum heals and pushes them out.
Types of Tympanostomy Tubes
Tympanostomy tubes come in various designs and materials, each suited for different situations. Short-term tubes, such as “collar button” or “Shah” tubes, are designed to fall out within 6 to 12 months. They are made from materials like silicone or fluoroplastic. Long-term tubes, often referred to as “T-tubes,” have flanges that extend further into the middle ear, providing a more secure fit and remaining in place for longer, sometimes several years. These are typically used for more severe or persistent cases. The choice of tube depends on the individual patient’s condition, the severity of the ear problems, and the surgeon’s preference. Advances in biocompatible materials have made these tubes safer and more effective over time.
Post-Operative Care and Tube Extrusion
Recovery from tympanostomy tube insertion is generally swift and uncomplicated. However, careful post-operative management is essential to ensure the success of the procedure and prevent complications.
Immediate Recovery and Activity Restrictions
Children usually recover quickly from general anesthesia and can typically return home within a few hours after the procedure. Pain is usually minimal, often managed with over-the-counter pain relievers. Most children can resume normal activities within 24 hours. The primary post-operative instruction often involves protecting the ears from water, especially contaminated water, to prevent infection through the tubes. This might involve using earplugs or special headbands during bathing, swimming, or hair washing. These precautions are typically advised for the duration the tubes are in place, though some surgeons may relax these restrictions for certain activities or for older children.
Monitoring and Follow-up Care
Regular follow-up appointments with the otolaryngologist are crucial. These visits typically occur a few weeks after surgery and then every 4 to 6 months until the tubes extrude. During these appointments, the surgeon checks the position and patency (openness) of the tubes, assesses the eardrum, and monitors the middle ear space. Hearing tests may be repeated to confirm improvement. Parents are advised to watch for signs of tube blockage, infection (otorrhea, or drainage from the ear), or premature extrusion.
Natural Extrusion and Potential Complications
Most tympanostomy tubes naturally extrude from the eardrum as it heals and regenerates. They usually fall out into the ear canal and may be unnoticed or removed by the parent or physician. Once the tube comes out, the small incision in the eardrum typically closes on its own. While generally safe, potential complications can include:
- Otorrhea: Ear drainage or infection, which usually responds well to antibiotic ear drops.
- Tube Blockage: Tubes can become blocked with earwax or debris, impairing their function.
- Premature Extrusion: Tubes falling out too soon, potentially requiring reinsertion if the ear problems recur.
- Persistent Perforation: In a small percentage of cases (1-2%), the hole in the eardrum may not close after the tube extrudes, requiring a surgical patch (tympanoplasty) to repair it.
- Tympanosclerosis: Scarring of the eardrum, which is usually benign and does not affect hearing significantly.
- Cholesteatoma: A rare but serious complication involving an abnormal skin growth behind the eardrum.
Long-Term Impact and Efficacy
Tympanostomy tube insertion has a well-established track record of efficacy in managing recurrent AOM and chronic OME, leading to significant improvements in pediatric health and development.
Benefits for Hearing and Speech Development
The most immediate and profound benefit for children with OME is the restoration of normal hearing. By draining fluid and equalizing pressure, tubes eliminate the conductive hearing loss, allowing children to hear clearly. This is especially vital during critical periods of speech and language acquisition. Studies consistently show that children with chronic OME who receive tubes experience better speech and language outcomes compared to those managed with watchful waiting, helping them to catch up to their peers and thrive academically and socially.
Addressing Quality of Life
Beyond hearing, tubes dramatically reduce the frequency and severity of ear infections, leading to fewer sick days from school or daycare, less pain and discomfort for the child, and reduced stress for parents. The need for repeated antibiotic courses decreases, lessening the concerns about antibiotic resistance. This overall improvement in health contributes significantly to a child’s general well-being and quality of life.
Considerations and Alternatives
While highly effective, tympanostomy is not always the first line of treatment. Watchful waiting is often recommended for initial episodes of OME, as many cases resolve spontaneously. For recurrent AOM, initial management may involve antibiotics. Adenoidectomy (removal of the adenoids) is sometimes performed concurrently with tympanostomy, especially if enlarged adenoids are believed to contribute to Eustachian tube dysfunction. The decision to proceed with tympanostomy is always individualized, based on the severity of symptoms, impact on development, and overall health status of the child.
The Technological Evolution of Tympanostomy
The practice of tympanostomy, while seemingly straightforward, has seen continuous innovation driven by advancements in medical technology, improving patient outcomes and refining surgical techniques. It represents a significant area of “Tech & Innovation” within medical practice.
Advances in Surgical Tools and Imaging
Modern tympanostomy benefits greatly from sophisticated surgical microscopes and endoscopes, which provide high-resolution, magnified views of the ear canal and eardrum. This enhanced visualization allows surgeons to perform the myringotomy with greater precision and minimizes trauma to surrounding tissues. The development of micro-instruments specifically designed for ear surgery has also contributed to the procedure’s success and safety. Furthermore, advancements in diagnostic imaging, such as improved audiometry and tympanometry devices, ensure more accurate pre-operative assessment and post-operative monitoring of middle ear function.
Material Innovations in Tube Design
The materials used for tympanostomy tubes have evolved significantly. Early tubes were often made from metal or simple plastics. Today, tubes are commonly made from biocompatible materials like silicone, fluoroplastic, and titanium, which are well-tolerated by the body and minimize adverse reactions. These materials are chosen for their inertness, flexibility, and durability, contributing to longer tube patency and reduced risk of tissue irritation. Different tube designs, with varying lumen sizes, flanges, and retention characteristics, reflect continuous innovation aimed at optimizing drainage, ventilation, and retention time based on specific patient needs. This ongoing material science research ensures that tubes are safer and more effective.

Future Directions and Minimally Invasive Techniques
The field continues to explore even more minimally invasive approaches. Research is underway on technologies like laser-assisted myringotomy, which uses focused laser energy to create the eardrum incision, potentially offering even greater precision and reducing the need for general anesthesia in some cases, particularly for adults or older cooperative children. Efforts are also being made to develop “smart tubes” that could incorporate drug delivery mechanisms or even biodegradable materials that dissolve once their function is complete, eliminating the need for natural extrusion or manual removal and further reducing potential complications like persistent perforation. These innovations highlight the ongoing commitment to refining tympanostomy, ensuring it remains a cornerstone of effective ear care while pushing the boundaries of surgical and material science.